

Phẫu thuật giải phóng cứng bàn tay Dupuytren Thông tin
Quy trình này sẽ hướng dẫn quá trình hồi phục của bạn sau ca phẫu thuật cắt bỏ màng cứng gây co rút ngón tay (phẫu thuật cắt màng cứng) do bác sĩ Kieran Hirpara thực hiện tại Bệnh viện tư nhân Mater Rockhampton. Hai yếu tố then chốt để đạt kết quả tốt là nẹp cố định – giúp giữ các ngón tay thẳng trong lúc vết thương lành lại – và chương trình tập luyện nhằm duy trì sự vận động của các ngón tay. Hãy mang theo trang này hoặc bản PDF tương ứng đến gặp chuyên viên trị liệu tay để quá trình phục hồi diễn ra đồng bộ.
Nếu bạn có bất kỳ thắc mắc nào về vết mổ sau phẫu thuật, hãy liên hệ với phòng khám. Việc chụp ảnh vết thương rồi gửi qua email để được đánh giá cũng thường rất hữu ích.
Những điều bạn có thể mong đợi
Phẫu thuật điều trị bệnh Dupuytren nhằm loại bỏ những sợi mô bị tổn thương đang kéo các ngón tay về phía lòng bàn tay, giúp các ngón tay có thể duỗi thẳng trở lại. Tình trạng bệnh này được giải thích chi tiết trên trang Bệnh Dupuytren; hiện chưa có phương pháp chữa khỏi vĩnh viễn, và mục tiêu của phẫu thuật là cắt bỏ mô bị tổn thương để khôi phục khả năng duỗi thẳng các ngón tay.
Thông thường, sau phẫu thuật khoảng 2–3 ngày, bạn sẽ được giới thiệu đến chuyên viên trị liệu tay. Chuyên viên này sẽ làm một chiếc nẹp nhựa riêng cho bạn, giúp giữ các ngón tay vừa phẫu thuật ở tư thế duỗi thẳng; đồng thời hướng dẫn bạn thực hiện các bài tập nhẹ nhàng được nêu dưới đây. Chiếc nẹp và các bài tập này bổ trợ cho nhau: nẹp giúp duy trì tư thế thẳng mà phẫu thuật đã đạt được, còn các bài tập giúp ngăn ngừa tình trạng cứng khớp do ngón tay bị co rút.
Hãy giữ vết mổ sạch sẽ và khô ráo cho đến khi cắt chỉ. Sau khi cắt chỉ, bạn có thể làm ướt da, nhưng hãy tránh ngâm hoặc nhúng tay vào nước trong vòng một tuần nữa. Trang Chăm sóc vết thương của phòng khám sẽ hướng dẫn chi tiết về cách băng bó, các dấu hiệu nhiễm trùng và cách chăm sóc sẹo. Việc massage vùng sẹo cũng rất quan trọng sau phẫu thuật Dupuytren; chuyên viên trị liệu sẽ hướng dẫn bạn cách thực hiện sau khi vết thương đã lành.
Chăm sóc vết sẹo
Trong những tuần đầu sau phẫu thuật Dupuytren, vết sẹo ở lòng bàn tay thường cứng, nổi lên và gây đau nhức; sau đó dần trở nên mềm mại và mờ đi trong vài tháng tiếp theo. Massage vết sẹo là một phần thường quy trong quy trình trị liệu tay tại Úc: theo một cuộc khảo sát toàn quốc về các chuyên gia trị liệu tay được chứng nhận, hầu hết họ đều áp dụng phương pháp này sau phẫu thuật tay (thường bắt đầu khoảng thời điểm cắt chỉ, khi vết thương đã lành hoàn toàn) nhằm làm mềm vết sẹo, giúp da trượt dễ dàng trên các mô bên dưới và giảm độ nhạy cảm của vết sẹo; phương pháp này thường được kết hợp với gel hoặc miếng dán silicone thay vì sử dụng đơn lẻ [6]. Các bằng chứng nghiên cứu về việc massage vết sẹo vẫn đang được bổ sung, nhưng đã cho thấy hiệu quả trong việc giảm cảm giác khó chịu liên quan đến vết sẹo và cải thiện khả năng vận động [6]. Chuyên viên trị liệu sẽ hướng dẫn bạn kỹ thuật này và có thể chỉ định sử dụng sản phẩm silicone; loại sản phẩm này thường được đeo vào ban đêm cùng với nẹp chỉnh hình.
Quá trình hồi phục, việc trở lại làm việc và diễn biến lâu dài
Trong những tuần đầu sau phẫu thuật, tình trạng sưng và cứng khớp là hiện tượng bình thường; các triệu chứng này sẽ giảm dần khi tay được vận động. Cảm giác thoải mái, khả năng vận động và lực nắm tay thường tiếp tục cải thiện trong vài tháng tiếp theo. Việc nâng cao tay và vận động nhẹ nhàng trong giai đoạn đầu sẽ giúp giảm sưng và ngăn ngừa tình trạng cứng khớp nhỏ. Độ thẳng của ngón tay sau phẫu thuật thường được duy trì tốt trong suốt thời gian này. Trong một nghiên cứu ngẫu nhiên về phục hồi chức năng sau phẫu thuật cắt bỏ màng cứng Dupuytren, hầu hết các ngón tay đã được phẫu thuật vẫn giữ nguyên hoặc cải thiện được độ duỗi trong ba tháng đầu điều trị tay [2].
Thời gian nghỉ việc phụ thuộc vào tính chất công việc của bạn. Trong một nghiên cứu trên hơn 2.500 người được điều trị bệnh Dupuytren, thời gian trung bình để trở lại làm việc sau phẫu thuật cắt màng cứng là khoảng hai tuần; khoảng 90% bệnh nhân đã quay lại làm việc trong vòng một năm; những công việc đòi hỏi sức lực nhiều thì thời gian nghỉ lâu hơn [4]. Bác sĩ Hirpara sẽ trao đổi với bạn về thời điểm thích hợp để trở lại làm việc tùy theo đặc thù công việc; những công việc chân tay nặng nhọc thường chỉ được thực hiện sau khi vết thương lành hẳn và lực nắm tay đã trở lại bình thường.
Vì bệnh Dupuytren là tình trạng kéo dài suốt đời, độ cứng của ngón tay có thể tái phát theo thời gian; tỷ lệ tái phát được ghi nhận trong các nghiên cứu cũng rất khác nhau, tùy thuộc vào cách định nghĩa tái phát. Nhìn chung, diễn biến lâu dài khá tích cực: trong một nghiên cứu theo dõi 142 ca phẫu thuật cắt màng cứng trong khoảng bốn năm, dựa trên định nghĩa thống nhất hiện nay, tỷ lệ tái phát thực sự của tình trạng co rút chỉ vào khoảng 3–4% các trường hợp; tuy nhiên, khoảng một phần ba bệnh nhân vẫn còn một chút độ cong nhẹ ở ngón tay, nhưng mức độ này thường không đáng kể và không bằng mức độ co rút đã được điều chỉnh sau phẫu thuật [5]. Việc đeo nẹp, chăm sóc sẹo và thực hiện các bài tập đều nhằm mục đích bảo vệ kết quả phẫu thuật; nếu có ngón tay nào bắt đầu cứng lại sau này, hãy thông báo ngay cho chúng tôi.
Nẹp cố định của bạn
- Tuần đầu tiên: Hãy đeo nẹp cả ngày lẫn đêm; chỉ tháo nẹp ra khi thực hiện các bài tập (và khi được phép thì có thể rửa tay).
- Sau tuần đầu tiên: Hầu hết mọi người chuyển sang chỉ đeo nẹp vào ban đêm; đồng thời có thể bắt đầu sử dụng tay cho các hoạt động nhẹ vào ban ngày.
- Việc đeo nẹp vào ban đêm cần duy trì khoảng 3 tháng (trong một số trường hợp có thể kéo dài tới 6 tháng) nhằm ngăn ngừa các ngón tay bị dịch chuyển trở lại về phía lòng bàn tay trong quá trình mô lành lại.
- Chuyên viên trị liệu vận động và bác sĩ Hirpara sẽ hướng dẫn cụ thể cho bạn về lịch trình đeo nẹp và các hoạt động được phép. Những thời điểm nêu trên chỉ là mô hình thông thường, không phải quy tắc cố định.
Bạn tuyệt đối không được lái xe khi tay vẫn đang đeo nẹp. Khi đã chuyển sang chỉ đeo nẹp vào ban đêm, bạn có thể lái xe vào ban ngày nếu cảm thấy thoải mái và có thể nắm vô lăng một cách an toàn.
Dành cho chuyên viên trị liệu vận động / chuyên viên trị liệu tay:
Cách quản lý
- Chuyển bệnh nhân đến làm nẹp cố định bằng vật liệu nhiệt dẻo sau 2–3 ngày phẫu thuật.
- Lịch trình đeo nẹp: đeo cả ngày lẫn đêm trong khoảng tuần đầu tiên (tháo ra khi tập luyện), sau đó chỉ đeo vào ban đêm kết hợp với các hoạt động nhẹ vào ban ngày; việc đeo nẹp ban đêm cần tiếp tục khoảng 3 tháng (có thể kéo dài tới 6 tháng nếu cần) theo đánh giá của bác sĩ phẫu thuật và chuyên viên trị liệu.
- Thực hiện chương trình tập luyện tại nhà theo các hướng dẫn dưới đây: duỗi thẳng ngón tay chủ động, hạn chế gập khớp DIP, gập khớp DIP/PIP quanh thân bút, gập ngón tay tổng hợp, vận động cổ tay theo kiểu tenodesis.
- Chăm sóc vết thương theo hướng dẫn của phòng khám; thực hiện các biện pháp chăm sóc sẹo sau khi vết thương đã lành.
- Số lần lặp lại và tần suất thực hiện mỗi ngày do chuyên viên trị liệu chỉ định.
Những lưu ý cần chú ý
- Giữ vết thương sạch và khô cho đến khi cắt chỉ; sau đó không được ngâm hay nhúng tay vào nước trong vòng một tuần nữa.
- Việc tuân thủ đúng lịch trình đeo nẹp là yếu tố then chốt để duy trì hiệu quả duỗi thẳng ngón tay sau phẫu thuật.
- Không được lái xe khi tay vẫn đang đeo nẹp.
Đây là các bài tập được ghi trong tờ hướng dẫn dành cho bạn; bạn sẽ thực hiện cùng chuyên viên trị liệu tay và tiếp tục luyện tập tại nhà.
Các bài tập của bạn
Kieran Hirpara 4.0
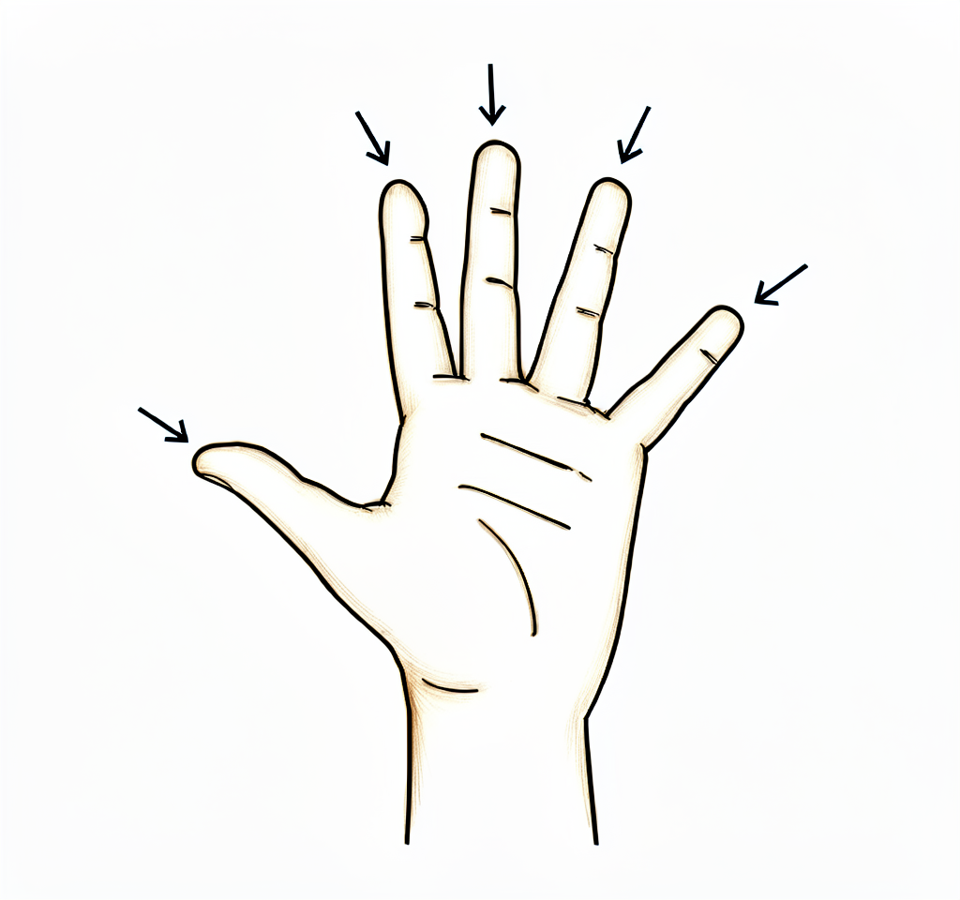
Chuyển động duỗi chủ động
Khi cổ tay giữ thẳng, hãy duỗi thẳng và dạng các ngón tay ra hết mức có thể. Bạn có thể dùng tay kia hỗ trợ nhẹ nhàng. Sau đó thả lỏng và lặp lại động tác.
Theo chỉ dẫn của chuyên viên trị liệu tay của bạn.
Kieran Hirpara 4.0
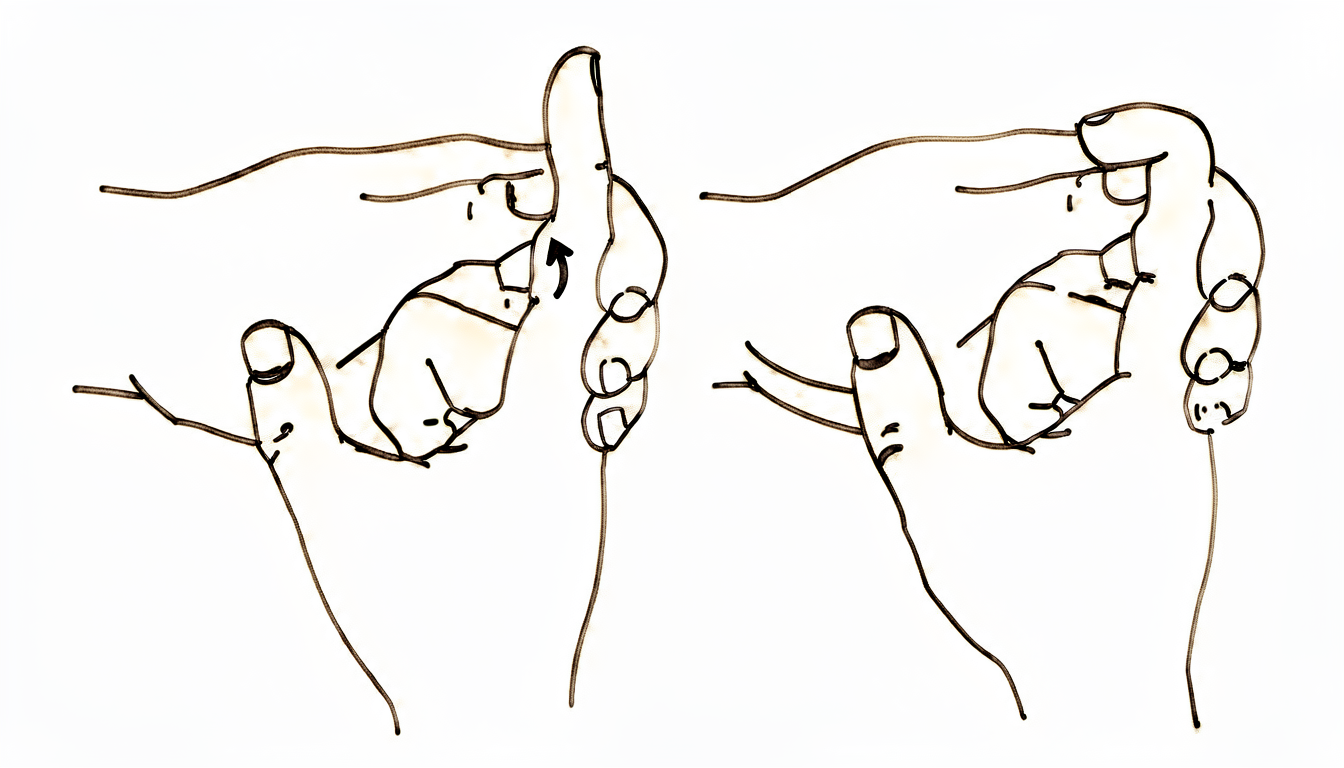
Gập chủ động khớp liên đốt xa (DIP)
Dùng tay kia đỡ ngón tay ngay phía dưới nếp gấp của khớp cuối (khớp DIP). Gập mạnh khớp cuối rồi thả lỏng.
Theo chỉ dẫn của chuyên viên trị liệu tay của bạn.
Kieran Hirpara 4.0
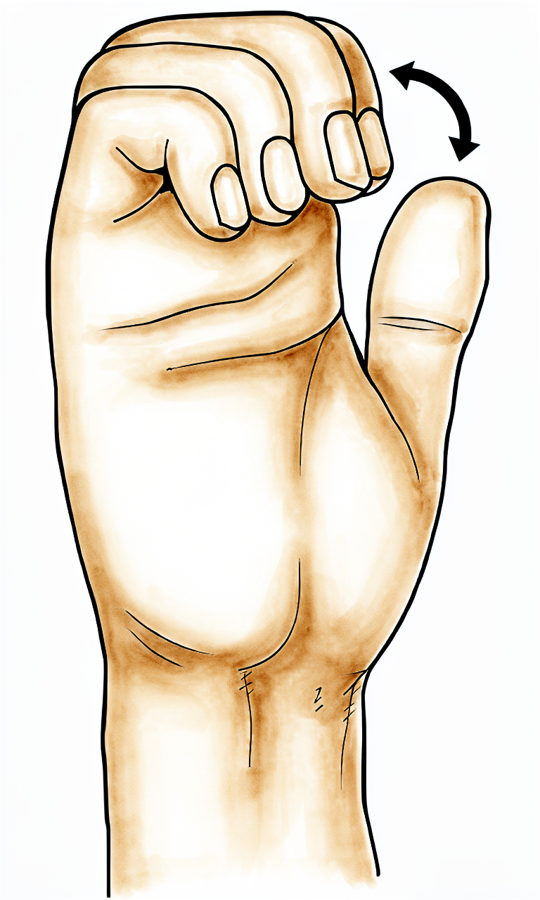
Chuyển động gập khớp đốt xa/đốt giữa ngón tay một cách chủ động
Đặt một cây bút ngang qua gốc các ngón tay. Cong các ngón tay quanh cây bút sao cho cả hai khớp ngón tay (khớp giữa và khớp cuối) đều gập lại, sau đó thả lỏng.
Theo chỉ dẫn của chuyên viên trị liệu tay của bạn.
Kieran Hirpara 4.0
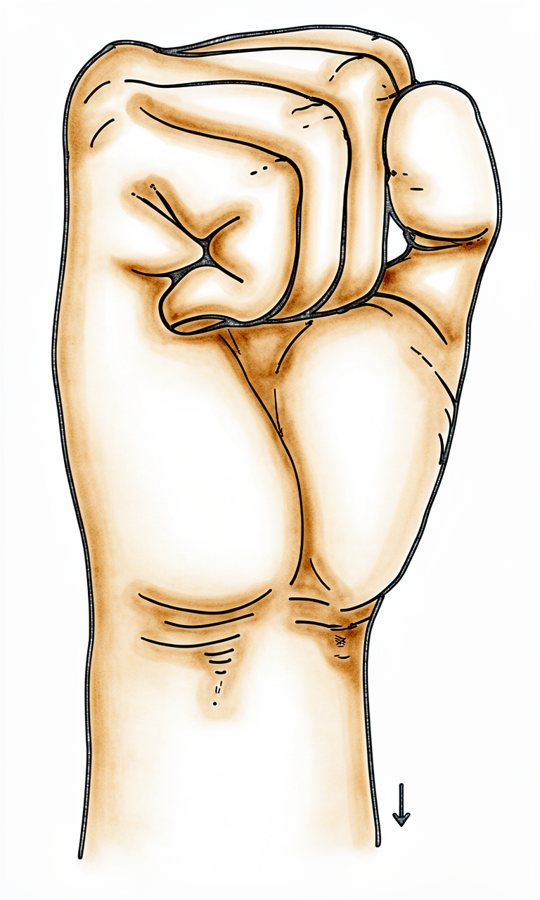
Gập phức hợp
Hãy khẽ nắm tay thành nắm đấm lỏng, sau đó thả lỏng và để các ngón tay duỗi thẳng ra.
Theo chỉ dẫn của chuyên viên trị liệu tay của bạn.
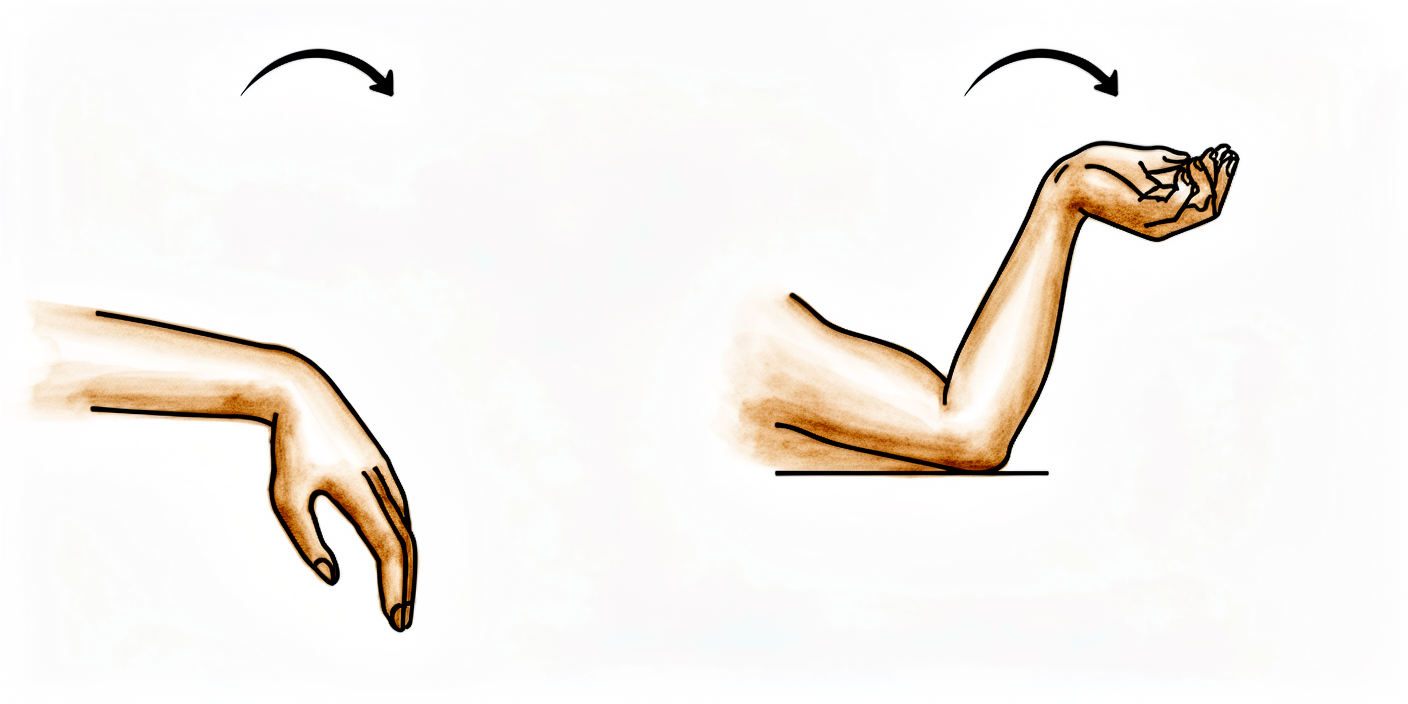
Kieran Hirpara 4.0
Bài tập hiệu ứng tenodesis cổ tay
Nghỉ ngơi bằng cách chống khuỷu tay xuống mặt phẳng, giữ các ngón tay thả lỏng; sau đó gập cổ tay về phía trước rồi về phía sau, để các ngón tay di chuyển theo một cách tự nhiên.
Theo chỉ dẫn của chuyên viên trị liệu tay của bạn.
Hãy thực hiện các bài tập dưới đây chỉ khi có sự hướng dẫn của Bác sĩ Hirpara và chuyên viên trị liệu vận động, đồng thời tuân thủ mọi phạm vi chuyển động và giới hạn đã được đề ra. Mục đích chính của ca phẫu thuật này là giúp ngón tay duỗi thẳng; vì vậy việc duỗi thẳng chủ động là bài tập ưu tiên — nếu bạn không tập luyện, các ngón tay sẽ dần trở lại tư thế cong, và phạm vi chuyển động mà bạn duy trì chính là phạm vi bạn sẽ sử dụng sau này. Các bài tập gập ngón tay (gập khớp DIP, gập khớp DIP/PIP và gập tổng hợp) cũng rất quan trọng; bởi một ngón tay chỉ có thể duỗi thẳng cũng chẳng hữu ích bằng một ngón tay chỉ có thể gập cong. Cơ chế tenodesis của cổ tay đóng vai trò kết nối giữa hai chức năng này. Hãy đeo nẹp đêm theo chỉ dẫn. Ngừng ngay mọi bài tập gây đau dữ dội, và thông báo cho chuyên viên trị liệu nếu có ngón tay nào bắt đầu mất khả năng duỗi thẳng.
Sau khi thực hiện theo phác đồ
Phác đồ này được soạn thảo với sự hợp tác của Ruby Doolan – chuyên gia trị liệu tay được chứng nhận thuộc trung tâm Extend Rehabilitation. Phác đồ này được sử dụng song song với các hướng dẫn phục hồi chung của phòng khám: xem mục Cách kiểm soát cơn đau sau phẫu thuật, Chăm sóc vết thương và Những điều cơ bản về trị liệu tay. Đối với quy trình phẫu thuật, xin tham khảo mục Phẫu thuật cắt bỏ màng cứng trong bệnh Dupuytren.
Những thông tin về tiến trình hồi phục, thời điểm có thể quay lại làm việc và cách chăm sóc vết sẹo nêu trên được trích dẫn từ các thử nghiệm lâm sàng, bài tổng quan và khảo sát về phục hồi chức năng sau phẫu thuật Dupuytren; bao gồm cả các thử nghiệm ngẫu nhiên và bài tổng quan có hệ thống về việc sử dụng nẹp và trị liệu tay sau phẫu thuật cắt bỏ màng cứng [1–3]. Chế độ sử dụng nẹp và chương trình tập luyện là do chính phòng khám đề xuất, được thống nhất giữa bác sĩ Hirpara và chuyên gia trị liệu tay của bạn; lịch trình đeo nẹp cũng được điều chỉnh phù hợp với từng bệnh nhân trong các buổi tái khám.
Tài liệu tham khảo
[1] Jerosch-Herold C, Shepstone L, Chojnowski AJ, Larson D, Barrett E, Vaughan SP. Việc sử dụng nẹp vào ban đêm sau khi cắt bỏ cân hoặc cắt bỏ da và cân trong điều trị co rút Dupuytren: một thử nghiệm ngẫu nhiên có đối chứng, đa trung tâm và mang tính thực tiễn. BMC Musculoskeletal Disorders. 2011;12:136. https://pmc.ncbi.nlm.nih.gov/articles/PMC3146906/ [2] Collis J, Collocott S, Hing W, Kelly E. Tác động của các dụng cụ nắn duỗi dùng vào ban đêm sau khi phẫu thuật giải phóng co rút Dupuytren: một thử nghiệm ngẫu nhiên có đối chứng tại một trung tâm duy nhất. Journal of Hand Surgery (American). 2013;38(7):1285–1294.e2. https://doi.org/10.1016/j.jhsa.2013.04.012 [3] Karam M, Kahlar N, Abul A, Rahman S, Pinder R. So sánh giữa phương pháp trị liệu tay có và không dùng nẹp sau khi cắt bỏ cân trong điều trị co rút Dupuytren: tổng quan có hệ thống và phân tích tổng hợp. Journal of Hand and Microsurgery. 2022;14(4):308–314. https://pmc.ncbi.nlm.nih.gov/articles/PMC10042625/ [4] Blake SN, Poelstra R, Andrinopoulou ER, và cộng sự. Việc trở lại làm việc và các chi phí liên quan sau điều trị bệnh Dupuytren. Plastic and Reconstructive Surgery. 2021;148(3):580–590. https://pubmed.ncbi.nlm.nih.gov/34292887/ [5] Radhamony NG, Nair RR, Sreenivasan S, và cộng sự. Tình trạng dị dạng còn sót lại so với tái phát sau khi cắt bỏ cân lòng bàn tay trong bệnh Dupuytren — kết quả theo dõi dài hạn trên 142 ca bệnh. Annals of Medicine and Surgery. 2022;73:103224. https://pmc.ncbi.nlm.nih.gov/articles/PMC8767281/ [6] Scott HC, Robinson LS, Brown T. Việc xoa bóp sẹo như một biện pháp can thiệp đối với các vết sẹo sau phẫu thuật: kết quả khảo sát thực hành của các chuyên gia trị liệu tay tại Úc. Hand Therapy. 2024;29(1):21–29. https://pmc.ncbi.nlm.nih.gov/articles/PMC10901164/
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: post-operative rehabilitation after open excision of diseased palmar/digital fascia for Dupuytren contracture — limited/regional fasciectomy, extending to dermofasciectomy (fascia plus overlying involved skin, replaced with a graft) for aggressive or recurrent disease. The procedure-selection literature (fasciectomy vs needle aponeurotomy vs collagenase) is summarised only as far as it frames recurrence expectations and rehabilitation; the rehab focus is the post-fasciectomy pathway — early active and passive finger extension and flexion, oedema control, scar management, and night extension splinting.
Defining principle of this rehab: fasciectomy removes diseased tissue and restores extension that the disease had taken away — it does not cure the diathesis, and the corrected finger sits in a tissue bed that wants to contract back. So the rehab is a "regain-and-hold" pathway: early motion to keep the freed joints supple and prevent the new flexor-tendon and skin-glide planes from binding down, oedema and scar control so the soft tissues mature without tethering, and a night extension orthosis to defend the surgical correction during healing. The defining clinical question is not whether a construct needs protection (there is no construct), but how aggressively to splint — and here the evidence has shifted decisively toward selective, not routine, splinting.
A. PROCEDURE OUTCOMES & RECURRENCE (context for the rehab)
Open partial (limited) fasciectomy is the long-standing reference operation for Dupuytren contracture and gives the most durable correction of the three mainstream options:
- Correction is reliable and recurrence is the dominant long-term limitation. Across modern series the operation restores extension well, but Dupuytren is a lifelong diathesis and some tightening returns over years. Reported recurrence rates vary enormously because studies define recurrence differently (any palpable disease vs a threshold extension loss vs need for re-intervention). Using the modern consensus definition, true recurrence of contracture is low at medium-term follow-up, though a substantial minority retain mild residual curvature well short of the pre-operative deformity [corpus: jhsa.2012.06.032; literature: Radhamony 2022].
- Fasciectomy vs minimally invasive options. Compared with needle aponeurotomy/fasciotomy and collagenase Clostridium histolyticum, open fasciectomy has a longer recovery and higher minor complication rate but lower recurrence — the recurring trade-off in this disease. Needle and collagenase are quicker with faster return to function but recur sooner [corpus: jhsa.2021.05.022; jhsa.2011.08.004; 1753193418786947]. This trade-off is why fasciectomy is typically chosen for denser, multi-ray or PIP-predominant contractures — the same cases whose rehab is hardest and whose splinting is most likely to be justified.
- Repeat limited fasciectomy for recurrence is safe and effective, supporting fasciectomy as a durable, repeatable mainstay rather than a one-shot procedure [corpus: bjj-2020-1393.r2].
Why this matters for rehab: recovery counselling and splint expectations must be framed against a disease that cannot be cured, only corrected — the rehab protects a correction, it does not prevent the diathesis.
B. THE SPLINTING CONTROVERSY (the central rehab question)
Historically, every patient was issued a static night extension orthosis after fasciectomy on the assumption it preserved the correction. The best available evidence does not support routine splinting — it supports selective splinting for patients who lose extension.
- Jerosch-Herold 2011 (pragmatic multi-centre RCT, n = 154). Hand therapy alone vs hand therapy + night splinting after fasciectomy/dermofasciectomy. No between-group difference in self-reported function (DASH), finger range of motion, or satisfaction. Authors concluded routine night splinting for all patients is not recommended, reserving it for cases where extension deficits recur [literature: Jerosch-Herold 2011, BMC Musculoskelet Disord].
- Collis 2013 (single-centre RCT, n = 56). Night extension orthosis + hand therapy vs hand therapy alone after surgical release. No significant difference in total active extension or any secondary outcome at 3 months. Same conclusion: provide an orthosis selectively, when extension loss occurs, not universally [corpus: jhsa.2013.04.012; literature: Collis 2013].
- Karam 2022 (systematic review + meta-analysis, 4 RCTs, n = 295). Pooling the splint-vs-no-splint trials found no significant difference in total active flexion/extension, DASH, pain, grip or satisfaction. The collective signal is consistent and now moderately strong: adding a splint to good hand therapy does not improve the average outcome [corpus: 1055/s-0041-1725221; literature: Karam 2022].
- Earlier/smaller work (e.g., post-fasciectomy splinting pilot studies) pointed the same way — splinting is low-yield as a blanket policy [corpus: 1753193412437631].
Practical reading for this protocol. The practice's pattern — splint day-and-night for ~1 week, then night-only with a low threshold to continue (or reinstate) splinting if a finger starts to drift back into flexion — is a reasonable, evidence-aligned middle path: it defends the correction during the highest-risk early healing window and during sleep, while honouring the trial finding that indefinite routine splinting adds little. The trials measured average outcomes; they do not say splinting is useless for the individual who is losing extension, which is exactly the subgroup the authors carved out. This is a defensible selective-splinting stance, not a contradiction of the protocol.
C. HAND-THERAPY & EXERCISE EVIDENCE
- Early supervised hand therapy is the backbone of recovery and is where the demonstrable benefit lies (the splint trials all compared against a hand-therapy baseline, not against nothing). Active and passive extension and flexion, oedema control and scar management are standard from the first post-operative therapy visit, typically 2–3 days after surgery.
- Most operated fingers hold or improve their extension over the first three months of hand therapy — the window in which the protocol concentrates splinting and exercise [corpus: jhsa.2013.04.012, control arm; literature: Collis 2013].
- Scar management. Scar massage is near-universal in hand-therapy practice after Dupuytren surgery to soften the palmar scar, improve skin glide and settle sensitivity, generally combined with silicone gel/sheeting and begun around suture removal once the wound is healed. The supporting evidence is developing rather than definitive but favours reduced scar-related discomfort and improved movement [literature: Scott 2024, Australian hand-therapist survey].
- Return to work. In a large cohort, median return after open fasciectomy was ~2 weeks with ~90% back at work within the year; physically demanding jobs took longer [literature: Blake 2021].
- Pre-operative hand therapy has a thinner evidence base and is not a substitute for the post-operative programme [corpus: 17589983241227162].
Phased rehabilitation timeline (matching the synthesis phases)
| Phase | Window | Splint | Movement / use | Scar & oedema | Notes |
|---|---|---|---|---|---|
| I — Protect & mobilise | ~Days 2–7 | Custom thermoplastic extension orthosis day & night, off for exercises | Gentle active extension + active DIP/PIP and composite flexion from the first therapy visit; wrist tenodesis | Oedema control (elevation, gentle movement); wound kept clean & dry | Therapy referral 2–3 days post-op; splint defends the surgical correction during the highest-risk window |
| II — Restore motion | ~Week 1 → 6–8 | Transition to night-only; light functional day use of the hand | Progress active + passive extension and flexion; restore full composite fist and full extension | Scar massage + silicone once wound healed (around suture removal) | Most extension is held or regained through this window; daytime driving resumes once out of the splint and grip is safe |
| III — Strengthen & return | ~Week 6–8 → 3 months | Night-only continues ~3 months (up to ~6 months selectively if extension is being lost) | Grip and functional strengthening; return to heavier manual work as wound is soundly healed and grip comfortable | Ongoing scar maturation over months | Splinting beyond this window is selective, driven by extension loss — not routine (see §B) |
The phase structure and timings are protocol/consensus, agreed between the surgeon and hand therapist; the trials inform the splinting policy within them, not the exact week boundaries.
D. COMPLICATIONS (rehab-relevant)
- Flare reaction / early CRPS-spectrum. A proportion of patients develop a post-operative inflammatory "flare" — disproportionate swelling, stiffness, redness and pain — which can progress to complex regional pain syndrome (CRPS type 1). Early recognition, oedema control, gentle continued motion and analgesia matter; CRPS is one of the more feared rehab-derailing complications after hand surgery [corpus: jht.2024.09.002 (Dupuytren CRPS-1 case); hcl.2009.11.001 (CRPS after hand surgery)].
- Digital nerve / vessel injury. The neurovascular bundles are displaced by Dupuytren cords, especially in recurrent disease and at the PIP; injury is a recognised operative risk. New sensory change post-operatively warrants surgeon review [corpus: hansur.2017.07.002 — complications systematic review; 17531934231206317 — surgical complications/adverse events].
- Wound healing, haematoma, infection, stiffness. Open fasciectomy has a higher minor-complication rate than the minimally invasive options; meticulous wound care and early motion mitigate stiffness and tethering [corpus: hansur.2017.07.002].
- Incomplete correction / residual PIP deficit. PIP contractures correct less completely than MCP; residual deficit may persist and is the usual trigger for selective ongoing splinting.
E. KEY CONTROVERSIES / EVIDENCE QUALITY
- Routine vs selective splinting — the headline controversy, now reasonably settled toward selective: three RCTs and a meta-analysis show no average benefit from adding a static night orthosis to good hand therapy, with all authors carving out the extension-loss subgroup. The practice's "night-only, low threshold to continue if drifting" approach is consistent with this. Moderate (multiple RCTs + SR/MA).
- Recurrence is definition-dependent — headline recurrence figures are not comparable across studies; the consensus definition gives lower, more credible rates. Counsel against the cure expectation. Moderate.
- Procedure choice frames rehab — fasciectomy trades a longer recovery and more minor complications for lower recurrence than needle/collagenase. The fasciectomy cohort is, by selection, the harder-rehab cohort. Moderate.
- The phase timings are consensus — drawn from surgeon/therapist protocols, not a rehab RCT. The splinting policy within them is trial-informed; the week boundaries are typical, not trial-derived. Weak/consensus.
F. EVIDENCE STRENGTH FLAGS (summary)
- MODERATE (multiple RCTs + SR/MA): routine night splinting adds no average benefit over hand therapy alone after fasciectomy — splint selectively for extension loss (Jerosch-Herold 2011; Collis 2013; Karam 2022 meta-analysis of 4 RCTs / 295 patients).
- MODERATE (cohorts / comparative): fasciectomy gives durable correction with lower recurrence but longer recovery and more minor complications than needle aponeurotomy/collagenase; repeat fasciectomy is safe and effective; CRPS and digital-nerve injury are recognised rehab-relevant complications.
- WEAK / CONSENSUS: the post-operative phase structure and timings themselves (surgeon + hand-therapist protocol; no defining rehab RCT). Scar-massage benefit is supportive but the evidence base is still developing.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Correction of contracture and recurrence rates of Dupuytren contracture following fasciectomy. J Hand Surg Am. 2012. DOI: 10.1016/j.jhsa.2012.06.032
- Repeat limited fasciectomy is a safe and effective treatment for recurrence of Dupuytren's contracture. Bone Joint J. 2021. DOI: 10.1302/0301-620X.103B5.BJJ-2020-1393.R2
- Limited fasciectomy versus collagenase Clostridium histolyticum for Dupuytren contracture. J Hand Surg Am. 2021. DOI: 10.1016/j.jhsa.2021.05.022
- The efficacy and safety of fasciectomy and fasciotomy for Dupuytren's contracture. J Hand Surg Eur. 2011. DOI: 10.1177/1753193410397971
- Cost-effectiveness of open partial fasciectomy, needle aponeurotomy, and collagenase injection for Dupuytren contracture. J Hand Surg Am. 2011. DOI: 10.1016/j.jhsa.2011.08.004
- Three-year recurrence of Dupuytren's contracture after needle fasciotomy and collagenase injection. J Hand Surg Eur. 2018. DOI: 10.1177/1753193418786947
- The effect of night extension orthoses following surgical release of Dupuytren contracture: a single-centre RCT. J Hand Surg Am. 2013. DOI: 10.1016/j.jhsa.2013.04.012
- Comparison of hand therapy with or without splinting postfasciectomy for Dupuytren's contracture: systematic review and meta-analysis. J Hand Microsurg. 2022. DOI: 10.1055/s-0041-1725221
- Does use of a night extension orthosis improve outcomes in patients with Dupuytren contracture? J Hand Surg Glob Online. 2021. DOI: 10.1016/j.jhsg.2021.05.001
- A pilot study assessing the effectiveness of postoperative splinting after limited fasciectomy. J Hand Surg Eur. 2012. DOI: 10.1177/1753193412437631
- Pre-operative hand therapy management of Dupuytren's disease: a systematic review. Hand Ther. 2024. DOI: 10.1177/17589983241227162
- Current concepts in the management of Dupuytren disease of the hand. J Am Acad Orthop Surg. 2020. DOI: 10.5435/JAAOS-D-20-00190
- Complications after treating Dupuytren's disease: a systematic literature review. Hand Surg Rehabil. 2017. DOI: 10.1016/j.hansur.2017.07.002
- Surgical complications: errors and adverse events (hand surgery). J Hand Surg Eur. 2023. DOI: 10.1177/17531934231206317
- The case of a woman with bilateral Dupuytren's contractures who developed CRPS-1. J Hand Ther. 2024. DOI: 10.1016/j.jht.2024.09.002
- Complex regional pain syndrome after hand surgery. Hand Clin. 2009. DOI: 10.1016/j.hcl.2009.11.001
Splinting & hand-therapy literature (URLs)
- Jerosch-Herold C, Shepstone L, Chojnowski AJ, et al. Night-time splinting after fasciectomy or dermo-fasciectomy for Dupuytren's contracture: a pragmatic, multi-centre, randomised controlled trial. BMC Musculoskelet Disord. 2011;12:136. https://pmc.ncbi.nlm.nih.gov/articles/PMC3146906/
- Collis J, Collocott S, Hing W, Kelly E. The effect of night extension orthoses following surgical release of Dupuytren contracture: a single-centre, randomised, controlled trial. J Hand Surg Am. 2013. https://pubmed.ncbi.nlm.nih.gov/23790420/
- Karam M, Kahlar N, Abul A, et al. Comparison of hand therapy with or without splinting postfasciectomy for Dupuytren's contracture: systematic review and meta-analysis. J Hand Microsurg. 2022. https://pmc.ncbi.nlm.nih.gov/articles/PMC10042625/
- Blake SN, Poelstra R, Andrinopoulou ER, et al. Return to work and associated costs after treatment for Dupuytren's disease. Plast Reconstr Surg. 2021. https://pubmed.ncbi.nlm.nih.gov/34292887/
- Radhamony NG, Nair RR, Sreenivasan S, et al. Residual deformity versus recurrence following Dupuytren's palmar fasciectomy — long-term follow-up of 142 cases. Ann Med Surg. 2022. https://pmc.ncbi.nlm.nih.gov/articles/PMC8767281/
- Scott HC, Robinson LS, Brown T. Scar massage as an intervention for post-surgical scars: a practice survey of Australian hand therapists. Hand Ther. 2024. https://pmc.ncbi.nlm.nih.gov/articles/PMC10901164/
Society guidance & published rehab protocols
- The British Society for Surgery of the Hand (BSSH) — Dupuytren's disease patient and professional guidance. https://www.bssh.ac.uk/patients/conditions/25/dupuytrens_disease
- BSSH — Assessing the outcome of surgery for Dupuytren's disease of the hand. https://www.bssh.ac.uk/assessing_the_outcome_of_surgery_for_dupuytrens_disease_of_the_hand.aspx





