

近端指间关节置换术 资料
本方案指导您在手指中间关节置换术(近端指间关节(PIP)关节,即中间指节)植入柔性硅胶间隔物后的康复过程,该手术由 Mater Private Hospital Rockhampton 的 Kieran Hirpara 医生实施。方案首先介绍您的居家锻炼计划,随后是为您手部治疗师撰写的结构化临床方案。请在首次治疗就诊时携带此页面或其 PDF 文件,以确保您的康复过程协调一致。您的治疗师可能会根据康复进展调整计划。
如果您对术后伤口有任何疑虑,请联系诊所。通常,拍摄伤口照片并通过电子邮件发送以供审阅会很有帮助。
预期情况
您的手指中间关节因关节炎而磨损,导致疼痛和僵硬。在此手术中,磨损的关节面将被移除,并在两块骨头之间放置一个柔性硅胶间隔物(Swanson 型植入物)。该间隔物并非刚性机械铰链;它是一个可弯曲的间隔物,用于保持骨骼分离,允许手指弯曲,并让您自身的瘢痕组织在其周围形成新的支撑袖套。主要且最可靠的益处是缓解疼痛。您还应预期获得有用的、适度的弯曲范围(通常在 40 到 60 度左右),而非完全正常的活动范围。大多数人非常满意,因为疼痛消失了,手指使用起来也很舒适。
关于您的康复,最重要的一点是外科医生采用的入路方向,因为这决定了您何时可以开始活动:
- 从前方(手掌侧,掌侧入路): 手指背侧的伸肌腱保持完全完整。由于背侧无需愈合,您通常可以在几天内开始活动手指。
- 从后方(背侧入路): 伸肌腱(中央腱)必须被切开或抬起以到达关节,然后进行修复。该修复最初需要保护,因此早期手指需伸直位夹板固定,并在您的手部治疗师指导下更逐渐地引入弯曲动作。
您的手部治疗师将按照您手术入路的计划进行指导。 Hirpara 医生会告知他们使用了哪种入路,以下时间安排是根据该入路定制的。无论您接受的是哪种入路,新的关节都是一个铰链:它喜欢沿直线弯曲和伸直,但不喜欢被侧向推压或扭转。保护其免受侧向应力是长期保持其稳定的关键。
注意事项与限制
- 仅沿直线移动手指(屈曲和伸直),并避免对手术手指施加任何侧向或扭转力。新关节为铰链结构,侧向应力可能导致其松动或变形。
- 按指示佩戴夹板,并在活动时使用邻指固定带以保持手指沿直线运动。
- 如果手术是从手指背侧进行的,早期切勿将手指伸直超过规定的限度:伸直肌腱正在愈合。
- 在手部治疗师允许进行强化训练之前(通常约为术后六周起),切勿进行用力抓握、强力捏持或沉重或扭转的任务。
- 从一开始就保持其他手指关节、手腕和肩部的活动,并在舒适范围内用手进行轻度日常活动。
关于伤口、肿胀和瘢痕管理,请参阅本诊所的伤口护理指南。
您的练习
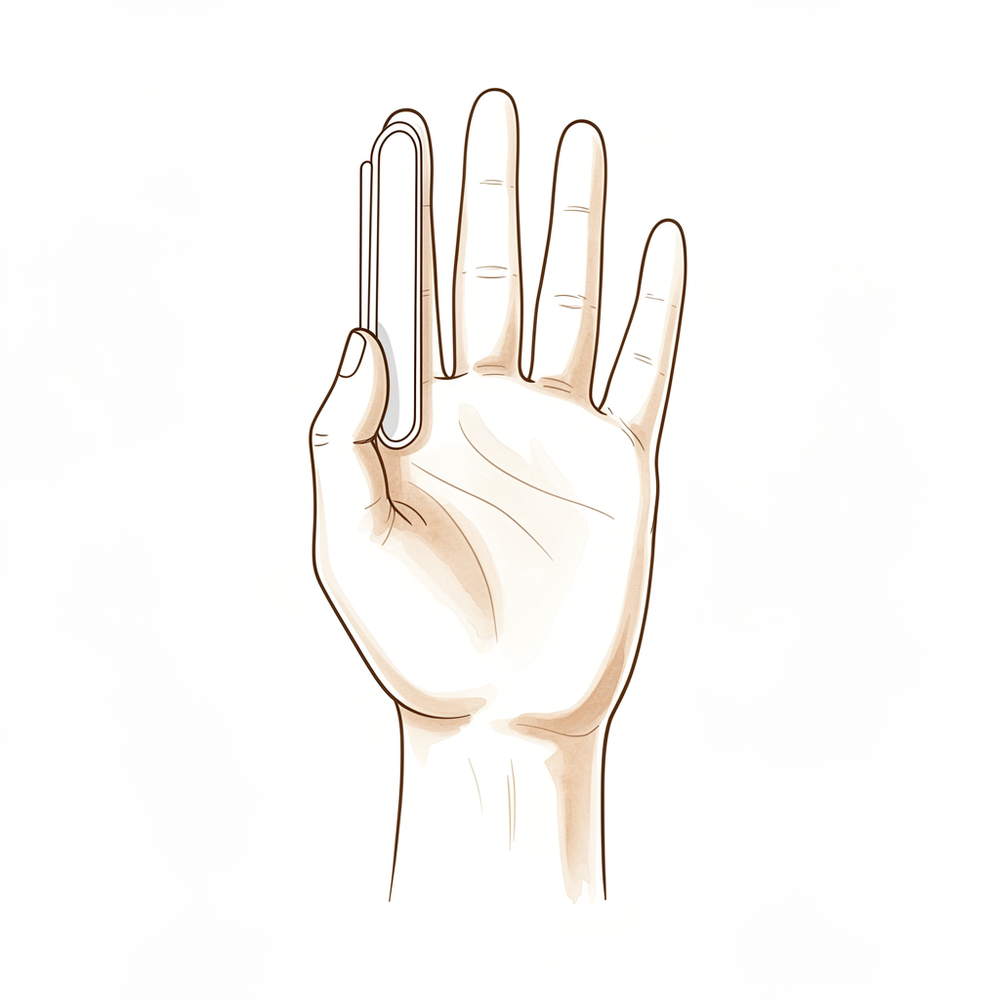
Kieran Hirpara 4.0
受保护的主动屈曲(近端指间关节)
用其余手指和夹板支撑手部其余部分,在您的手部治疗师设定的活动范围内,轻轻弯曲和伸直手指的已手术中间关节。保持动作缓慢且笔直——沿一条清晰的直线进行弯曲和伸直,不要让手指向一侧偏移。这能保持新关节的活动度,防止其僵硬。
10次,每天数次,在您设定的范围内
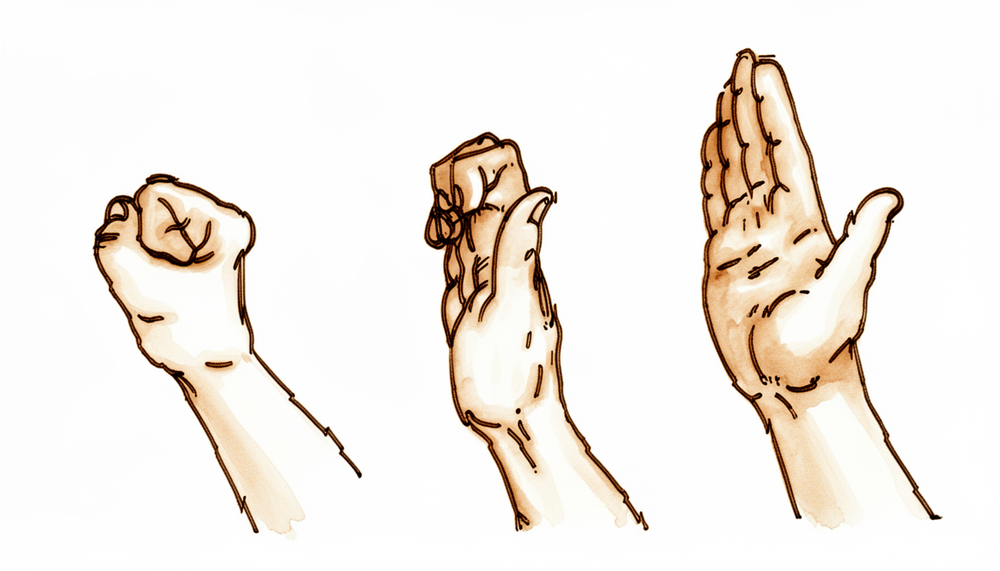
Kieran Hirpara 4.0
主动伸直(伸展)
尽可能轻柔地将手术手指完全伸直,然后放松。如果您的手术是从手指背面进行的,这是早期需要保护的动作——您的手部治疗师将指导您具体做多少以及何时做,因为伸直肌腱需要先愈合。切勿强行操作。
10次,每天数次,遵医嘱
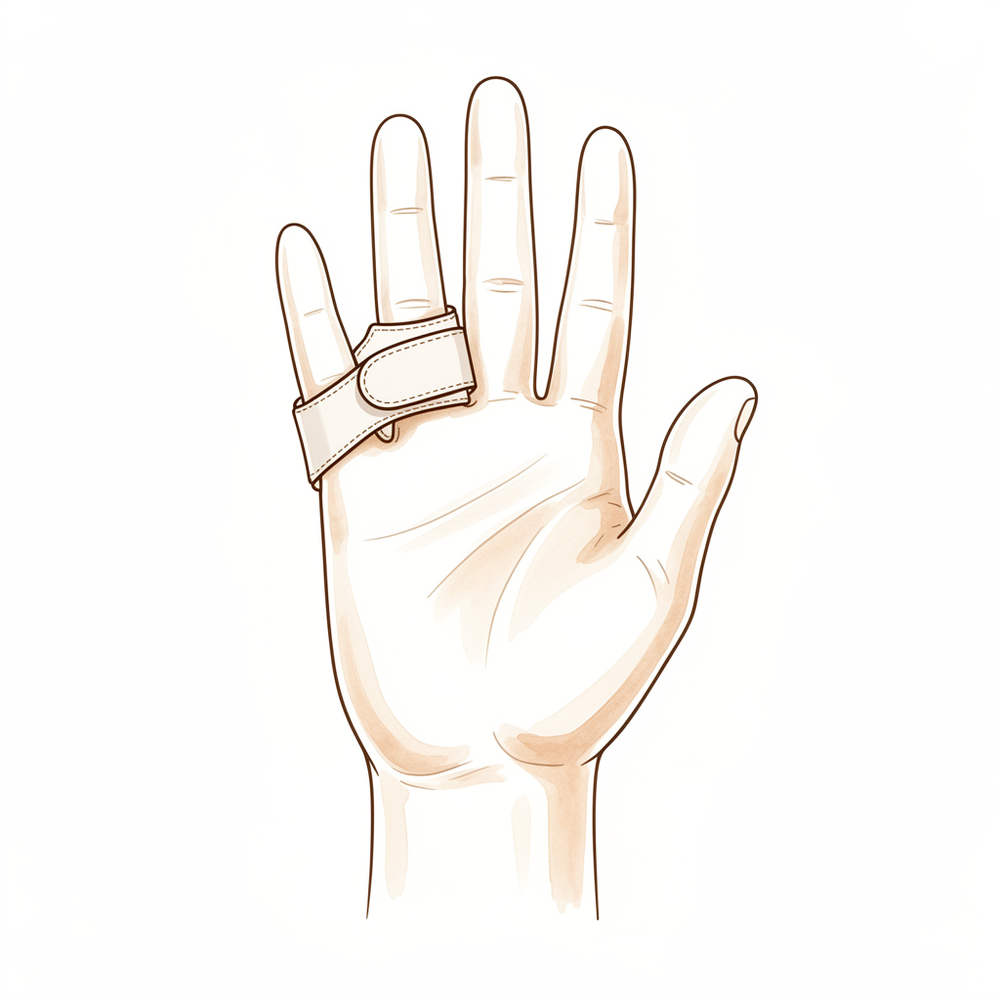
Kieran Hirpara 4.0
邻指固定
将手术手指轻柔地固定于相邻手指(固定于中间关节的上方和下方,而非覆盖关节本身)。相邻手指起到夹板的作用,引导您的手指沿直线弯曲和伸直,并防止其向侧方倾斜至新关节上。请遵医嘱在活动时佩戴。
在轻度活动期间佩戴,具体请遵循您的手部治疗师的指导
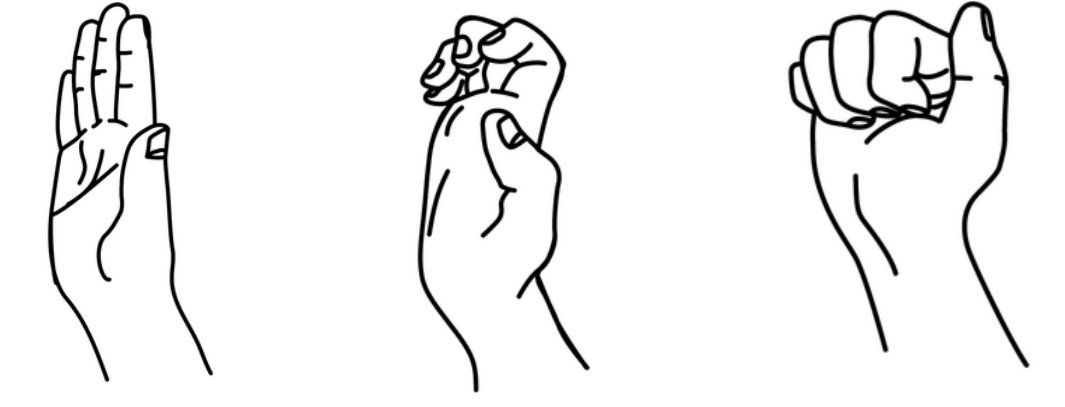
Kieran Hirpara 4.0
腱滑动
将手依次做三种形态:手指伸直(平手),然后仅弯曲末端两个关节呈钩状,再轻轻握成完整拳头,最后再次伸直。此动作可使肌腱顺畅滑动,防止手指愈合过程中发生粘连。请严格在您被规定的屈曲限制范围内进行。
整套动作做5–10遍,每天数次

Kieran Hirpara 4.0
瘢痕按摩
待伤口完全愈合后,取少量无添加乳霜按摩瘢痕,以小而坚定的圆圈动作持续数分钟。此举可保持瘢痕柔软,防止其与下方的肌腱和关节发生粘连。请勿开始按摩,直至您的手部治疗师确认伤口已愈合。
每天 2–3 次,每次几分钟,待伤口愈合后

Kieran Hirpara 4.0
握力强化
后期练习——仅在手部治疗师确认可进行强化训练后方可开始(通常从约六周起)。轻轻挤压软球或橡皮泥,逐步增加强度。在被告知安全之前,避免用力捏持或任何会对新关节施加侧向力的扭转动作。
在您的手部治疗师指导下(仅限后期阶段)
这些是您的手册中列出的练习。请仅在Hirpara医生和您的手部治疗师的指导下开始这些练习,并严格保持在您被允许的范围内和限制内。早期的练习旨在让手指沿直线活动,避免侧向应力:包括保护性屈曲、轻柔伸直、 buddy 绑带固定以及肌腱滑动。如果您的手术是从手指背侧进行的,主动伸直练习是早期需要保护并缓慢建立的项目。握力强化属于后期阶段,在获得明确许可之前不应开始。停止任何引起剧烈疼痛或使手指感觉不稳定的活动。
您的临床方案
本页其余部分为硅胶掌指关节(PIP)关节置换术后康复的分阶段临床方案。本节内容应提供给您的手部治疗师,每个阶段均以通俗易懂的语言解释当前正在发生的情况。该方案取决于手术入路,这是核心分支点:掌侧(掌面)入路保持伸肌装置完整,允许在数天内进行早期主动活动;背侧入路会切断或劈开中央腱,因此必须首先通过伸指支具和分级屈曲来保护伸肌愈合。在整个过程中,硅胶植入物是一个柔性间隔器,其长期稳定性依赖于植入物周围囊,因此避免冠状面(侧向)应力,并将活动保持在纯矢状面弧内。
在治疗前,请与主刀外科医生确认手术入路(掌侧或背侧)、中央腱和侧副韧带的完整性/修复情况,以及术中活动范围。Hirpara 医生将指定入路;相应地选择掌侧(早期主动活动)或背侧(伸指保护)路径。预期的功能目标是约 40–60° 的无痛活动范围,而非全范围活动。
第一阶段 — 保护并启动活动(第 0 至 3 周)
最初几周旨在保护软组织,同时防止僵硬,进度完全由手术入路决定。植入物在屈伸方向上稳定,但易受侧向载荷影响,因此所有活动均保持在纯净的矢状面内,手指通过邻指绑带和支具进行支撑。
致您的手部治疗师:
宣教与注意事项 - 识别手术入路并遵循相应的康复路径: - 掌侧入路: 伸肌装置完整 → 在 3–5 天开始主动 PIP/DIP 关节活动。佩戴掌侧伸肌阻挡/模板支具,允许较短的屈曲弧度(通常初始约为 30°),并逐步增加。 - 背侧入路(中央滑车切开/修复): 保护伸肌功能。PIP 关节全天佩戴支具固定于接近完全伸直位;在监督下引入有限短弧度的主动屈曲,尊重中央滑车修复情况。(可根据外科医生偏好使用相对运动/动态伸肌方案。) - 严格避免对手术关节施加冠状面(外侧/桡侧–尺侧)应力:使用邻指绑带固定于相邻手指,以引导纯矢状面轨迹。 - 禁止抓握、捏持或抗阻/负重使用。
管理 - 伤口:按指示使用外科敷料;监测感染迹象 - 水肿:抬高患肢、轻柔的逆向按摩、轻度加压包扎 - 练习:在设定弧度内进行受保护的主动 PIP/DIP 屈伸活动;肌腱滑动练习;未受累关节(DIP、MCP、腕部、拇指)的主动活动;开始进行活动时的邻指绑带固定 - 在练习间隙全天佩戴支具
晋级标准 - 伤口愈合良好;未出现伸肌滞后(背侧路径);在当前弧度内活动舒适且可控
第二阶段 — 活动度进阶(第3至6周)
屈曲活动范围逐渐打开;对于经背侧入路的手指,随着中央滑车的愈合巩固,伸肌保护将逐步放松。此阶段的目标是在瘢痕成熟固定活动范围之前,储备有效的屈曲活动度(≈40–60°)。
致您的手部治疗师:
评估 - 主动和被动掌指关节(PIP)活动范围;伸肌滞后(背侧通路);冠状面稳定性;疼痛与水肿;伤口/瘢痕复查
宣教与注意事项 - 逐步增加允许的屈曲活动范围,直至达到功能目标(≈40–60°) - 掌侧入路: 在可耐受范围内推进主动屈曲;若伸肌功能完全且稳定,可加入轻柔的被动屈曲 - 背侧入路: 根据中央滑愈合情况逐步停用伸肌支具(通常在第4–6周期间逐步撤除日间支撑);警惕伸肌滞后:切勿以牺牲主动伸肌功能为代价去追求屈曲 - 继续严格避免侧向/扭转负荷;暂不进行抗阻强化训练
处理措施 - 练习:分级主动及主动辅助的掌指关节(PIP)屈伸运动;使用阻挡练习以聚焦掌指关节(PIP)活动;继续肌腱滑动练习及邻指绑带固定;伤口愈合后开始瘢痕按摩 - 维持邻近关节的全范围活动
进阶标准 - 伤口愈合;冠状面关节稳定;已建立无痛的功能性活动范围;伸肌滞后极小(背侧入路)
第三阶段 — 强化与恢复(第6至12周及以后)
一旦活动度建立且软组织状态良好(约6周时),开始轻度强化训练并逐步增加强度。强化训练保持轴向(抓握和直线负荷),同时长期尊重对植入物的侧向/扭转应力。
致您的手部治疗师:
评估 - 抓握力和捏力与对侧比较;最终PIP关节活动范围;冠状面稳定性;功能性及任务特异性测试
教育与注意事项 - 从约6周开始进行轻度抓握强化,并逐步增加强度 - 谨慎引入捏力负荷,并无限期避免对手术关节施加强烈的侧向/扭转负荷(以延长植入物寿命) - 设定现实预期:持久的疼痛缓解是主要获益;最终活动范围有限(≈40–60°),且主要在约3个月时确定
管理 - 练习:渐进性抓握/橡皮泥训练;分级功能性和工作特异性负荷;继续任何残留的活动度和瘢痕处理 - 一旦达到稳定、舒适、功能良好的手指,且具有有用的无痛活动范围,可考虑出院 - 如果恢复停滞、关节变得不稳定/偏斜,或怀疑植入物失效,请转回主治医生处
出院/复诊标准 - 关节舒适、无痛、冠状面稳定,具有功能性活动范围;抓握力充足;能够满足日常和工作需求
重返工作与活动
鼓励从初期开始进行轻度日常手部使用(如进食、书写、轻度自我护理),以舒适为限,前提是手指保持直线,并避免对手术手指施加侧向或扭转力。通常,一旦您能舒适地握住方向盘并安全控制车辆,已脱离任何限制性夹板,且不再服用强效止痛药,即可驾驶,这通常需要几周时间,并在复诊时予以确认。
较紧的抓握和负重任务需等到约六周后,随后逐步增加。较重的体力劳动或扭转工作是最后恢复的项目,其恢复标准是重新获得舒适、稳定的手指及足够的抓握力,由Hirpara医生和您的手部治疗师评估决定,而非仅依据日历时间。请记住此次手术的长期目标:可靠的疼痛缓解以及约40至60度的有效活动范围,并长期避免对关节施加侧向应力,以保护植入物。
您的方案之后
本方案与本诊所的一般康复建议配合使用;请参阅术后疼痛管理、伤口护理和疤痕管理。上述分阶段计划反映了硅胶指间关节置换术后已发表的康复指南,您的持续康复将由Hirpara医生和您的手部治疗师根据所使用的手术入路及手指恢复情况,进行个体化指导。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: post-operative rehabilitation after silicone (Swanson-type) proximal interphalangeal (PIP) joint arthroplasty for primary osteoarthritis. The worn joint surfaces are excised and a flexible silicone spacer is implanted; this is an interposition / encapsulation arthroplasty, not a rigidly-fixed mechanical hinge. The implant works as a flexible spacer around which a peri-implant fibrous capsule forms to provide stability. The dominant, reliable benefit is pain relief; the functional gain is a modest active arc (~40–60°), not restoration of normal range.
Defining principle of the rehab here: the rehabilitation pathway is dictated by the surgical approach, because the rate-limiting tissue is the extensor mechanism, not the implant. A volar (palmar) approach leaves the central slip and extensor mechanism intact → it permits immediate / early active motion (within 3–5 days). A dorsal approach must split or reflect the central slip to reach the joint → the extensor repair must be protected first with extension orthotics and a graded, short-arc flexion programme. Across both pathways the silicone spacer is stable in the sagittal (flexion–extension) plane but vulnerable in the coronal plane, so the programme deliberately avoids lateral / torsional load and tracks the joint in a pure sagittal arc (buddy strapping). Therapy aims to bank the useful arc before scar maturation fixes it while protecting extension and the implant — it is not an immobilise-to-heal construct in the volar case.
A. PROCEDURE OUTCOMES (silicone PIP arthroplasty for osteoarthritis)
Silicone PIP arthroplasty is a reliable pain-relieving operation with predictable but modest motion; the principal debates are over surgical approach and implant choice (silicone vs surface-replacement/pyrocarbon), not whether arthroplasty relieves pain.
- Pain relief is high and durable; motion gains are modest. A long-term series of Swanson silicone PIP arthroplasty for osteoarthritis (mean ~10-year follow-up) reported excellent pain relief (mean VAS ~0.4) with essentially unchanged arc (≈55° pre-op → ≈50° post-op) and high patient satisfaction — patients would have the surgery again despite limited motion gain [Bales, Wall & Stern, J Hand Surg Am 2014]. Moderate (level-IV long-term cohort).
- The volar approach can improve the active arc. A volar-approach silicone PIP series reported the active arc improving from ~33° to ~72°, with good function and satisfaction, by preserving the extensor mechanism and enabling early motion [Proubasta et al., J Hand Surg Am 2014]. Moderate–weak (level-IV).
- Radiographic implant deformation/fracture is common but poorly correlated with symptoms. In the long-term Swanson series most implants deformed and many fractured radiographically, yet clinical revision was uncommon (survivorship ~90% at ~10 years) and there was no correlation between radiographs and satisfaction [Bales, Wall & Stern 2014]. Strong natural-history signal within a cohort.
- Silicone vs surface-replacement and pyrocarbon implants give broadly comparable clinical results; no implant is clearly superior. Systematic review across implants/approaches found comparable outcomes with implant-/approach-specific complication profiles [Yamamoto et al., Plast Reconstr Surg 2017; Carlson Strother, Moran & Rizzo, JAAOS 2023]. Moderate (SR + narrative review).
- Pyrocarbon and resurfacing implants carry their own failure modes (subsidence, squeaking, intra-operative periprosthetic fracture, instability), informing implant choice rather than rehab [Watts et al., J Hand Surg Am 2012; Wagner et al. medium-term 2018 & intra-op fractures 2015; Branam et al. resurfacing-vs-silicone 2007]. Moderate.
B. REHABILITATION / THERAPY EVIDENCE
The central rehab questions are (1) how soon to move and (2) how to splint, and the answer to both is set by the surgical approach and the extensor mechanism. The evidence base is low-level (expert consensus / single-cohort therapy series) — there are no RCTs comparing PIP arthroplasty rehab pathways.
- Approach dictates the timeline (the core principle). Surgical reviews establish that a volar approach preserves the central slip and permits immediate active and passive motion, while a dorsal approach requires post-operative protection of the split/repaired central slip before flexion is advanced [Renfree, Bone Joint J 2022 (surgical approaches); Herren, Hand Clin 2017; Yamamoto et al. 2017]. Moderate (surgical evidence) — strong mechanistic basis.
- A structured 12-week, splint-based therapy programme is the consensus framework (dorsal pathway). Feldscher's hand-therapy protocol for PIP (pyrocarbon, central-slip-splitting dorsal approach) uses a volar static finger orthosis allowing a limited short-arc PIP/DIP active arc that is increased over the rehab course, with a hand-based resting splint (MCP flexed, PIP/DIP near 0°) for full-time use except during template-splint exercise [Feldscher, J Hand Ther 2010]. Weak (expert-consensus protocol).
- A defined controlled-motion program exists and reports good arcs. A controlled-motion rehabilitation program for PIP arthroplasty reported favourable range-of-motion outcomes, supporting graded controlled motion over rigid immobilisation [Ramanathan, Koludrovich & Evans, J Hand Ther 2021]. Weak (cohort / programme description).
- Static and dynamic extension splinting give similar results. A comparison of static vs dynamic splinting after PIP pyrocarbon arthroplasty found comparable outcomes, favouring static splinting for simplicity and patient convenience [Jennings & Livingstone / static-vs-dynamic cohort, J Hand Ther 2011]. Weak–moderate (comparative cohort).
- Coronal-plane protection is the durable, lifelong caveat. Collateral integrity and avoidance of lateral stress underpin long-term implant stability; collateral compromise drives instability/deviation [Carlo et al., collateral reconstruction, J Hand Surg Am 2016; Carlson Strother et al. 2023]. Consensus / mechanistic.
Recovery trajectory (expected, evidence-anchored)
| Phase | Window | Restraint (by approach) | Hand-therapy focus | Strength / load | Notes |
|---|---|---|---|---|---|
| I — Protect & initiate motion | Week 0–3 | Volar: active motion at 3–5 days, short flexion arc (~30°) in template/extension-block splint. Dorsal: PIP splinted near extension full-time; supervised short-arc flexion only | Protected sagittal PIP/DIP motion; tendon glides; buddy strapping; uninvolved-joint motion; no lateral/torsional load | None (no grip/pinch) | Implant stable in flexion–extension, vulnerable coronally |
| II — Advance motion | Week 3–6 | Progressively increase flexion arc toward ~40–60°. Dorsal: wean extension splint as central slip consolidates (≈wk 4–6); guard against extensor lag | Graded active/AAROM flexion–extension; blocking; scar massage once healed; continue buddy strapping | Still no resisted strengthening | Bank the useful arc before scar maturation fixes it |
| III — Strengthen & return | Week 6–12+ | Lifting/grip restrictions progressively lifted; lateral/twisting load avoided indefinitely | Light grip → cautious pinch; functional & work-specific loading | Grip from ~6 wk, graded | Pain relief is the durable gain; final arc (~40–60°) largely set by ~3 months |
(Phase windows mirror the precautions in the patient protocol; they are typical guides — not trial-derived deadlines — and the volar vs dorsal split is the dominant variable.)
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Volar vs dorsal approach (the rehab-defining question). The volar approach spares the extensor mechanism and permits early active motion (and a better reported arc), at the cost of being more technically demanding; the dorsal approach is more familiar but mandates extensor protection and a slower, splint-led flexion programme. Choice is surgeon-dependent and drives the entire rehab pathway. Moderate surgical evidence; no head-to-head rehab RCT.
- Implant choice (silicone vs surface-replacement vs pyrocarbon). No implant is clearly superior on clinical outcomes; silicone is durable for pain relief with high radiographic deformation/fracture that poorly predicts symptoms, while pyrocarbon/resurfacing trade different complication profiles (subsidence, instability, intra-operative fracture). Moderate (SR + cohorts).
- Static vs dynamic splinting (dorsal pathway). Comparable outcomes; static splinting is favoured for simplicity and convenience. Weak–moderate.
- Motion gain is modest and that is expected, not failure. Patients reliably lose pain but gain little arc (especially via dorsal/silicone); mislabelling the modest arc as a poor result misframes a successful pain-relieving operation. Counsel the ~40–60° expectation up front. Strong natural-history signal.
- Lifelong coronal-stress avoidance. Long-term stability depends on the peri-implant capsule and collaterals; forceful lateral/twisting load risks deviation, instability and implant failure. Consensus.
D. EVIDENCE STRENGTH FLAGS (summary)
- STRONG (mechanistic / natural-history): the surgical-approach principle (volar preserves extensor mechanism → early motion; dorsal splits central slip → protect extension first); the modest-arc / reliable-pain-relief outcome pattern; radiographic implant deformation poorly predicting symptoms.
- MODERATE: procedure outcomes are level-IV case series (long-term Swanson silicone series; volar approach series); implant-comparison systematic review/narrative review; surgical-approach reviews.
- WEAK / EXPERT CONSENSUS: the specific rehabilitation regimen — short-arc controlled motion, 12-week splint-based programme, static-vs-dynamic splinting equivalence, exact phase timings. These are low-level, expert-consensus / single-cohort therapy descriptions, not trial-derived; individualise to the operative approach and tissue quality.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Bales JG, Wall LB, Stern PJ. Long-term results of Swanson silicone arthroplasty for proximal interphalangeal joint osteoarthritis. J Hand Surg Am. 2014. DOI: 10.1016/j.jhsa.2013.11.008
- Proubasta IR, Lamas CG, Natera L, et al. Silicone proximal interphalangeal joint arthroplasty for primary osteoarthritis using a volar approach. J Hand Surg Am. 2014;39(6). DOI: 10.1016/j.jhsa.2014.03.033
- Weistra K, Kan HJ, van Alebeek VAHJ, et al. Proximal interphalangeal joint arthroplasty using a silicone implant: a comparison between Integra and NeuFlex in 72 cases. HAND. 2022. DOI: 10.1177/15589447221122829
- Branam BR, Tuttle HG, Stern PJ, et al. Resurfacing arthroplasty versus silicone arthroplasty for proximal interphalangeal joint osteoarthritis. J Hand Surg Am. 2007. DOI: 10.1016/j.jhsa.2007.04.006
- Yamamoto M, Malay S, Fujihara Y, et al. A systematic review of different implants and approaches for proximal interphalangeal joint arthroplasty. Plast Reconstr Surg. 2017. DOI: 10.1097/prs.0000000000003260
- Renfree KJ. Surgical approaches for proximal interphalangeal joint arthroplasty. Bone Joint J. 2022;104-B(12). DOI: 10.1302/0301-620x.104b12.bjj-2022-0946
- Herren DB. Current European practice in the treatment of proximal interphalangeal joint arthritis. Hand Clin. 2017. DOI: 10.1016/j.hcl.2017.04.002
- Carlson Strother CR, Moran SL, Rizzo M. Small joint arthroplasty of the hand: an update on indications, outcomes, and complications. J Am Acad Orthop Surg. 2023;31(15). DOI: 10.5435/jaaos-d-23-00034
- Feldscher SB. Postoperative management for PIP joint pyrocarbon arthroplasty. J Hand Ther. 2010. DOI: 10.1016/j.jht.2009.10.011
- Ramanathan D, Koludrovich J, Evans P. A new controlled motion program for rehabilitation of the proximal interphalangeal joint arthroplasty. J Hand Ther. 2021. DOI: 10.1016/j.jht.2019.04.003
- Watts AC, Hearnden AJ, Trail IA, et al. Pyrocarbon proximal interphalangeal joint arthroplasty: minimum two-year follow-up. J Hand Surg Am. 2012. DOI: 10.1016/j.jhsa.2012.02.012
- Wagner ER, Weston JT, Houdek MT, et al. Medium-term outcomes with pyrocarbon proximal interphalangeal arthroplasty: a study of 170 consecutive arthroplasties. J Hand Surg Am. 2018. DOI: 10.1016/j.jhsa.2018.06.020
- Wagner ER, Van Demark R, Kor DJ, et al. Intraoperative periprosthetic fractures in proximal interphalangeal joint arthroplasty. J Hand Surg Am. 2015. DOI: 10.1016/j.jhsa.2015.06.101
- McGuire DT, White CD, Carter SL, et al. Pyrocarbon proximal interphalangeal joint arthroplasty: outcomes of a cohort study. J Hand Surg Eur Vol. 2011;37(6). DOI: 10.1177/1753193411434053
- Carlo J, Dell PC, Matthias R, et al. Collateral ligament reconstruction of the proximal interphalangeal joint. J Hand Surg Am. 2016;41(1). DOI: 10.1016/j.jhsa.2015.10.007
- Aversano FJ, Calfee RP. Salvaging a failed proximal interphalangeal joint implant. Hand Clin. 2018. DOI: 10.1016/j.hcl.2017.12.011
PIP arthroplasty rehabilitation literature (URLs)
- Feldscher SB. Postoperative management for PIP joint pyrocarbon arthroplasty. J Hand Ther. 2010. https://pubmed.ncbi.nlm.nih.gov/20036511/
- Ramanathan D, Koludrovich J, Evans P. A new controlled motion program for rehabilitation of the proximal interphalangeal joint arthroplasty. J Hand Ther. 2021. https://pubmed.ncbi.nlm.nih.gov/31481342/
- Static versus dynamic splinting for proximal interphalangeal joint pyrocarbon implant arthroplasty: a comparison of current and historical cohorts. J Hand Ther. 2011. https://pmc.ncbi.nlm.nih.gov/articles/PMC3143198/
- Proubasta IR, et al. Silicone proximal interphalangeal joint arthroplasty for primary osteoarthritis using a volar approach. J Hand Surg Am. 2014. https://pubmed.ncbi.nlm.nih.gov/24799141/
- Bales JG, Wall LB, Stern PJ. Long-term results of Swanson silicone arthroplasty for PIP joint osteoarthritis. J Hand Surg Am. 2014. https://pubmed.ncbi.nlm.nih.gov/24559624/
- The dorsal approach to silicone implant arthroplasty of the proximal interphalangeal joint. J Hand Surg Am. 2007. https://www.sciencedirect.com/science/article/abs/pii/S0363502307004662
- Proximal interphalangeal joint arthroplasty using a silicone implant: a comparison between Integra and NeuFlex. HAND. 2022. https://pmc.ncbi.nlm.nih.gov/articles/PMC10953532/





