

腕关节融合术 资料
本方案指导您在 Mater Private Hospital Rockhampton 接受 Kieran Hirpara 医生进行的全腕关节融合术(又称腕关节融合术,该手术将磨损的腕关节永久固定,使其不再活动)后的康复过程。方案首先介绍您的居家锻炼计划,随后是专为您的手部治疗师编写的结构化临床方案:请在首次治疗就诊时携带此页面或其 PDF 文件,以确保您的康复过程协调一致。您的治疗师可能会根据康复进展调整计划。
如果您对术后伤口有任何疑虑,请联系病房。通常,拍摄伤口照片并通过电子邮件发送以供审查会很有帮助。
预期情况
腕关节全融合术适用于所有关节均磨损(终末期或“全腕骨”关节炎)且活动时疼痛的腕关节。手术并非试图保留磨损关节的活动度,而是有意消除活动度:通过沿腕背侧放置的背侧钢板,将前臂骨(桡骨)与手部骨骼(掌骨)连接起来,使腕关节牢固地固定在轻微后伸(轻度背伸)的位置,该位置最有利于抓握。在接下来的几周内,骨骼将愈合(融合)成一个坚固的整体。
此次康复的关键理念与大多数手术相反:腕关节停止活动是预期目标:这是治愈,而非并发症。 因此,没有恢复腕关节活动度的目标,也没有弯曲或伸直腕关节的锻炼。相反,整个康复过程保护的是融合术未涉及且对手部功能至关重要的两个方面:
- 手指和拇指必须保持完全的活动能力。 手指僵硬是导致腕关节融合术效果不佳的主要原因,因此手指和拇指的活动从第一天开始。
- 前臂旋转(手掌向上和向下翻转)得以保留。 融合术不涉及此运动,它接管了腕关节原本承担的许多功能(如拧钥匙、按门铃和转门把手),因此从一开始就保持其灵活性。
由于背侧钢板牢固地固定骨骼(稳定固定),在骨骼愈合期间需佩戴支具约六周,并鼓励早期进行手指和前臂活动,而非限制。一旦外科医生确认骨愈合,即可开始抓握力量训练。许多人在腕关节融合术后功能恢复良好,且由于抓握不再疼痛,抓握力量通常比术前疼痛的腕关节有所改善。
注意事项与限制
- 切勿尝试活动腕关节本身:该关节在设计上已牢固融合。现在或将来均无腕关节屈伸练习。
- 务必从第一天起就充分活动手指、拇指及前臂旋转:这是您能为手部做的最重要的一件事。
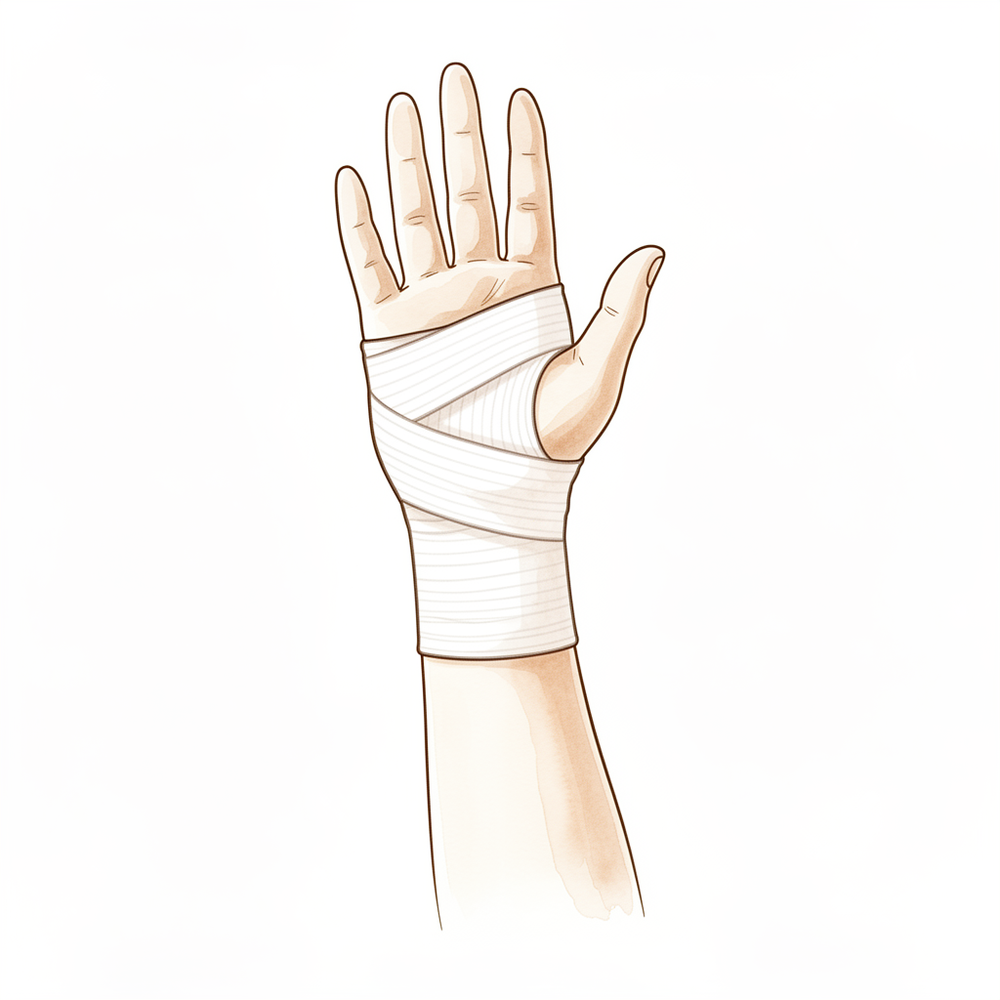
- 按照指示佩戴支具或敷料,以保持舒适并保护关节,直至骨骼愈合;请保持其清洁干燥。
- 切勿负重或用力抓握,并避免提起超过轻杯重量的物品,直至融合愈合且获得许可(通常在六至八周左右):在愈合前进行重度负重可能导致钢板或融合失败。
- 切勿在佩戴支具期间或无法安全控制车辆时驾驶;一旦您拆除支具且能操控方向盘,并经复查确认后,即可恢复驾驶。
关于伤口、肿胀及疤痕管理,请参阅本诊所的伤口护理指南。
您的练习

Kieran Hirpara 4.0
手指和拇指运动
从术后最初几天起,请保持手指和拇指充分活动。先握紧拳头,然后张开手掌,将手指完全伸直;接着依次用拇指触碰每个手指的指尖。您的手腕不会活动——这是正常且符合预期的——但手指和拇指必须保持松弛且完全灵活,因为僵硬是腕关节融合术后限制手部功能的主要因素。
各10次,每天数次,从第一天起

Kieran Hirpara 4.0
前臂旋转(掌心向上 / 掌心向下)
将肘部紧贴身体一侧并弯曲成直角,轻轻将手掌向上转向天花板,然后向下转向地板。融合手术不涉及这些旋转动作,因此它们保持自由——保持其柔韧性很重要,因为前臂的旋转承担了原本由手腕完成的许多工作(如转动钥匙、门把手、水龙头)。
每个方向10次,每天2–3次
Kieran Hirpara 4.0
肿胀控制
在最初的一两周内,无论您是坐着还是躺着,都应将手枕在枕头上,使其抬高至心脏水平以上,并轻柔地做手指的屈伸活动。此举有助于引流手部手术后必然出现的肿胀;肿胀减轻后,手指活动会更加自如,伤口也会更快愈合。
休息时抬高患肢;清醒状态下每小时进行10次手指泵运动

Kieran Hirpara 4.0
瘢痕护理
伤口完全愈合且无痂皮后,取少量润肤霜,以小而有力的画圈方式按摩手腕背侧的瘢痕。此举可保持瘢痕柔软,并防止其与下方的钢板及肌腱粘连。您的手部治疗师会在适当时机开始指导此操作。
几分钟,每天 2–3 次,愈合后

Kieran Hirpara 4.0
骨性愈合后的握力强化
后期锻炼——仅在骨融合愈合(通常约六至八周)且获得许可后进行。用掌心挤压软球或治疗用橡皮泥,保持后松开。融合后的腕部为手部提供了稳定且无痛的抓握基础,因此抓握力通常在随后的数月内逐渐增强。请循序渐进地进行训练。
10–15次挤压,每天2–3次,骨性愈合并获准后进行
这些是您的手册中列出的练习。请仅在Hirpara医生和您的手部治疗师的指导下开始进行。早期的所有练习都旨在保护融合术后保留的活动功能(手指和拇指运动、前臂旋转以及肿胀控制),且均不涉及手腕,因为手腕需保持稳固。握力强化属于后期阶段,在融合骨愈合且您获得明确许可之前,不应开始进行。如果手腕背部出现剧烈疼痛,请立即停止任何练习。
您的临床方案
本页其余部分为全腕关节融合术后康复的分阶段临床方案。本节内容应提供给您的手部治疗师,每个阶段均以通俗易懂的语言解释当前正在发生的情况。本方案没有腕关节活动度(ROM)目标:桡腕关节(通常还包括第三掌指关节)已通过背侧钢板进行融合。该方案旨在融合骨愈合期间保护手指活动度、前臂旋转功能并控制水肿,随后在稳定的内固定结构基础上增强握力。
在治疗开始前,请查阅患者的手术报告及既往病史,并与主刀医生沟通内固定结构(背侧融合钢板;第三掌指关节是否包含在融合范围内或予以保留)、融合后的腕关节位置、是否使用骨移植以及骨愈合状态。Hirpara 医生采用背侧钢板将腕关节固定于轻度背伸位;由于内固定稳定,故使用轻便夹板或敷料以提供舒适感,而非长时间使用刚性石膏固定,且早期手指及前臂活动为首要任务。
第一阶段 — 保护内固定结构,活动未融合关节(第 0 至 6 周)
前六周旨在保护愈合中的融合部位,同时确保所有未融合的部分保持完全活动。佩戴轻便夹板或敷料以提供舒适感。由于内固定结构在设计上是刚性的,因此禁止腕部活动,重点完全集中在手指、拇指、前臂及肿胀管理上。
致您的手部治疗师:
健康教育与注意事项 - 佩戴夹板/敷料以提供舒适与保护,直至临床及影像学显示骨性愈合;鉴于钢板固定稳定,无需长期刚性石膏固定 - 禁止腕部活动:桡腕关节/掌指关节结构已融合;无关节活动度(ROM)目标 - 在确认骨性愈合前,禁止负重抓握或提起超过轻杯重量的物体 - 警惕手指僵硬:这是腕关节融合术后影响预后的主要威胁
管理措施 - 伤口:按医嘱进行外科敷料护理;约在 10–14 天时拆线并进行夹板/X 光复查;监测感染迹象 - 水肿:抬高患肢至心脏水平以上,进行轻柔的手指泵式运动,必要时冰敷 - 练习:从第一天起进行完全主动的手指和拇指主动关节活动度(AROM)(复合握拳 → 完全伸展,拇指对掌);主动前臂旋前/旋后;主动肩部和肘部关节活动度;禁止腕部活动,禁止抗阻抓握
进展标准 - 伤口愈合;维持完全或接近完全的手指关节活动度;约六周时出现早期影像学骨性愈合征象
第二阶段——确认骨性愈合,开始抓握负荷(第6至12周)
大约六周时,X光片通常显示融合处正在愈合,一旦外科医生确认这一点,即可弃用支具并开始抓握强化训练。前臂和手指训练继续进行;腕关节保持融合且仅在不承重状态下维持,直至确认骨性愈合。
致您的手部治疗师:
评估 - 在施加负荷前,与主治外科医生确认愈合状态;手指活动度(ROM);前臂旋转范围;抓握基线;伤口/瘢痕检查
宣教与注意事项 - 仅在外科医生确认骨性愈合后(通常为六至八周)开始抓握和轻度负荷 - 背侧腕部内固定物位于皮下;注意观察突出/刺激症状并及时报告 - 在整个过程中继续优先保证手指全范围活动度
管理 - 练习:确认骨性愈合后,进行渐进式抓握强化(软球 → 治疗泥 → 分级握力器);伤口愈合后开始瘢痕管理;继续前臂旋转和手指全范围活动度训练;引入轻度功能性手部使用 - 宣教:前臂旋转现在替代了丧失的腕部运动,用于日常任务(开门、敲击、转动)
晋级标准 - 确认骨性愈合;无痛轻度抓握;手指全范围活动度;瘢痕活动
第三阶段——强化训练与负重恢复(第12周及以后)
一旦骨融合牢固,便无需限制活动以进行保护;手部可按耐受程度逐步负重并强化。抓握力及整体手部力量在术后数月内持续改善,通常优于术前水平,因为抓握现已无痛。
致手部治疗师:
评估 - 抓握力与对侧对比;功能性及工作/任务特异性测试;内固定物耐受性
宣教与注意事项 - 骨性愈合后无活动限制;按耐受程度逐步增加负重 - 重体力/手动负荷需逐步建立;完全的力量增益可持续至约12个月
管理 - 练习:渐进性抗阻抓握及前臂强化;分级恢复功能性及工作任务;继续残余的手指活动度训练 - 一旦抓握功能恢复且持续改善,并能应对日常任务,可考虑出院;若出现手指僵硬、持续性内固定物刺激或不良预后,请转回主诊医生
恢复负重标准 - 牢固愈合;抓握功能恢复且持续改善;任务特异性负重无痛
重返工作与活动
从术后初期开始,即在舒适范围内,鼓励进行轻度日常手部活动(如进食、书写、轻度自我护理),前提是融合骨愈合前不要用力抓握或提起超过一杯轻饮的重量。由于佩戴支具期间或无法安全操控车辆时禁止驾驶,请提前安排早期数周的出行协助;待拆除支具且能在复查时确认能操控方向盘后,方可恢复驾驶。
负重抓握、提举和拉拽需等待融合骨愈合(通常为六至八周左右)并获得许可后方可进行,随后逐步增加强度。大多数人约三个月即可重返办公室或从事轻体力工作,较重或体力劳动则需更长时间,其进度由Hirpara医生及您的手部治疗师基于标准评估决定,而非仅依据时间。力量可持续改善长达一年,且由于磨损的腕关节不再疼痛,许多人的抓握力比术前更强,手部使用也更自如。
您的方案之后
本方案与本诊所的一般康复建议配合使用:请参阅 术后疼痛管理、伤口护理 和 疤痕管理。上述分阶段计划反映了全腕关节融合术后已发表的疗效及康复指南,您的持续康复将由 Hirpara 医生和您的手部治疗师根据您的融合及手部进展情况提供个体化指导。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: post-operative rehabilitation after total wrist arthrodesis — permanent surgical fusion of the radiocarpal (and usually the third carpometacarpal) joints with a dorsal arthrodesis plate, for end-stage pancarpal (panarticular) arthritis of the wrist. This is a salvage reconstruction that deliberately abolishes wrist motion, not a motion-preserving operation, so the rehabilitation has no wrist-ROM goal. It is built around preserving the joints the fusion leaves free — the fingers, thumb and forearm rotation — and controlling oedema while the fusion unites, then progressive grip loading once united.
Defining principle of the rehab here: total wrist fusion trades motion for a stable, pain-free wrist. The whole wrist is set solid (radius → metacarpals) in slight extension; loss of wrist movement is the intended endpoint, not a deficit to be rehabilitated. Modern dorsal locking-plate fixation is rigid enough that prolonged casting is unnecessary — so the deliberate priorities are early digital and forearm-rotation motion (digital stiffness is the principal threat to a good result) and swelling control, with grip strengthening deferred until radiographic union (typically 6–8 weeks). The single branch point is union status: loading is gated on the surgeon confirming the fusion has consolidated, after which there are no motion restrictions to protect.
A. PROCEDURE OUTCOMES (total wrist arthrodesis, dorsal plate)
Total wrist arthrodesis is a reliable, durable salvage for the painful, arthritic wrist that has failed non-operative care: the great majority of patients obtain lasting pain relief and a stable hand, accepting the loss of wrist motion in exchange.
- High union rates and durable pain relief. Plate arthrodesis is a well-established, reproducible operation; published series and the JAAOS review of indications and outcomes report reliable fusion, good pain relief and high patient satisfaction, with most patients willing to undergo it again [Wei & Feldon, JAAOS 2017; Shah et al., J Hand Surg Am 2022 — technique/modifications]. Moderate–strong (review + technique series).
- Grip strength is preserved or improves. Because gripping is no longer painful and the wrist is a stable platform, grip strength after fusion is typically equal to or better than the painful pre-operative wrist. A 2026 systematic review and meta-analysis of long-term grip strength after total wrist fusion (comparing inclusion vs sparing of the third CMC joint) confirms maintained long-term grip with comparable complication profiles between the two constructs [Lawson-Smith et al., J Hand Surg Glob Online 2026]. Moderate (SR/meta-analysis).
- Function is good for daily tasks; forearm rotation compensates for lost wrist motion. Patients adapt well because forearm pronation/supination (unaffected by the fusion) substitutes for much of the lost wrist arc in activities such as turning keys, taps and handles. Carpometacarpal-joint– sparing plate designs aim to retain a small amount of motion and reduce distal hardware issues [Briotti et al., HAND 2022 — Medartis CMC-sparing plate]. Moderate (cohort).
- Complications are defined and manageable. Principal complications are nonunion, hardware prominence/irritation requiring plate removal (the dorsal plate is subcutaneous), wound issues, and adjacent-segment problems (distal radioulnar joint / digital stiffness). These are recognised, generally treatable, and informed-consent staples rather than common catastrophes [Wei & Feldon, JAAOS 2017; Kalb & Prommersberger, Oper Orthop Traumatol 2009 — AO plate technique]. Moderate.
B. REHABILITATION / THERAPY EVIDENCE
The rehab questions after total wrist fusion are different from a motion-preserving operation: there is no wrist arc to recover. The evidence and consensus instead converge on early mobilisation of the unfused joints, oedema control, and union-gated grip loading, exploiting the stability of modern plate fixation.
- Stable plate fixation permits early digital and forearm motion. Rigid dorsal locking-plate constructs are robust enough that prolonged rigid immobilisation is unnecessary; a light splint or dressing for comfort, with immediate finger, thumb and forearm-rotation motion, is the intended default [Shah et al., J Hand Surg Am 2022; Kalb & Prommersberger, Oper Orthop Traumatol 2009]. Moderate (technique consensus).
- Preserving digital range is the priority — stiffness is the main avoidable failure. Because the hand's function after fusion depends entirely on the joints left mobile, full active finger and thumb range from day one, plus preserved forearm rotation, is the core therapeutic aim. This is a mechanistic/consensus position rather than one from comparative rehab trials. Weak–moderate (mechanism strong, dedicated rehab RCTs absent).
- Grip strengthening is deferred to union, then progressed freely. Loaded grip is withheld until the surgeon confirms radiographic union (commonly 6–8 weeks), after which there are no motion restrictions and strengthening is progressed as tolerated; grip continues to improve for several months. Consensus / protocol-based.
- Hand therapy targets the free joints, not the wrist. Published patient-guidance protocols and surgical references describe early referral to a hand therapist for finger and forearm mobility and later putty-based grip strengthening — there is no wrist-ROM component by design [AAOS OrthoInfo — Wrist Fusion; institutional post-op protocols]. Consensus (patient-guidance).
Recovery trajectory (expected, evidence-anchored)
| Phase | Window | Restraint | Hand use / therapy focus | Strength / load | Notes |
|---|---|---|---|---|---|
| I — Protect construct, mobilise free joints | Week 0–6 | Light splint/dressing for comfort; no wrist motion (fused) | Elevate; immediate full finger + thumb AROM; forearm pronation/supination; elbow/shoulder ROM; oedema control | Light functional use only; no loaded grip / lifting > a light cup | Sutures + splint/X-ray review ~10–14 days. Digital stiffness is the chief threat |
| II — Confirm union, begin grip loading | Week 6–12 | Loading gated on surgeon-confirmed union (≈6–8 wk) | Splint discarded at union; progressive grip (ball → putty → grippers); scar massage once healed; continue forearm + digital ROM | Grip introduced light → graded after union | Forearm rotation substitutes for lost wrist motion. Watch dorsal hardware prominence |
| III — Strengthening & return to load | Week 12 → 12 months | None once united | Progressive resisted grip/forearm strengthening; work-/task-specific loading | Full load as tolerated; heavy/manual built up gradually | Office/light work ~3 months; strength improves up to ~12 months, often exceeding pre-op (pain-free grip) |
(Phase windows mirror the precautions and recovery structure in the patient protocol; they are typical guides anchored to union, not trial-derived deadlines.)
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Fusion vs total wrist arthroplasty. The central modern controversy. Systematic review of total wrist arthroplasty versus arthrodesis (originally in rheumatoid disease) found insufficient evidence to declare either superior, with arthroplasty preserving some motion at the cost of higher revision/implant-related complications, and fusion offering durability at the cost of motion [Cavaliere & Chung, Plast Reconstr Surg 2008]. A cost-utility analysis found arthrodesis and arthroplasty both reasonable, with trade-offs in motion, complications and cost [Cavaliere & Chung, J Hand Surg Am 2010]. The "where are we now" synthesis frames the choice as patient-specific (demand, bilateral disease, expectations) rather than a settled winner [Jump, Trail & Talwalkar, J Hand Surg Eur 2025]. Moderate; genuine equipoise.
- Arthrodesis as salvage for failed arthroplasty. Total wrist fusion reliably salvages a failed total wrist arthroplasty, though such salvage fusions behave somewhat differently (bone loss, grafting) from primary arthrodesis [Zijlker et al., J Hand Surg Eur 2021]. Moderate.
- Include or spare the third CMC joint. Constructs differ in whether the plate crosses the third carpometacarpal joint. Long-term grip and complication outcomes are broadly comparable between inclusion and sparing, with CMC-sparing designs aiming to reduce distal hardware issues and retain a trace of motion [Lawson-Smith et al., J Hand Surg Glob Online 2026; Briotti et al., HAND 2022]. Moderate.
- Hardware prominence and removal. The subcutaneous dorsal plate is a recognised source of irritation and a common reason for elective hardware removal once the fusion is solid — expected, not a failure of the operation [Wei & Feldon, JAAOS 2017]. Moderate.
- Special populations. In spastic/neurological wrists (e.g. cerebral palsy), fusion changes hand function in nuanced ways — improving positioning but with task-specific trade-offs — underlining that the goal is a useful stable position, not motion [Hargreaves, Warwick & Tonkin, J Hand Surg Br 2000]. Moderate (specialised cohort).
D. EVIDENCE STRENGTH FLAGS (summary)
- STRONG (SR / meta-analysis): preserved-to-improved long-term grip strength after total wrist fusion; comparable outcomes between CMC-inclusion and CMC-sparing constructs [Lawson-Smith et al. 2026].
- MODERATE: reliable union, durable pain relief and high satisfaction with plate arthrodesis [Wei & Feldon 2017; Shah et al. 2022]; genuine equipoise between fusion and arthroplasty with motion-vs-durability/complication trade-offs [Cavaliere & Chung 2008, 2010; Jump et al. 2025]; fusion as salvage for failed arthroplasty [Zijlker et al. 2021]; defined complication set (nonunion, hardware removal, DRUJ/digital adjacent issues).
- WEAK / CONSENSUS: the specific early digital/forearm-motion, union-gated grip rehabilitation programme (mechanistically rationalised — stiffness avoidance — with no dedicated rehab RCTs); exact phase timings (typical, anchored to union rather than trial-derived); stable-fixation early-motion default from technique consensus [Shah et al. 2022; Kalb & Prommersberger 2009].
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Total Wrist Arthrodesis: Indications and Clinical Outcomes. J Am Acad Orthop Surg. 2017. DOI: 10.5435/jaaos-d-15-00424
- Radiocarpal Fusion: Indications, Technique, and Modifications. J Hand Surg Am. 2022. DOI: 10.1016/j.jhsa.2022.04.002
- Long-term Grip Strength and Complications After Total Wrist Fusion With and Without Inclusion of the Third Carpometacarpal Joint: A Systematic Review and Meta-analysis. J Hand Surg Glob Online. 2026. DOI: 10.1016/j.jhsg.2026.101022
- Wrist Arthrodesis Using the Medartis Carpometacarpal Joint Sparing Plate. HAND. 2022. DOI: 10.1177/15589447221141474
- A Systematic Review of Total Wrist Arthroplasty Compared with Total Wrist Arthrodesis for Rheumatoid Arthritis. Plast Reconstr Surg. 2008. DOI: 10.1097/prs.0b013e318180ece3
- A Cost-Utility Analysis of Nonsurgical Management, Total Wrist Arthroplasty, and Total Wrist Arthrodesis in Rheumatoid Arthritis. J Hand Surg Am. 2010. DOI: 10.1016/j.jhsa.2009.12.013
- Arthrodesis or arthroplasty, complete or partial: where are we at in the 21st century? J Hand Surg Eur Vol. 2025. DOI: 10.1177/17531934241296758
- Comparative outcomes of total wrist arthrodesis for salvage of failed total wrist arthroplasty and primary wrist arthrodesis. J Hand Surg Eur Vol. 2021. DOI: 10.1177/17531934211057389
- Die vollständige Versteifung des Handgelenks mit der AO-Handgelenk-Arthrodesenplatte (Complete wrist arthrodesis with the AO wrist arthrodesis plate). Oper Orthop Traumatol. 2009. DOI: 10.1007/s00064-009-1905-2
- Changes in Hand Function Following Wrist Arthrodesis in Cerebral Palsy. J Hand Surg Br. 2000. DOI: 10.1054/jhsb.2000.0366
Wrist-fusion rehabilitation / patient-guidance literature (URLs)
- American Academy of Orthopaedic Surgeons — Wrist Fusion (Wrist Arthrodesis), OrthoInfo (recovery timeline; fusion heals ~8–12 weeks; the fused wrist no longer moves; therapy for joints not fused). https://orthoinfo.aaos.org/en/treatment/wrist-fusion-wrist-arthrodesis/
- Wrist Arthrodesis Technique — postoperative care and approach considerations. Medscape eMedicine. https://emedicine.medscape.com/article/1241236-technique
- Total Wrist Arthrodesis (Wrist Fusion) — procedure and rehabilitation overview. Resurgens Orthopaedics. https://www.resurgens.com/hand-wrist/procedures/wrist-fusion-total-wrist-arthrodesis
- Full Wrist Fusion — Post-Operative Rehabilitation Protocol (institutional hand-therapy protocol; early digital/forearm motion, union-gated grip strengthening). Alaska Orthopedic. https://www.akortho.com/wp-content/uploads/Full-Wrist-Fusion.pdf





