

Exercícios para pacientes internados — manguito rotador e estabilização Folheto
Estes são os exercícios suaves a serem iniciados no hospital após uma reparação do manguito rotador ou uma estabilização do ombro. Eles mantêm a mão, o cotovelo e o ombro em movimento enquanto a reparação cicatriza.
Seus exercícios

Kieran Hirpara 4.0
Movimento do punho
Mantenha a mão em movimento, dobrando o punho para a frente, para trás e para os lados.
10 vezes, 3 vezes por dia.

Kieran Hirpara 4.0
Abrir e fechar a mão
Mantenha a mão e os dedos em movimento, abrindo e fechando-os ou apertando uma bola antiestresse.
10 vezes, 3 vezes por dia.

Kieran Hirpara 4.0
Flexão do cotovelo
Flexione e estenda o cotovelo.
10 vezes, 3 vezes por dia.

Kieran Hirpara 4.0
Pêndulos
Este é um exercício passivo. Incline-se para a frente e deixe o braço relaxar. Use o corpo para mover o braço suavemente, tanto no sentido horário quanto anti-horário, além de para a frente, para trás e para os lados.
Cerca de 30 segundos em cada direção, 3 vezes por dia.

Kieran Hirpara 4.0
Flexão anterior assistida
Sentado numa cadeira e inclinado para a frente, segure o braço operado com o outro braço e mova-o suavemente para cima, à sua frente. Em seguida, abaixe-o novamente com a ajuda do braço não operado. Se preferir, pode deitar-se de costas na cama e levantar o braço dessa maneira.
10 vezes, 3 vezes por dia.
Kieran Hirpara 4.0
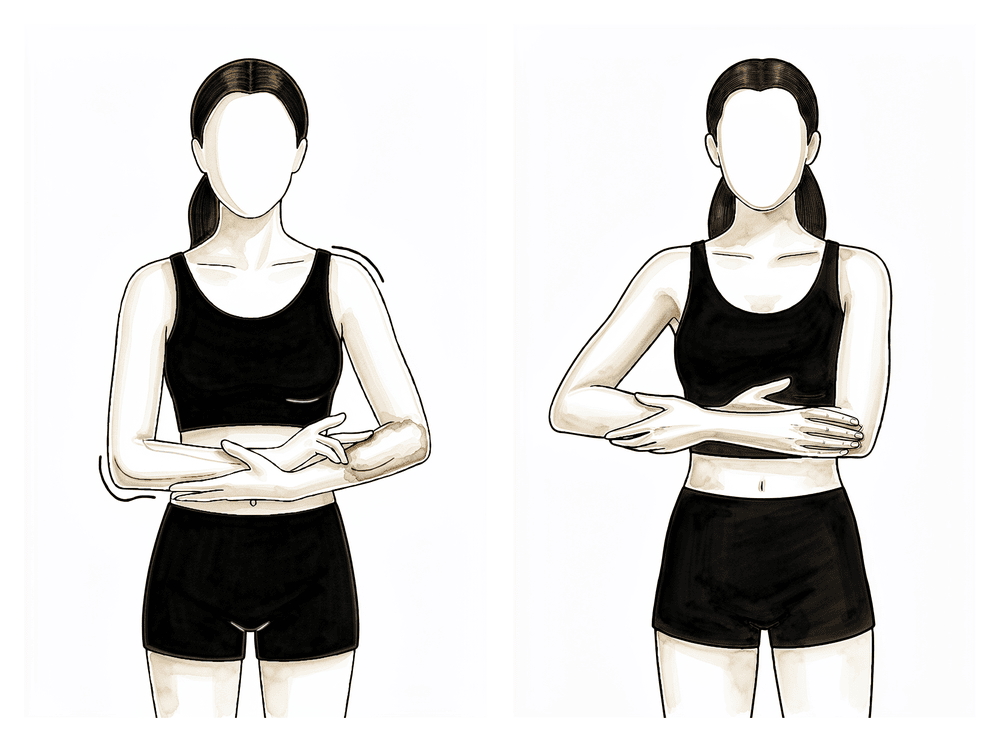
Abdução assistida
Sentado numa cadeira e inclinando-se para a frente, embale novamente o braço e ajude-o a mover para o lado (como se estivesse embalando um bebê).
10 vezes, 3 vezes por dia.
Kieran Hirpara 4.0
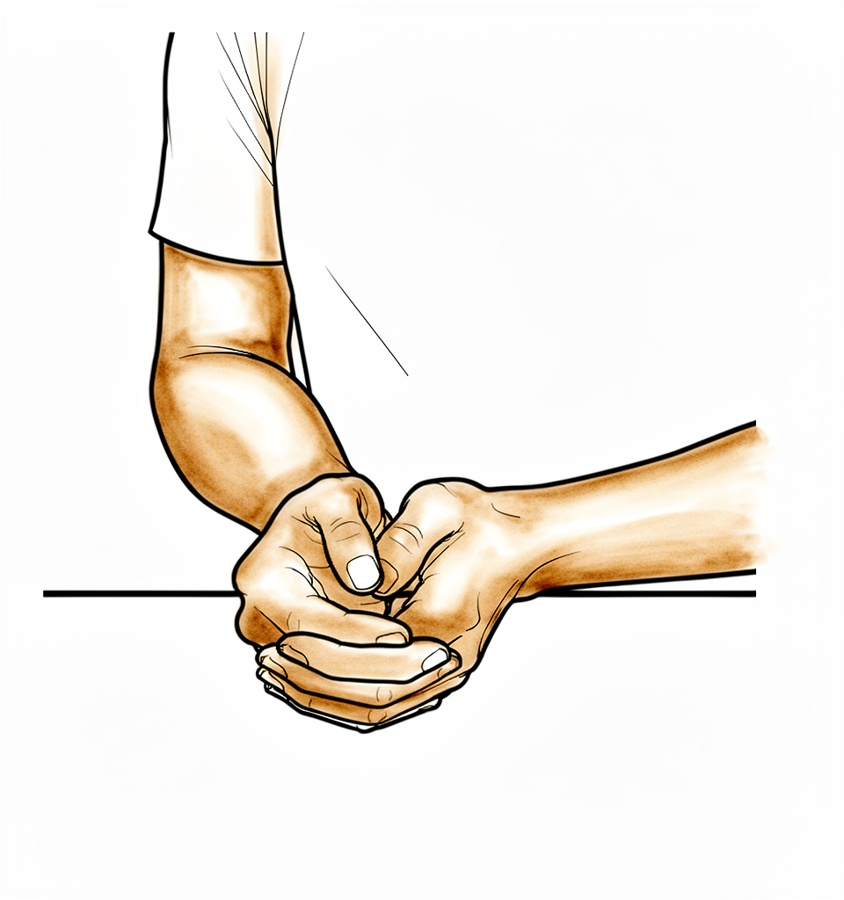
Rotação externa
Sentado numa cadeira, mova apenas o braço a partir da posição em que ele se encontra na tipóia, até ficar apontado diretamente à sua frente. Não o mova para além disso.
10 vezes, 3 vezes por dia.

Kieran Hirpara 4.0
Ativação do trapézio inferior
Aperte as escápulas para baixo e para junto uma da outra.
Mantenha por 5 segundos, 5 vezes, 3 vezes ao dia.
Kieran Hirpara 4.0
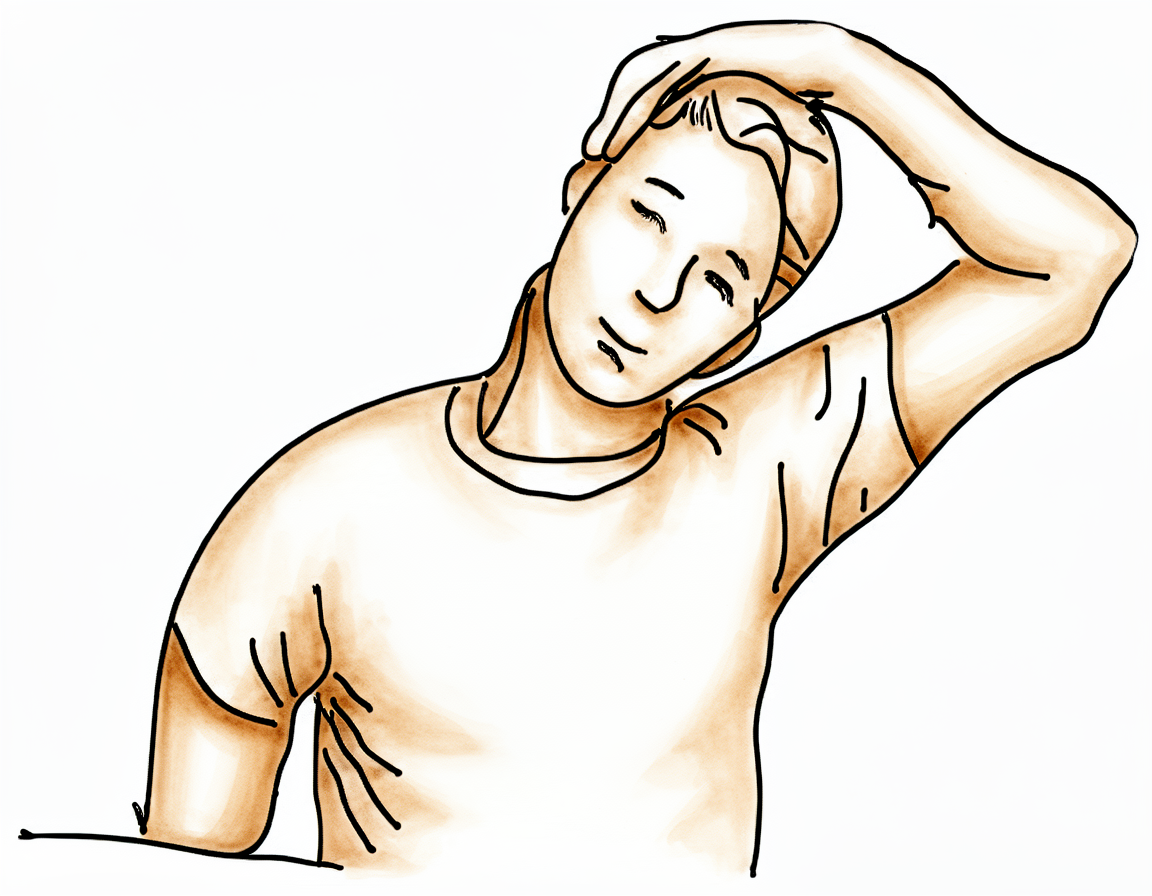
Alongamento do trapézio superior
Use o braço não operado para aproximar a orelha do ombro, afastando-a do lado operado.
Mantenha por 10 segundos, 3 vezes, 3 vezes ao dia.
Kieran Hirpara 4.0
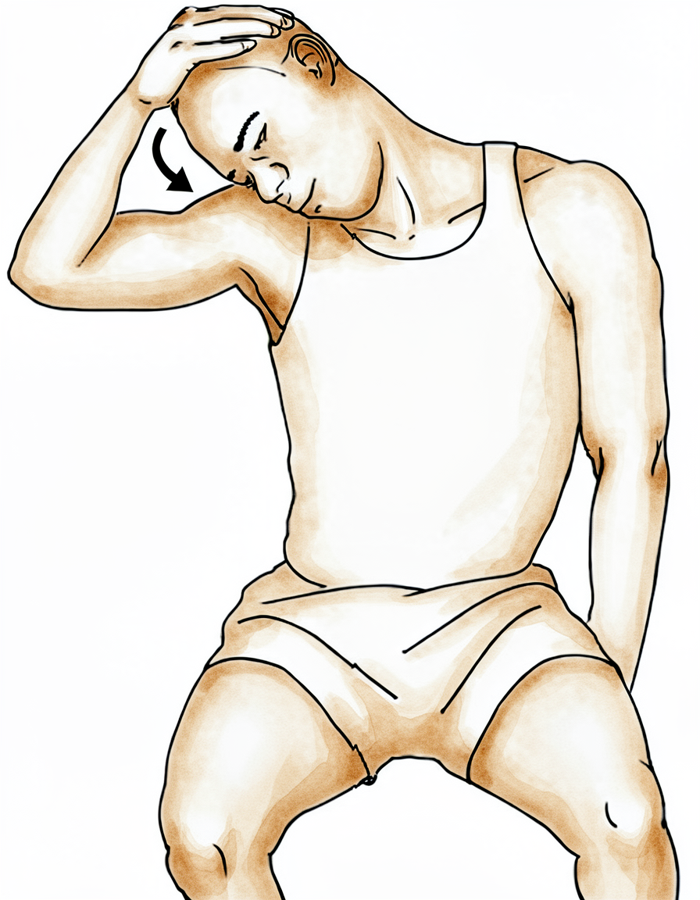
Alongamento do levantador da escápula
Use o braço não operado para aproximar o nariz da região da axila, afastando-o do lado operado.
Mantenha por 10 segundos, 3 vezes, 3 vezes ao dia.
Comece estes exercícios suaves no hospital e continue fazendo-os em casa. Eles devem ser confortáveis; reduza a intensidade caso a dor aumente.
Como usar a tipóia
- Você pode tirar o braço da tipóia para fazer os exercícios e para tomar banho.
- É necessário usar a tipóia por 6 semanas, especialmente quando estiver fora de casa.
- Não é preciso dormir com a tipóia.
- Se necessário, use gelo para aliviar a dor.
- Ao usar a tipóia, relaxe o ombro e deixe que a tipóia suporte o peso do braço.
- Tome os analgésicos antes de fazer os exercícios e antes das sessões de fisioterapia.
- A menos que tenha agendado sua própria fisioterapia, já foi marcada uma consulta para você; os detalhes constam no seu pacote de alta.
- Caso tenha algum problema, entre em contato com o consultório ou informe seu fisioterapeuta.
Ao chegar em casa
Depois de chegar em casa, sua recuperação prossegue com todo o protocolo de reabilitação correspondente à sua cirurgia: reparo do manguito rotador; estabilização anterior e procedimento de Latarjet; estabilização posterior.
Após seguir o seu protocolo
Esses exercícios iniciais constituem o ponto de partida no hospital, tanto para a reparação do manguito rotador quanto para a estabilização do ombro: eles mantêm o movimento suave da mão, do cotovelo e do ombro, enquanto a área operada permanece protegida. As frequências e durações dos exercícios são consideradas típicas, mas não fixas; a sua reabilitação posterior será orientada individualmente pelo seu fisioterapeuta, em colaboração com a clínica, conforme a evolução da recuperação do seu ombro. Esta página complementa as orientações gerais de recuperação fornecidas pela clínica; consulte controle da dor pós-operatória e cuidados com a ferida. O plano completo, específico para a sua cirurgia, consta no seu próprio protocolo (linkado acima). As evidências científicas que sustentam esta fase inicial – incluindo pesquisas sobre o movimento precoce versus tardio após a reparação do manguito rotador e os benefícios da imobilização após a estabilização do ombro – estão resumidas na seção de evidências, disponível como PDF no topo desta página.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: This is the early in-hospital / early-protected phase of a combined pathway covering patients who had a rotator cuff repair and/or a shoulder stabilisation procedure (anterior labral/Bankart repair, Latarjet, or posterior labral/capsular repair). It deliberately stops at the point of discharge plus the first protected weeks — the gentle hand/elbow/shoulder exercises that keep the limb moving while the repair is protected by the sling. The full, operation-specific rehabilitation course lives in the parent protocols, which this page hands the patient back to once they go home:
Defining principle of this early phase — PROTECT the repair: Unlike a frozen-shoulder release (where immediate aggressive motion is the goal), a cuff repair and a labral/capsular stabilisation both create a construct that must heal undisturbed. So the early phase is the same for both: sling immobilisation, gentle/passive-only motion within safe limits, and NO active or resisted shoulder work. Tendon-to-bone and labrum-to-bone healing is weak in the first weeks, so the sling and the movement limits are the protectors. The hand, wrist and elbow are kept moving freely throughout (these don't stress the repair) to prevent swelling and stiffness; the shoulder itself is only moved passively/with assistance within the limits the surgeon and physiotherapist set.
The early in-hospital phase (what this page covers)
In the first hours-to-days after surgery the aims are simple and shared across both operation families:
- Protect the repair — arm in the sling, no active lifting or reaching, no loading.
- Keep the rest of the limb moving — wrist, fingers and elbow exercises to prevent swelling and stiffness (these put no stress on the cuff or labral repair).
- Gentle, assisted shoulder motion only — pendulums and assisted/passive elevation within a safe arc; for an anterior repair, external rotation is limited; for a posterior repair, internal rotation and reaching behind the back are limited (the at-risk directions are opposite).
- Pain control and a safe discharge plan — analgesia before exercise, sling instructions, and a physiotherapy follow-up arranged in the discharge pack.
The standalone protocols then drive the rest of recovery (the full sling-weaning schedule, when active motion and strengthening begin, and return to work/sport). The same first-phase principles appear at the head of each of those protocols — this inpatient page simply consolidates that shared early phase for patients who had the procedure(s) performed together or are still in hospital.
Evidence by theme
Theme 1 — Early vs delayed motion after rotator cuff repair (the central debate)
This is the best-studied question that shapes the early phase, and the corpus is rich on it. Two competing concerns: early passive motion reduces post-operative stiffness, while delayed/immobilisation may better protect tendon-to-bone healing (lower retear), especially in larger tears.
- Multiple RCTs and systematic reviews of overlapping meta-analyses converge on the same bottom line: early and delayed passive motion give superior early range of motion for the early group but equivalent final outcomes by ~6–12 months for small-to-medium tears — so timing is largely surgeon preference and does not change the end result [Saltzman 2017; Mazzocca 2017].
- For large/massive tears the balance tilts toward a delayed / protected approach to favour healing [systematic-review/meta-analysis evidence; BMC Musculoskelet Disord 2025].
- A "knowing the speed limit" theme runs through the reviews: tendon repairs are mechanically weak early, and very aggressive early therapy can compromise the construct [Thigpen 2015 review].
Practical consequence for this page: the early in-hospital phase is passive/assisted-only with the sling on regardless of which approach the surgeon ultimately chooses for the home phase — the disagreement in the literature is about how soon to progress, not about whether to protect the repair in the first days. A defining surgical decision (early vs delayed progression, and how it is size-stratified) is made by the surgeon and detailed in the cuff-repair protocol.
Theme 2 — Immobilisation after stabilisation (anterior and posterior)
The stabilisation literature also supports an early protected phase, though high-level evidence is sparser and protocols are more consensus-driven.
- Anterior (Bankart/capsulolabral) repair: the American Society of Shoulder and Elbow Therapists' consensus guideline recommends 0–4 weeks of absolute immobilisation, then relative immobilisation (out of the sling only for exercises) to ~6 weeks, with no forced external rotation/extension for ~3 months; early ER is progressed gradually (e.g. ~15° at 0–2 wk → ~35° at 2–4 wk → ~55° at 4–6 wk). A simple sling is used in the large majority of published protocols.
- Posterior (labral/capsular) repair: the precaution is reversed — the sling is positioned in slight abduction and neutral/slight external rotation, the arm is kept in front of the body, and internal rotation, adduction and reaching behind the back are avoided early. Posterior instability is uncommon (~3–5%), so the protocols are biomechanically reasoned (Level IV–V) rather than RCT-tested.
- Both share the same headline as the cuff-repair early phase: sling on, gentle motion within the safe arc, no active/resisted shoulder work while the labrum/capsule heals.
Early-phase timeline (consolidated; first weeks only)
This focuses on the shared early-protected window and is consistent with the synthesis page. The full operation-specific schedules continue in the parent protocols.
| Phase | Window | Sling | Shoulder motion | Active / strengthening | Notes |
|---|---|---|---|---|---|
| Inpatient / immediate | Day 0 — discharge | On at all times (off only for exercises & showering) | Wrist/hand/elbow moving freely; pendulums; gentle assisted/passive elevation within safe limits | None for the shoulder (no active lift, no resisted work) | Analgesia before exercises; ice for comfort; physiotherapy follow-up arranged |
| Early protected | Week 0–6 | Worn ~6 weeks, especially out of the house; not needed for sleep | Continue gentle assisted/passive motion within limits — anterior repair: limit external rotation; posterior repair: limit internal rotation / no reaching behind the back | Still no active/resisted shoulder work | The sling and the direction limits are the protectors; ease back if pain rises |
| Handover to parent protocol | ~Week 6 onward | Weaned per the operation-specific protocol | Active-assisted → active motion begins in the parent protocol, not here | Strengthening begins later (cuff repair typically ~12 wk; stabilisation per its own schedule) | Recovery continues with the rotator cuff repair, anterior stabilisation & Latarjet, or posterior stabilisation protocol |
The sling duration, the exact motion limits, and when active motion and strengthening begin are surgeon-set clinical decisions; the windows above are the typical shared early phase, not trial-derived precise cut-offs.
Key controversies / evidence quality
- Early vs delayed progression after cuff repair is the one well-studied question, and it is about the home phase rather than the in-hospital phase. RCTs/meta-analyses show equivalent final outcomes for small/medium tears and a protect-healing tilt for large/massive tears — the early in-hospital protected phase is common ground either way. Strong (RCT / SR-MA), but Cochrane-level certainty for any single optimal schedule remains low.
- Stabilisation immobilisation duration and sling position are largely consensus/biomechanical — there is no RCT defining the optimal early regimen, and posterior protocols in particular are extrapolated. Weak–moderate / consensus.
- The combined early-phase protocol itself is a surgeon patient-guidance consolidation, not a trial-derived schedule. It is deliberately brief and defers to the parent protocols for the full course.
Evidence-strength flags (summary)
- STRONG (RCT / SR-MA): early-vs-delayed passive motion after cuff repair → equivalent final outcomes for small/medium tears, protect-healing tilt for large/massive (Saltzman 2017; Mazzocca 2017; BMC Musculoskelet Disord 2025 SR-MA).
- MODERATE / CONSENSUS: anterior stabilisation immobilisation schedule (ASSET/JOSPT consensus guideline); graded early ER limits.
- WEAK / CONSENSUS (Level IV–V): posterior stabilisation sling position and precautions (biomechanical, no RCT); the consolidated early in-hospital protocol itself.
Citations
RAG corpus (180,000+ Orthopaedic articles)
- Saltzman BM, Zuke WA, Go B, et al. Early Versus Delayed Motion After Rotator Cuff Repair: A Systematic Review of Overlapping Meta-analyses. Am J Sports Med. 2017. DOI: 10.1177/0363546517692543
- Mazzocca AD, Arciero RA, Shea KP, et al. The Effect of Early Range of Motion on Quality of Life, Clinical Outcome, and Repair Integrity After Arthroscopic Rotator Cuff Repair. Arthroscopy. 2017. DOI: 10.1016/j.arthro.2016.10.017
- Effects of early exercise and immobilization after arthroscopic rotator cuff repair surgery: a systematic review and meta-analysis of randomized controlled trials. BMC Musculoskelet Disord. 2025. DOI: 10.1186/s12891-025-08500-7
- Which is better? Early versus delayed rehabilitation after arthroscopic rotator cuff repair. Knee Surg Sports Traumatol Arthrosc. 2024. DOI: 10.1002/ksa.12129
- Thigpen CA, Shaffer MA, Kissenberth MJ. Knowing the Speed Limit (post-cuff-repair rehab progression). Clin Sports Med. 2015. DOI: 10.1016/j.csm.2014.12.007
- Rehabilitation Following Arthroscopic Rotator Cuff Repair. J Bone Joint Surg. DOI: 10.2106/jbjs.m.00034
- Anterior Shoulder Instability Part I — Diagnosis, Nonoperative Management, and Bankart Repair — An International Consensus Statement. Arthroscopy. 2021. DOI: 10.1016/j.arthro.2021.07.022
Literature / consensus guidelines (URLs)
- The American Society of Shoulder and Elbow Therapists' Consensus Rehabilitation Guideline for Arthroscopic Anterior Capsulolabral Repair of the Shoulder. JOSPT. 2010. https://www.jospt.org/doi/10.2519/jospt.2010.3186
- Rehabilitation Protocol Variability Following Arthroscopic Bankart Repair and Remplissage: A Systematic Review. Int J Sports Phys Ther. https://pmc.ncbi.nlm.nih.gov/articles/PMC11446737/
- Current Concepts in Rehabilitation for Traumatic Anterior Shoulder Instability. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC5685970/
- Rehabilitation Following Posterior Shoulder Stabilization (clinical commentary). PMC8168996. https://pmc.ncbi.nlm.nih.gov/articles/PMC8168996/
Published patient/rehab protocols (basis for the early-phase structure)
- Massachusetts General Hospital — Rehabilitation Protocol for Bankart Repair. https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-bankart-repair.pdf
- University of Virginia Sports Medicine — Posterior Labral Repair Rehabilitation Protocol. https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2021/06/Posterior-Labral-Repair.pdf
- Brigham & Women's Hospital — Arthroscopic Rotator Cuff Repair Protocol (early protected phase, tear-size stratification). https://www.brighamandwomens.org/assets/BWH/patients-and-families/rehabilitation-services/pdfs/shoulder-arthroscopic-rct-repair-protocol-hybrid-patient-therapist.pdf





