

Các bài tập dành cho bệnh nhân nằm viện — chóp xoay và phẫu thuật ổn định khớp vai Thông tin
Đây là những bài tập nhẹ nhàng có thể bắt đầu thực hiện tại bệnh viện sau khi phẫu thuật khâu lại gân cơ chóp xoay hoặc cố định khớp vai. Các bài tập này giúp duy trì sự vận động của tay, khuỷu tay và vai trong quá trình vết thương lành lại.
Các bài tập của bạn

Kieran Hirpara 4.0
Chuyển động cổ tay
Hãy liên tục cử động tay bằng cách gập cổ tay về phía trước, phía sau và sang hai bên.
10 lần, 3 lần mỗi ngày

Kieran Hirpara 4.0
Mở và nắm tay
Hãy cử động tay và các ngón tay bằng cách mở ra, khép lại, hoặc nắm chặt quả bóng giảm căng thẳng.
10 lần, 3 lần mỗi ngày

Kieran Hirpara 4.0
Cử động gập khuỷu tay
Hãy gập và duỗi khuỷu tay của bạn.
10 lần, 3 lần mỗi ngày

Kieran Hirpara 4.0
Con lắc
Đây là bài tập thụ động. Hãy cúi người về phía trước và để cánh tay thả lỏng. Dùng cơ thể để nhẹ nhàng di chuyển cánh tay theo chiều kim đồng hồ hoặc ngược chiều kim đồng hồ, đồng thời di chuyển về phía trước, phía sau và sang hai bên.
Khoảng 30 giây cho mỗi hướng, 3 lần mỗi ngày.

Kieran Hirpara 4.0
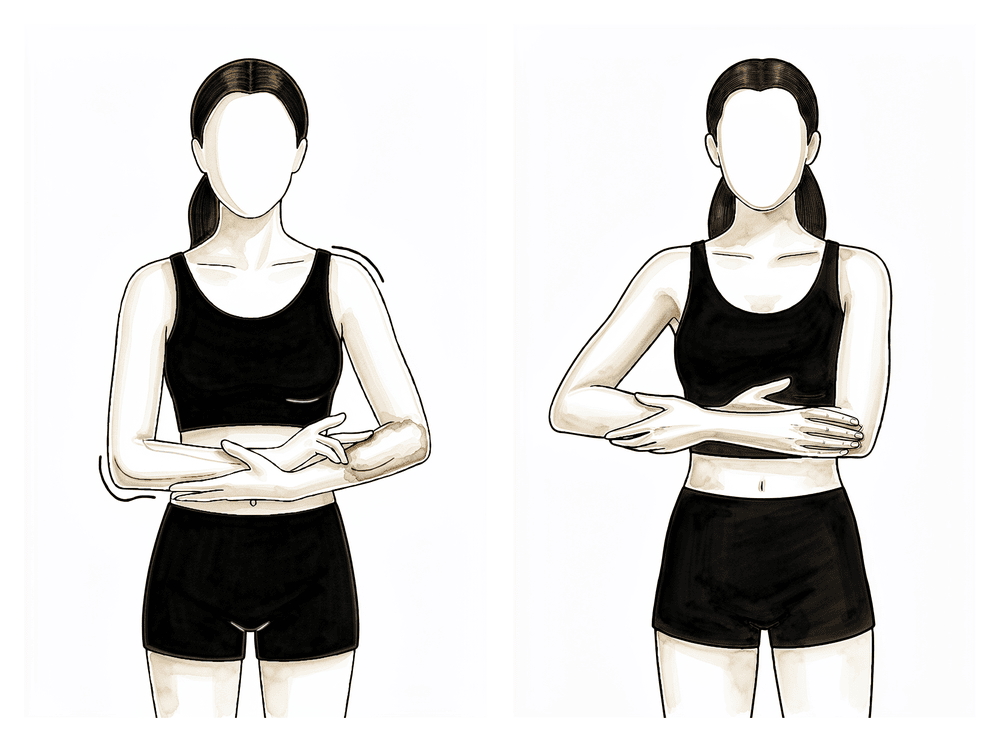
Hỗ trợ gập cánh tay về phía trước
Ngồi trên ghế và hơi cúi người về phía trước; dùng tay còn lại ôm lấy cánh tay vừa được phẫu thuật rồi nhẹ nhàng nâng nó lên phía trước người. Sau đó, dùng tay không phẫu thuật để hỗ trợ hạ cánh tay xuống. Nếu thích, bạn cũng có thể nằm ngửa trên giường và dùng tay không phẫu thuật để nâng cánh tay lên.
10 lần, 3 lần mỗi ngày
Kieran Hirpara 4.0
Hỗ trợ vận động cánh tay ra xa thân
Ngồi trên ghế và hơi nghiêng người về phía trước; sau đó ôm lấy cánh tay và nhẹ nhàng đưa nó sang bên cạnh (giống như cách ru em bé vậy).
10 lần, 3 lần mỗi ngày
Kieran Hirpara 4.0
Xoay ngoài
Ngồi trên ghế, chỉ cần di chuyển cánh tay từ vị trí đang được treo trong dây đeo sao cho nó hướng thẳng về phía trước. Đừng di chuyển cánh tay ra ngoài quá mức.
10 lần, 3 lần mỗi ngày.

Kieran Hirpara 4.0
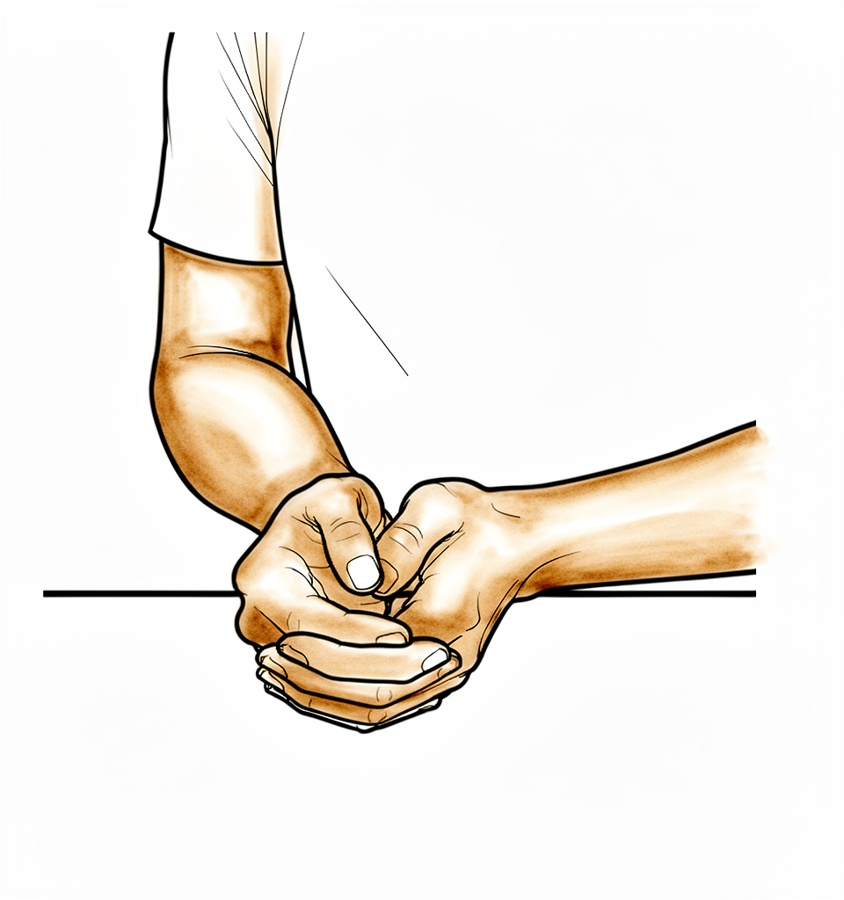
Siết giữ cơ thang dưới
Hãy siết hai xương bả vai xuống dưới và khép lại gần nhau.
Giữ nguyên trong 5 giây, thực hiện 5 lần, ngày 3 lần.
Kieran Hirpara 4.0
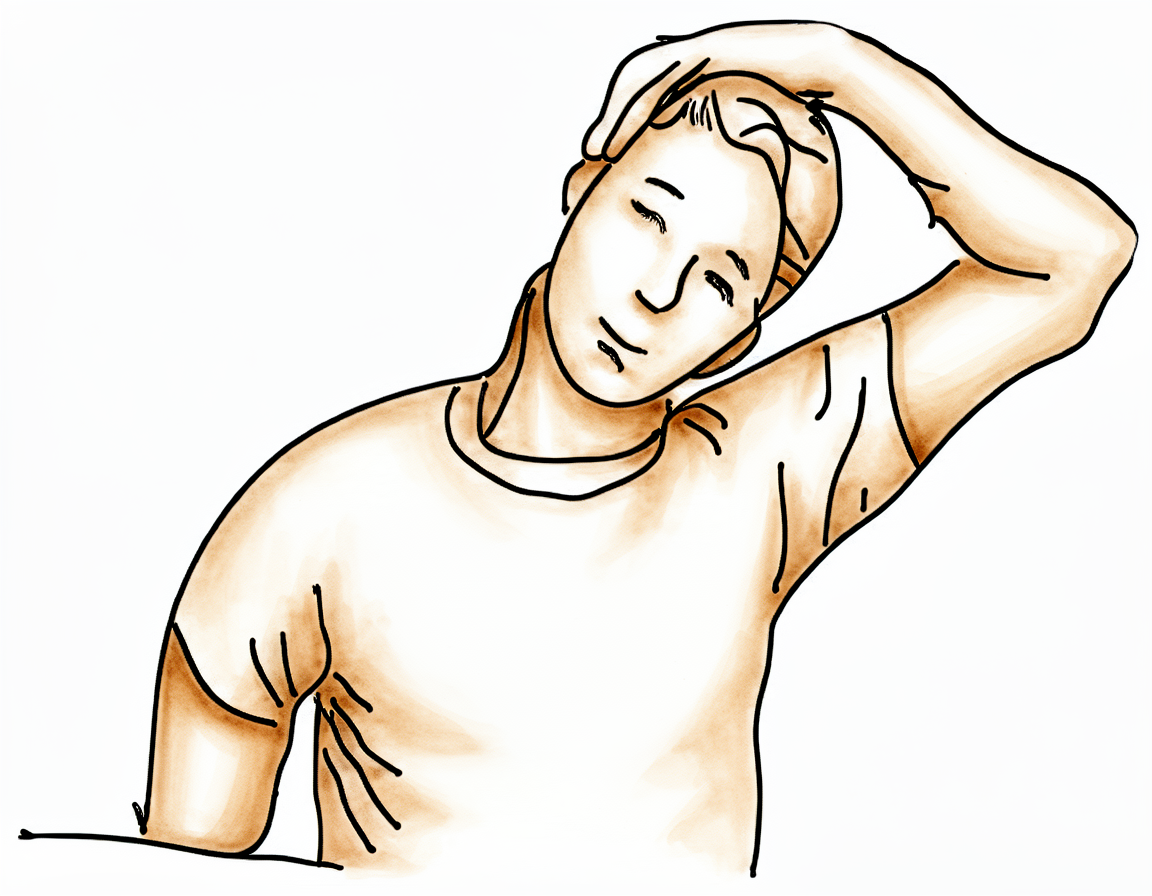
Kéo giãn cơ thang trên
Hãy dùng cánh tay chưa được phẫu thuật để đưa tai về phía vai, hướng ra xa phía cánh tay đã phẫu thuật.
Giữ nguyên trong 10 giây, thực hiện 3 lần, ngày 3 lần.
Kieran Hirpara 4.0
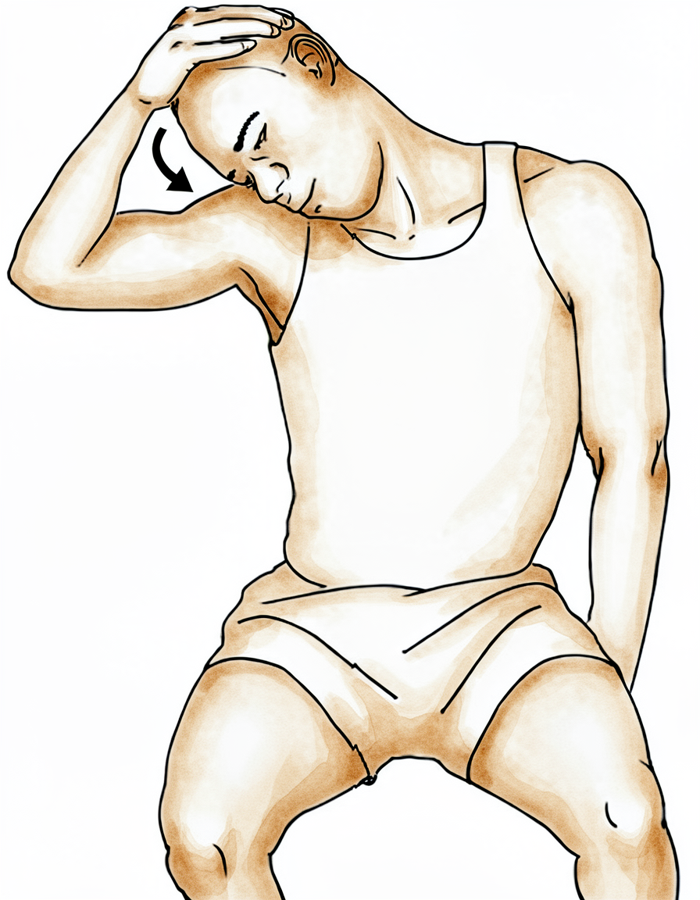
Bài tập kéo giãn cơ nâng xương bả vai
Hãy dùng cánh tay chưa được phẫu thuật để đưa mũi về phía vùng nách, hướng ra xa khỏi bên đã phẫu thuật.
Giữ nguyên trong 10 giây, thực hiện 3 lần, ngày 3 lần.
Hãy bắt đầu thực hiện những bài tập nhẹ nhàng này tại bệnh viện và tiếp tục thực hiện tại nhà. Các bài tập này nên mang lại cảm giác dễ chịu; hãy giảm mức độ tập nếu cảm thấy đau tăng lên.
Cách đeo nẹp cố định
- Bạn có thể tháo tay ra khỏi nẹp để tập luyện và tắm rửa.
- Bạn cần đeo nẹp trong 6 tuần, đặc biệt là khi ra ngoài.
- Bạn không cần phải đeo nẹp khi ngủ.
- Nếu cần, hãy chườm đá để giảm đau.
- Khi đeo nẹp, hãy thả lỏng vai và để nẹp gánh hết trọng lượng của cánh tay.
- Hãy uống thuốc giảm đau trước khi tập luyện và trước các buổi trị liệu vật lý.
- Trừ khi bạn đã tự sắp xếp dịch vụ trị liệu vật lý, chúng tôi đã đặt lịch cho bạn; thông tin chi tiết có trong bộ hồ sơ xuất viện.
- Nếu gặp bất kỳ vấn đề nào, hãy liên hệ với phòng khám hoặc thông báo cho chuyên viên trị liệu vật lý của bạn.
Khi về nhà
Sau khi về nhà, quá trình hồi phục của bạn sẽ tiếp tục theo đúng quy trình phục hồi chức năng sau phẫu thuật: phẫu thuật sửa chữa cơ chóp xoay; thủ thuật ổn định khớp vai phía trước & kỹ thuật Latarjet; thủ thuật ổn định khớp vai phía sau.
Sau khi thực hiện theo phác đồ
Những bài tập sơ khởi này là nền tảng trong quá trình phục hồi tại bệnh viện, được áp dụng chung cho cả ca phẫu thuật sửa chữa cơ chóp xoay và cố định khớp vai: chúng giúp tay, khuỷu tay và vai vẫn có thể vận động nhẹ nhàng trong lúc vết thương đang được bảo vệ. Các mức độ vận động này mang tính chất tham khảo chứ không cố định; quá trình phục hồi tiếp theo sẽ do chuyên viên vật lý trị liệu phối hợp với phòng khám điều chỉnh riêng cho từng bệnh nhân, dựa trên tiến độ hồi phục của vai. Trang này bổ trợ cho các hướng dẫn phục hồi chung của phòng khám; vui lòng tham khảo mục kiểm soát cơn đau sau phẫu thuật và chăm sóc vết thương. Phác đồ phục hồi chi tiết, phù hợp với từng ca phẫu thuật sẽ được trình bày trong tài liệu riêng của bạn (đã được liên kết ở trên). Các bằng chứng khoa học liên quan đến giai đoạn sớm này – bao gồm các nghiên cứu so sánh giữa việc vận động sớm và trì hoãn sau khi sửa chữa cơ chóp xoay, cũng như các bằng chứng về việc cố định khớp sau phẫu thuật ổn định khớp vai – được tóm tắt trong mục “Bằng chứng khoa học”, có sẵn dưới dạng tệp PDF ở đầu trang này.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: This is the early in-hospital / early-protected phase of a combined pathway covering patients who had a rotator cuff repair and/or a shoulder stabilisation procedure (anterior labral/Bankart repair, Latarjet, or posterior labral/capsular repair). It deliberately stops at the point of discharge plus the first protected weeks — the gentle hand/elbow/shoulder exercises that keep the limb moving while the repair is protected by the sling. The full, operation-specific rehabilitation course lives in the parent protocols, which this page hands the patient back to once they go home:
Defining principle of this early phase — PROTECT the repair: Unlike a frozen-shoulder release (where immediate aggressive motion is the goal), a cuff repair and a labral/capsular stabilisation both create a construct that must heal undisturbed. So the early phase is the same for both: sling immobilisation, gentle/passive-only motion within safe limits, and NO active or resisted shoulder work. Tendon-to-bone and labrum-to-bone healing is weak in the first weeks, so the sling and the movement limits are the protectors. The hand, wrist and elbow are kept moving freely throughout (these don't stress the repair) to prevent swelling and stiffness; the shoulder itself is only moved passively/with assistance within the limits the surgeon and physiotherapist set.
The early in-hospital phase (what this page covers)
In the first hours-to-days after surgery the aims are simple and shared across both operation families:
- Protect the repair — arm in the sling, no active lifting or reaching, no loading.
- Keep the rest of the limb moving — wrist, fingers and elbow exercises to prevent swelling and stiffness (these put no stress on the cuff or labral repair).
- Gentle, assisted shoulder motion only — pendulums and assisted/passive elevation within a safe arc; for an anterior repair, external rotation is limited; for a posterior repair, internal rotation and reaching behind the back are limited (the at-risk directions are opposite).
- Pain control and a safe discharge plan — analgesia before exercise, sling instructions, and a physiotherapy follow-up arranged in the discharge pack.
The standalone protocols then drive the rest of recovery (the full sling-weaning schedule, when active motion and strengthening begin, and return to work/sport). The same first-phase principles appear at the head of each of those protocols — this inpatient page simply consolidates that shared early phase for patients who had the procedure(s) performed together or are still in hospital.
Evidence by theme
Theme 1 — Early vs delayed motion after rotator cuff repair (the central debate)
This is the best-studied question that shapes the early phase, and the corpus is rich on it. Two competing concerns: early passive motion reduces post-operative stiffness, while delayed/immobilisation may better protect tendon-to-bone healing (lower retear), especially in larger tears.
- Multiple RCTs and systematic reviews of overlapping meta-analyses converge on the same bottom line: early and delayed passive motion give superior early range of motion for the early group but equivalent final outcomes by ~6–12 months for small-to-medium tears — so timing is largely surgeon preference and does not change the end result [Saltzman 2017; Mazzocca 2017].
- For large/massive tears the balance tilts toward a delayed / protected approach to favour healing [systematic-review/meta-analysis evidence; BMC Musculoskelet Disord 2025].
- A "knowing the speed limit" theme runs through the reviews: tendon repairs are mechanically weak early, and very aggressive early therapy can compromise the construct [Thigpen 2015 review].
Practical consequence for this page: the early in-hospital phase is passive/assisted-only with the sling on regardless of which approach the surgeon ultimately chooses for the home phase — the disagreement in the literature is about how soon to progress, not about whether to protect the repair in the first days. A defining surgical decision (early vs delayed progression, and how it is size-stratified) is made by the surgeon and detailed in the cuff-repair protocol.
Theme 2 — Immobilisation after stabilisation (anterior and posterior)
The stabilisation literature also supports an early protected phase, though high-level evidence is sparser and protocols are more consensus-driven.
- Anterior (Bankart/capsulolabral) repair: the American Society of Shoulder and Elbow Therapists' consensus guideline recommends 0–4 weeks of absolute immobilisation, then relative immobilisation (out of the sling only for exercises) to ~6 weeks, with no forced external rotation/extension for ~3 months; early ER is progressed gradually (e.g. ~15° at 0–2 wk → ~35° at 2–4 wk → ~55° at 4–6 wk). A simple sling is used in the large majority of published protocols.
- Posterior (labral/capsular) repair: the precaution is reversed — the sling is positioned in slight abduction and neutral/slight external rotation, the arm is kept in front of the body, and internal rotation, adduction and reaching behind the back are avoided early. Posterior instability is uncommon (~3–5%), so the protocols are biomechanically reasoned (Level IV–V) rather than RCT-tested.
- Both share the same headline as the cuff-repair early phase: sling on, gentle motion within the safe arc, no active/resisted shoulder work while the labrum/capsule heals.
Early-phase timeline (consolidated; first weeks only)
This focuses on the shared early-protected window and is consistent with the synthesis page. The full operation-specific schedules continue in the parent protocols.
| Phase | Window | Sling | Shoulder motion | Active / strengthening | Notes |
|---|---|---|---|---|---|
| Inpatient / immediate | Day 0 — discharge | On at all times (off only for exercises & showering) | Wrist/hand/elbow moving freely; pendulums; gentle assisted/passive elevation within safe limits | None for the shoulder (no active lift, no resisted work) | Analgesia before exercises; ice for comfort; physiotherapy follow-up arranged |
| Early protected | Week 0–6 | Worn ~6 weeks, especially out of the house; not needed for sleep | Continue gentle assisted/passive motion within limits — anterior repair: limit external rotation; posterior repair: limit internal rotation / no reaching behind the back | Still no active/resisted shoulder work | The sling and the direction limits are the protectors; ease back if pain rises |
| Handover to parent protocol | ~Week 6 onward | Weaned per the operation-specific protocol | Active-assisted → active motion begins in the parent protocol, not here | Strengthening begins later (cuff repair typically ~12 wk; stabilisation per its own schedule) | Recovery continues with the rotator cuff repair, anterior stabilisation & Latarjet, or posterior stabilisation protocol |
The sling duration, the exact motion limits, and when active motion and strengthening begin are surgeon-set clinical decisions; the windows above are the typical shared early phase, not trial-derived precise cut-offs.
Key controversies / evidence quality
- Early vs delayed progression after cuff repair is the one well-studied question, and it is about the home phase rather than the in-hospital phase. RCTs/meta-analyses show equivalent final outcomes for small/medium tears and a protect-healing tilt for large/massive tears — the early in-hospital protected phase is common ground either way. Strong (RCT / SR-MA), but Cochrane-level certainty for any single optimal schedule remains low.
- Stabilisation immobilisation duration and sling position are largely consensus/biomechanical — there is no RCT defining the optimal early regimen, and posterior protocols in particular are extrapolated. Weak–moderate / consensus.
- The combined early-phase protocol itself is a surgeon patient-guidance consolidation, not a trial-derived schedule. It is deliberately brief and defers to the parent protocols for the full course.
Evidence-strength flags (summary)
- STRONG (RCT / SR-MA): early-vs-delayed passive motion after cuff repair → equivalent final outcomes for small/medium tears, protect-healing tilt for large/massive (Saltzman 2017; Mazzocca 2017; BMC Musculoskelet Disord 2025 SR-MA).
- MODERATE / CONSENSUS: anterior stabilisation immobilisation schedule (ASSET/JOSPT consensus guideline); graded early ER limits.
- WEAK / CONSENSUS (Level IV–V): posterior stabilisation sling position and precautions (biomechanical, no RCT); the consolidated early in-hospital protocol itself.
Citations
RAG corpus (180,000+ Orthopaedic articles)
- Saltzman BM, Zuke WA, Go B, et al. Early Versus Delayed Motion After Rotator Cuff Repair: A Systematic Review of Overlapping Meta-analyses. Am J Sports Med. 2017. DOI: 10.1177/0363546517692543
- Mazzocca AD, Arciero RA, Shea KP, et al. The Effect of Early Range of Motion on Quality of Life, Clinical Outcome, and Repair Integrity After Arthroscopic Rotator Cuff Repair. Arthroscopy. 2017. DOI: 10.1016/j.arthro.2016.10.017
- Effects of early exercise and immobilization after arthroscopic rotator cuff repair surgery: a systematic review and meta-analysis of randomized controlled trials. BMC Musculoskelet Disord. 2025. DOI: 10.1186/s12891-025-08500-7
- Which is better? Early versus delayed rehabilitation after arthroscopic rotator cuff repair. Knee Surg Sports Traumatol Arthrosc. 2024. DOI: 10.1002/ksa.12129
- Thigpen CA, Shaffer MA, Kissenberth MJ. Knowing the Speed Limit (post-cuff-repair rehab progression). Clin Sports Med. 2015. DOI: 10.1016/j.csm.2014.12.007
- Rehabilitation Following Arthroscopic Rotator Cuff Repair. J Bone Joint Surg. DOI: 10.2106/jbjs.m.00034
- Anterior Shoulder Instability Part I — Diagnosis, Nonoperative Management, and Bankart Repair — An International Consensus Statement. Arthroscopy. 2021. DOI: 10.1016/j.arthro.2021.07.022
Literature / consensus guidelines (URLs)
- The American Society of Shoulder and Elbow Therapists' Consensus Rehabilitation Guideline for Arthroscopic Anterior Capsulolabral Repair of the Shoulder. JOSPT. 2010. https://www.jospt.org/doi/10.2519/jospt.2010.3186
- Rehabilitation Protocol Variability Following Arthroscopic Bankart Repair and Remplissage: A Systematic Review. Int J Sports Phys Ther. https://pmc.ncbi.nlm.nih.gov/articles/PMC11446737/
- Current Concepts in Rehabilitation for Traumatic Anterior Shoulder Instability. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC5685970/
- Rehabilitation Following Posterior Shoulder Stabilization (clinical commentary). PMC8168996. https://pmc.ncbi.nlm.nih.gov/articles/PMC8168996/
Published patient/rehab protocols (basis for the early-phase structure)
- Massachusetts General Hospital — Rehabilitation Protocol for Bankart Repair. https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-bankart-repair.pdf
- University of Virginia Sports Medicine — Posterior Labral Repair Rehabilitation Protocol. https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2021/06/Posterior-Labral-Repair.pdf
- Brigham & Women's Hospital — Arthroscopic Rotator Cuff Repair Protocol (early protected phase, tear-size stratification). https://www.brighamandwomens.org/assets/BWH/patients-and-families/rehabilitation-services/pdfs/shoulder-arthroscopic-rct-repair-protocol-hybrid-patient-therapist.pdf





