

住院期间锻炼——肩袖与稳定性 资料
这些是肩袖修复或肩关节稳定术后在院内开始的温和锻炼。它们可在修复愈合期间保持手部、肘部和肩部的活动。
您的锻炼

Kieran Hirpara 4.0
腕部运动
通过向前、向后及左右弯曲手腕来保持手部活动。
10次,每日3次

Kieran Hirpara 4.0
张开和握紧手
通过反复张开和握紧手部及手指,或挤压压力球,保持手部和手指的活动。
10次,每日3次

Kieran Hirpara 4.0
肘部弯曲
弯曲并伸直您的肘部。
10次,每日3次

Kieran Hirpara 4.0
钟摆
这是一项被动练习。身体前倾,让手臂自然下垂放松。利用身体带动手臂,沿顺时针或逆时针方向轻柔地移动,同时配合前后及左右方向的摆动。
每个方向约30秒,每日3次

Kieran Hirpara 4.0
辅助前屈
坐在椅子上并身体前倾,用另一只手臂托住手术侧手臂,轻轻将其向上移动至身前。借助非手术侧手臂的帮助将其放回原位。如果您愿意,也可以仰卧在床上,协助手臂向上移动。
10次,每日3次
Kieran Hirpara 4.0
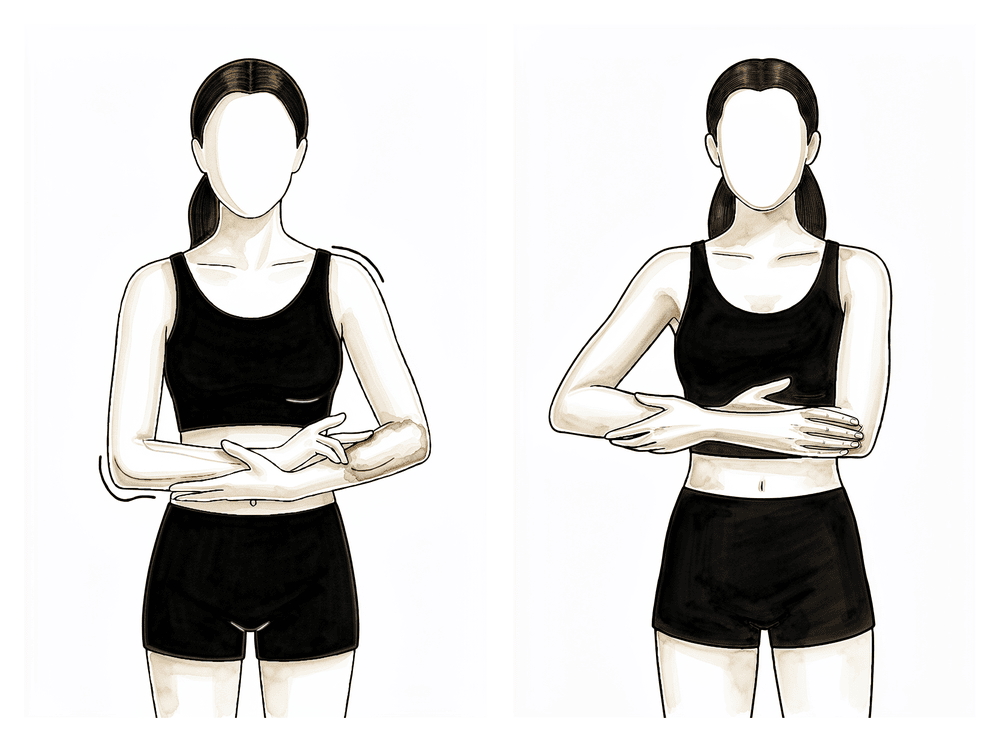
辅助外展
坐在椅子上,身体前倾,再次托住手臂,帮助其向外侧移动(如同摇动婴儿般)。
10次,每日3次
Kieran Hirpara 4.0
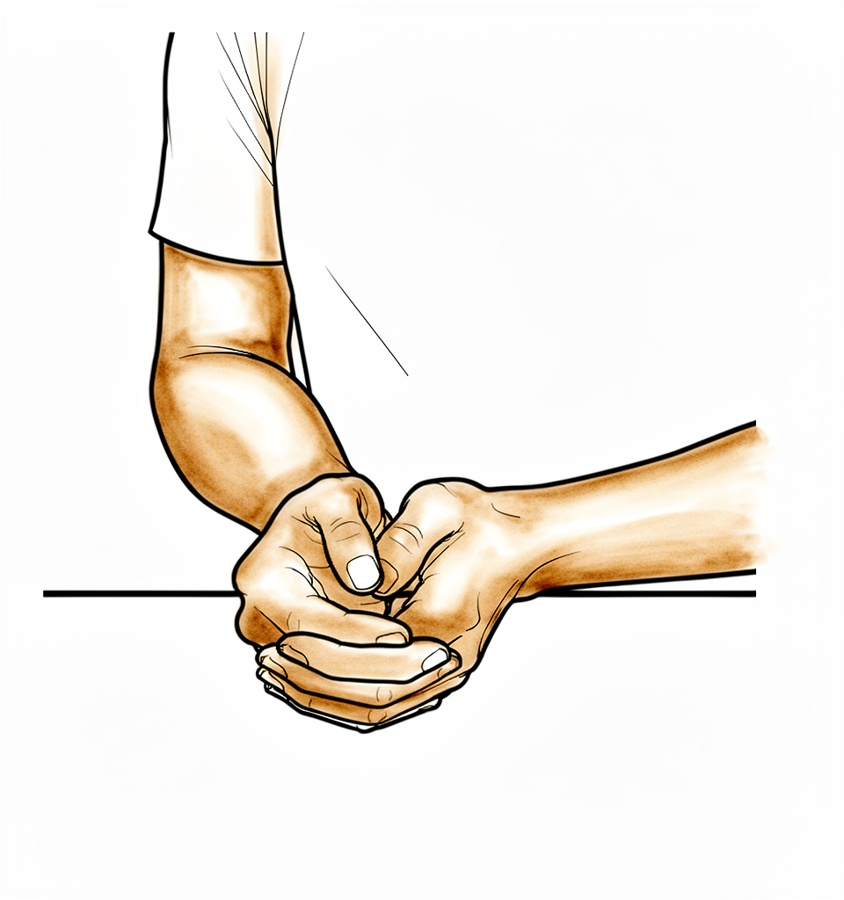
外旋
坐在椅子上,仅将手臂从悬吊带中的位置移动至正前方伸直。不要向外侧移动更多。
10次,每日3次

Kieran Hirpara 4.0
下斜方肌激活
将肩胛骨向下并向内收拢。
保持 5 秒,5 次,每天 3 次
Kieran Hirpara 4.0
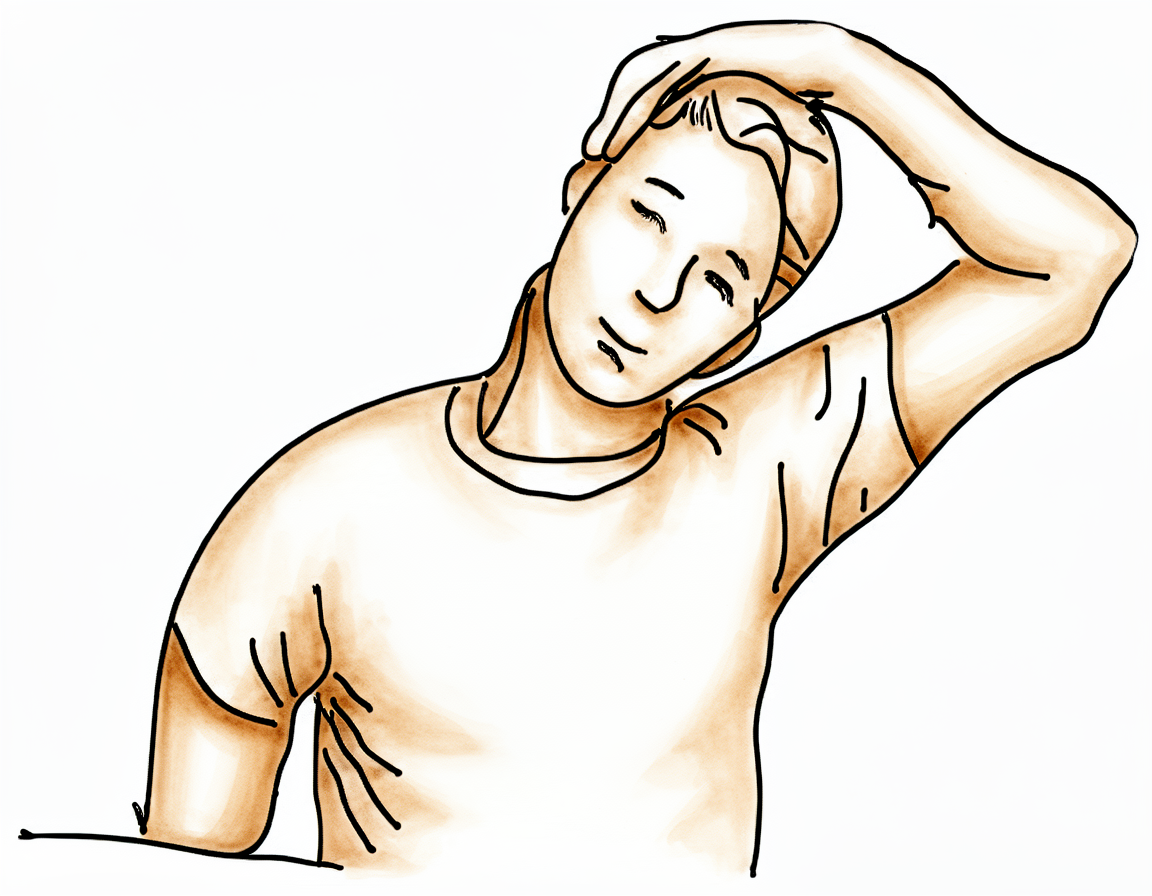
上斜方肌拉伸
用您的非手术侧手臂将耳朵向同侧肩部方向移动,远离手术侧。
保持10秒,3次,每天3次
Kieran Hirpara 4.0
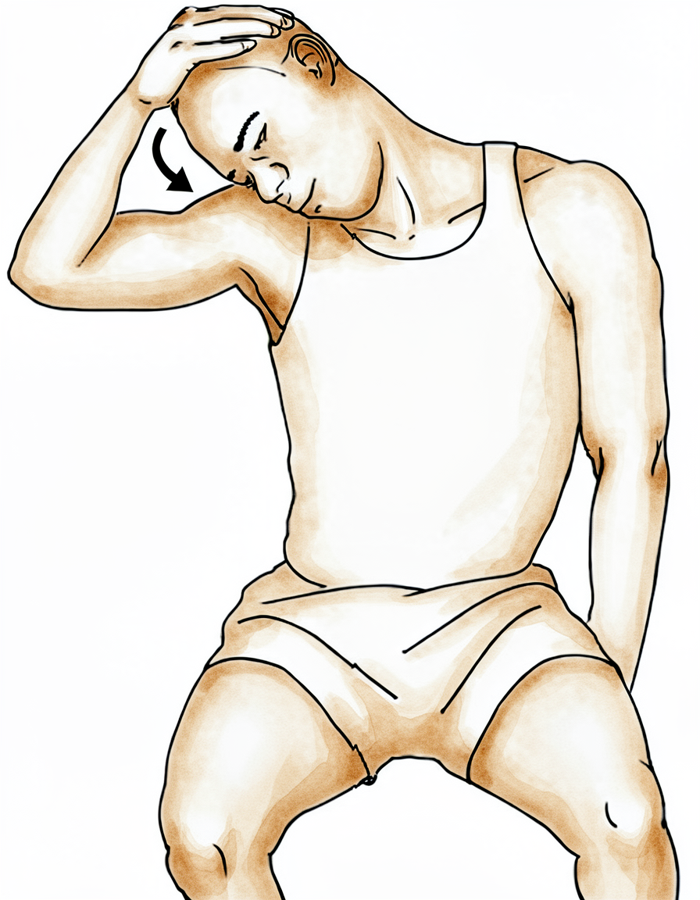
肩胛提肌拉伸
使用您的非手术侧手臂,将鼻子移向腋窝区域,远离手术侧。
保持10秒,3次,每天3次
请在医院开始进行这些温和的锻炼,并在回家后继续。它们应当是舒适的;如果疼痛加剧,请减轻强度。
佩戴悬吊带
- 您可以将手臂从悬吊带中取出以进行锻炼和淋浴。
- 您需要佩戴悬吊带 6 周,尤其是在外出时。
- 您无需在睡觉时佩戴悬吊带。
- 如有需要,请使用冰敷以缓解疼痛。
- 佩戴悬吊带时,请放松肩部,让悬吊带承担手臂的重量。
- 在进行锻炼和物理治疗预约前,请服用止痛药。
- 除非您已自行安排物理治疗,否则已为您预约了物理治疗,详情见您的出院资料包。
- 如果您遇到任何问题,请联系诊室或告知您的物理治疗师。
回家时
回家后,您的康复将继续按照手术后的完整康复方案进行:肩袖修复;前方稳定术与 Latarjet 术;后方稳定术。
您的术后方案之后
这些早期练习是肩袖修复和肩关节稳定化手术在院内阶段的共同起点:它们在保护修复部位的同时,保持手部、肘部和肩部的轻柔活动。剂量为典型值而非固定值,您的后续康复将根据肩关节的恢复情况,由您的物理治疗师与诊所协作,进行个体化指导。本页与诊所的通用康复建议相辅相成;请参阅术后疼痛管理和伤口护理。完整的、针对特定手术的疗程将在您自己的方案中继续(链接见上方)。这一早期阶段的证据基础(肩袖修复后早期与延迟活动研究的对比,以及稳定化术后制动的相关证据)已在证据部分进行总结,可从本页顶部获取 PDF 文件。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: This is the early in-hospital / early-protected phase of a combined pathway covering patients who had a rotator cuff repair and/or a shoulder stabilisation procedure (anterior labral/Bankart repair, Latarjet, or posterior labral/capsular repair). It deliberately stops at the point of discharge plus the first protected weeks — the gentle hand/elbow/shoulder exercises that keep the limb moving while the repair is protected by the sling. The full, operation-specific rehabilitation course lives in the parent protocols, which this page hands the patient back to once they go home:
Defining principle of this early phase — PROTECT the repair: Unlike a frozen-shoulder release (where immediate aggressive motion is the goal), a cuff repair and a labral/capsular stabilisation both create a construct that must heal undisturbed. So the early phase is the same for both: sling immobilisation, gentle/passive-only motion within safe limits, and NO active or resisted shoulder work. Tendon-to-bone and labrum-to-bone healing is weak in the first weeks, so the sling and the movement limits are the protectors. The hand, wrist and elbow are kept moving freely throughout (these don't stress the repair) to prevent swelling and stiffness; the shoulder itself is only moved passively/with assistance within the limits the surgeon and physiotherapist set.
The early in-hospital phase (what this page covers)
In the first hours-to-days after surgery the aims are simple and shared across both operation families:
- Protect the repair — arm in the sling, no active lifting or reaching, no loading.
- Keep the rest of the limb moving — wrist, fingers and elbow exercises to prevent swelling and stiffness (these put no stress on the cuff or labral repair).
- Gentle, assisted shoulder motion only — pendulums and assisted/passive elevation within a safe arc; for an anterior repair, external rotation is limited; for a posterior repair, internal rotation and reaching behind the back are limited (the at-risk directions are opposite).
- Pain control and a safe discharge plan — analgesia before exercise, sling instructions, and a physiotherapy follow-up arranged in the discharge pack.
The standalone protocols then drive the rest of recovery (the full sling-weaning schedule, when active motion and strengthening begin, and return to work/sport). The same first-phase principles appear at the head of each of those protocols — this inpatient page simply consolidates that shared early phase for patients who had the procedure(s) performed together or are still in hospital.
Evidence by theme
Theme 1 — Early vs delayed motion after rotator cuff repair (the central debate)
This is the best-studied question that shapes the early phase, and the corpus is rich on it. Two competing concerns: early passive motion reduces post-operative stiffness, while delayed/immobilisation may better protect tendon-to-bone healing (lower retear), especially in larger tears.
- Multiple RCTs and systematic reviews of overlapping meta-analyses converge on the same bottom line: early and delayed passive motion give superior early range of motion for the early group but equivalent final outcomes by ~6–12 months for small-to-medium tears — so timing is largely surgeon preference and does not change the end result [Saltzman 2017; Mazzocca 2017].
- For large/massive tears the balance tilts toward a delayed / protected approach to favour healing [systematic-review/meta-analysis evidence; BMC Musculoskelet Disord 2025].
- A "knowing the speed limit" theme runs through the reviews: tendon repairs are mechanically weak early, and very aggressive early therapy can compromise the construct [Thigpen 2015 review].
Practical consequence for this page: the early in-hospital phase is passive/assisted-only with the sling on regardless of which approach the surgeon ultimately chooses for the home phase — the disagreement in the literature is about how soon to progress, not about whether to protect the repair in the first days. A defining surgical decision (early vs delayed progression, and how it is size-stratified) is made by the surgeon and detailed in the cuff-repair protocol.
Theme 2 — Immobilisation after stabilisation (anterior and posterior)
The stabilisation literature also supports an early protected phase, though high-level evidence is sparser and protocols are more consensus-driven.
- Anterior (Bankart/capsulolabral) repair: the American Society of Shoulder and Elbow Therapists' consensus guideline recommends 0–4 weeks of absolute immobilisation, then relative immobilisation (out of the sling only for exercises) to ~6 weeks, with no forced external rotation/extension for ~3 months; early ER is progressed gradually (e.g. ~15° at 0–2 wk → ~35° at 2–4 wk → ~55° at 4–6 wk). A simple sling is used in the large majority of published protocols.
- Posterior (labral/capsular) repair: the precaution is reversed — the sling is positioned in slight abduction and neutral/slight external rotation, the arm is kept in front of the body, and internal rotation, adduction and reaching behind the back are avoided early. Posterior instability is uncommon (~3–5%), so the protocols are biomechanically reasoned (Level IV–V) rather than RCT-tested.
- Both share the same headline as the cuff-repair early phase: sling on, gentle motion within the safe arc, no active/resisted shoulder work while the labrum/capsule heals.
Early-phase timeline (consolidated; first weeks only)
This focuses on the shared early-protected window and is consistent with the synthesis page. The full operation-specific schedules continue in the parent protocols.
| Phase | Window | Sling | Shoulder motion | Active / strengthening | Notes |
|---|---|---|---|---|---|
| Inpatient / immediate | Day 0 — discharge | On at all times (off only for exercises & showering) | Wrist/hand/elbow moving freely; pendulums; gentle assisted/passive elevation within safe limits | None for the shoulder (no active lift, no resisted work) | Analgesia before exercises; ice for comfort; physiotherapy follow-up arranged |
| Early protected | Week 0–6 | Worn ~6 weeks, especially out of the house; not needed for sleep | Continue gentle assisted/passive motion within limits — anterior repair: limit external rotation; posterior repair: limit internal rotation / no reaching behind the back | Still no active/resisted shoulder work | The sling and the direction limits are the protectors; ease back if pain rises |
| Handover to parent protocol | ~Week 6 onward | Weaned per the operation-specific protocol | Active-assisted → active motion begins in the parent protocol, not here | Strengthening begins later (cuff repair typically ~12 wk; stabilisation per its own schedule) | Recovery continues with the rotator cuff repair, anterior stabilisation & Latarjet, or posterior stabilisation protocol |
The sling duration, the exact motion limits, and when active motion and strengthening begin are surgeon-set clinical decisions; the windows above are the typical shared early phase, not trial-derived precise cut-offs.
Key controversies / evidence quality
- Early vs delayed progression after cuff repair is the one well-studied question, and it is about the home phase rather than the in-hospital phase. RCTs/meta-analyses show equivalent final outcomes for small/medium tears and a protect-healing tilt for large/massive tears — the early in-hospital protected phase is common ground either way. Strong (RCT / SR-MA), but Cochrane-level certainty for any single optimal schedule remains low.
- Stabilisation immobilisation duration and sling position are largely consensus/biomechanical — there is no RCT defining the optimal early regimen, and posterior protocols in particular are extrapolated. Weak–moderate / consensus.
- The combined early-phase protocol itself is a surgeon patient-guidance consolidation, not a trial-derived schedule. It is deliberately brief and defers to the parent protocols for the full course.
Evidence-strength flags (summary)
- STRONG (RCT / SR-MA): early-vs-delayed passive motion after cuff repair → equivalent final outcomes for small/medium tears, protect-healing tilt for large/massive (Saltzman 2017; Mazzocca 2017; BMC Musculoskelet Disord 2025 SR-MA).
- MODERATE / CONSENSUS: anterior stabilisation immobilisation schedule (ASSET/JOSPT consensus guideline); graded early ER limits.
- WEAK / CONSENSUS (Level IV–V): posterior stabilisation sling position and precautions (biomechanical, no RCT); the consolidated early in-hospital protocol itself.
Citations
RAG corpus (180,000+ Orthopaedic articles)
- Saltzman BM, Zuke WA, Go B, et al. Early Versus Delayed Motion After Rotator Cuff Repair: A Systematic Review of Overlapping Meta-analyses. Am J Sports Med. 2017. DOI: 10.1177/0363546517692543
- Mazzocca AD, Arciero RA, Shea KP, et al. The Effect of Early Range of Motion on Quality of Life, Clinical Outcome, and Repair Integrity After Arthroscopic Rotator Cuff Repair. Arthroscopy. 2017. DOI: 10.1016/j.arthro.2016.10.017
- Effects of early exercise and immobilization after arthroscopic rotator cuff repair surgery: a systematic review and meta-analysis of randomized controlled trials. BMC Musculoskelet Disord. 2025. DOI: 10.1186/s12891-025-08500-7
- Which is better? Early versus delayed rehabilitation after arthroscopic rotator cuff repair. Knee Surg Sports Traumatol Arthrosc. 2024. DOI: 10.1002/ksa.12129
- Thigpen CA, Shaffer MA, Kissenberth MJ. Knowing the Speed Limit (post-cuff-repair rehab progression). Clin Sports Med. 2015. DOI: 10.1016/j.csm.2014.12.007
- Rehabilitation Following Arthroscopic Rotator Cuff Repair. J Bone Joint Surg. DOI: 10.2106/jbjs.m.00034
- Anterior Shoulder Instability Part I — Diagnosis, Nonoperative Management, and Bankart Repair — An International Consensus Statement. Arthroscopy. 2021. DOI: 10.1016/j.arthro.2021.07.022
Literature / consensus guidelines (URLs)
- The American Society of Shoulder and Elbow Therapists' Consensus Rehabilitation Guideline for Arthroscopic Anterior Capsulolabral Repair of the Shoulder. JOSPT. 2010. https://www.jospt.org/doi/10.2519/jospt.2010.3186
- Rehabilitation Protocol Variability Following Arthroscopic Bankart Repair and Remplissage: A Systematic Review. Int J Sports Phys Ther. https://pmc.ncbi.nlm.nih.gov/articles/PMC11446737/
- Current Concepts in Rehabilitation for Traumatic Anterior Shoulder Instability. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC5685970/
- Rehabilitation Following Posterior Shoulder Stabilization (clinical commentary). PMC8168996. https://pmc.ncbi.nlm.nih.gov/articles/PMC8168996/
Published patient/rehab protocols (basis for the early-phase structure)
- Massachusetts General Hospital — Rehabilitation Protocol for Bankart Repair. https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-bankart-repair.pdf
- University of Virginia Sports Medicine — Posterior Labral Repair Rehabilitation Protocol. https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2021/06/Posterior-Labral-Repair.pdf
- Brigham & Women's Hospital — Arthroscopic Rotator Cuff Repair Protocol (early protected phase, tear-size stratification). https://www.brighamandwomens.org/assets/BWH/patients-and-families/rehabilitation-services/pdfs/shoulder-arthroscopic-rct-repair-protocol-hybrid-patient-therapist.pdf





