

手指手术 资料
本方案指导您在 Mater Private Hospital Rockhampton 接受 Kieran Hirpara 医生手指手术后的康复。它说明了术后数周的预期情况,并制定了有助于恢复手指和手部活动及功能的锻炼计划。请在首次物理治疗或手部治疗就诊时携带此页面或其 PDF 文件,以确保您的康复过程协调一致;您的治疗师可能会根据您的手术类型及康复进展调整计划。
如果您对术后伤口有任何疑虑,请联系诊所。拍摄伤口照片并通过电子邮件发送以供审阅通常很有帮助。
预期情况
您的伤口护理说明详见诊所的伤口护理手册。以下练习对于恢复手指和手部的活动度及功能至关重要。
伤口愈合后,在进行这些练习前,请先对您的手部进行20分钟的热敷。完成练习后,请进行冰敷以缓解任何肿胀或炎症。
待伤口完全愈合后,开始进行瘢痕按摩:在切口处进行有力的环形按摩。有关瘢痕管理的更多信息,请参阅伤口护理手册。
请密切监测肿胀情况,如有任何疑虑,请致电诊所或咨询手部治疗师。
大多数手指手术后的康复基于三项原则,以下练习将逐一落实这些原则。第一是控制肿胀:持续的手部肿胀会导致软组织僵硬,并限制肌腱和关节的活动能力,因此在早期几周,抬高患肢、轻柔活动以及(在必要时)逆行按摩和加压是优先事项 [1]。第二是早期、轻柔的活动:手指会迅速僵硬,因此在特定手术规定的限制范围内活动手指(一旦伤口和手术情况允许,应尽早开始),可保持小关节的柔韧性,并有助于肌腱在周围愈合的组织中顺畅滑动而非粘连。第三是肌腱滑动。您手册中列出的不同手指姿势(伸直、钩状、桌面状和全握拳)并非随意设定:每种姿势都会使深层和浅层手指肌腱相对于彼此以及腱鞘产生不同程度的移动,这正是保持肌腱自由滑动的原因 [2]。远端指间关节(DIP)和近端指间关节(PIP)的阻挡练习旨在针对同一滑动机制,逐关节进行训练。少量多次是基本原则:全天持续、频繁、轻柔的练习比偶尔的剧烈努力更有利于您的康复。
注意事项与限制
鼓励对手进行轻度功能性使用,以完成日常生活动作,如自我护理、进食、穿衣、书写和打字(除非另有医嘱)。根据损伤情况及所实施的手术,术后通常需避免提重物、抓握、负重及冲击,时间最长可达6周。您将在术后复查时获得关于注意事项和限制的更多指导。
致物理治疗师:
管理
- 伤口和疤痕护理遵循本机构的伤口护理手册;待伤口完全愈合后,开始进行疤痕按摩(在切口处进行有力的环形按摩)
- 伤口愈合后,在进行锻炼计划前,先对患手进行20分钟的热敷;锻炼后冰敷以减轻肿胀和炎症
- 监测肿胀情况;如有疑虑,请上报至诊室或手外科治疗师
- 若肿胀过度或消退缓慢,消肿控制是优先事项:首选抬高患肢和主动活动,辅以逆行按摩、加压包扎和手法消肿动员,并结合标准治疗 [1]
- 家庭锻炼计划如下方卡片所示:腕关节屈曲/伸展;远端指间关节(DIP)和近端指间关节(PIP)关节阻挡;肌腱滑动(A系列和B系列)
- 肌腱滑动和关节阻挡序列旨在最大化屈肌腱相对于彼此及腱鞘的差异化滑动:应变换体位(直位、钩状位、桌面位、握拳位),而非重复单一位置 [2]
注意事项
- 鼓励对手进行轻度功能性使用,以完成日常生活动作(自我护理、进食、穿衣、书写、打字),除非另有医嘱
- 术后避免提重物、抓握、负重或冲击,时间最长可达6周(取决于损伤/所实施的手术)
- 具体的注意事项和限制将在术后复查时确认
- 这是一般性的术后手指锻炼计划;若特定手术本身带有保护范围、运动限制或夹板固定(例如肌腱修复术后),则以手术特定的指示为准
这些是出自您手册中的锻炼动作,请按照物理治疗师或手外科治疗师的指导,在家中继续执行。
您的练习

Kieran Hirpara 4.0
腕关节屈曲/伸展
将肘部支撑在桌面上,轻轻前后摆动手腕(或如图所示,将手腕悬空置于桌边或扶手椅边缘)。待感觉较为舒适后,用另一只手握住手掌,将手腕向后推,使手指指向天花板,然后反向推,使手指指向地面。保持手指放松——它们会自行弯曲或伸直。每个拉伸动作保持15秒;每个方向重复5次。
10 次,4–5 次/天
Kieran Hirpara 4.0
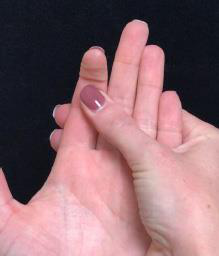
远端指间关节阻挡练习
掌心向上,用另一只手在末节指间关节(远端指间关节,DIP)下方支撑患手。弯曲并伸直末节指间关节,每个姿势保持3–5秒。仅对中间关节提供足够的支撑,使其不发生弯曲。在此练习过程中,其他手指移动是可以接受的。
10次,每天4次,每日
Kieran Hirpara 4.0
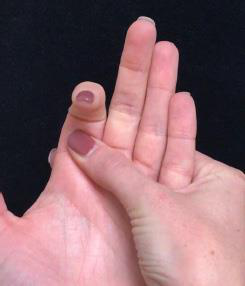
近端指间关节阻挡
掌心向上,用另一只手在第二关节——即近端指间关节(PIP关节)——下方支撑患手。在中间关节处弯曲并伸直手指,每个姿势保持3–5秒。其他手指同时活动也是可以的。
10次,每天4次,每日
Kieran Hirpara 4.0
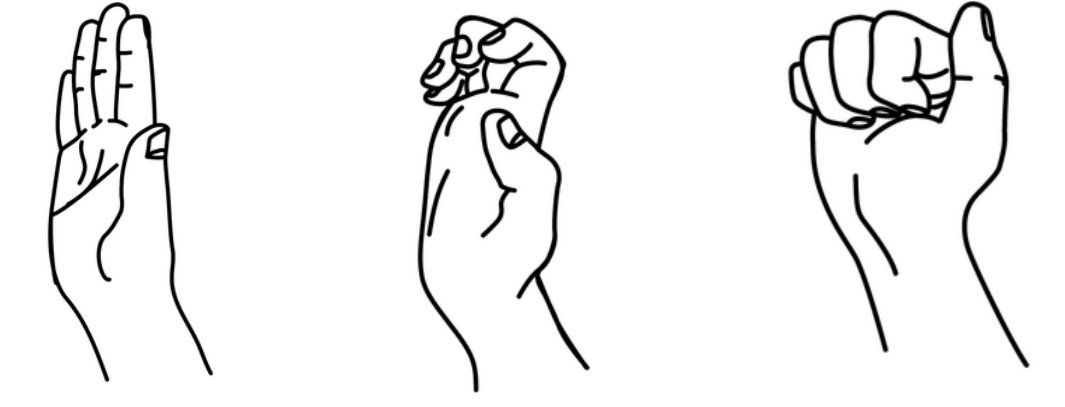
肌腱滑动 — A 系列
将手置于身前,手腕保持伸直,完全伸直所有手指(1)。将指尖弯曲至“钩”状位置,指关节朝上(2)。拇指置于手指上方,握紧拳头(3)。
5–10 次,每天 2–3 次,每日
Kieran Hirpara 4.0
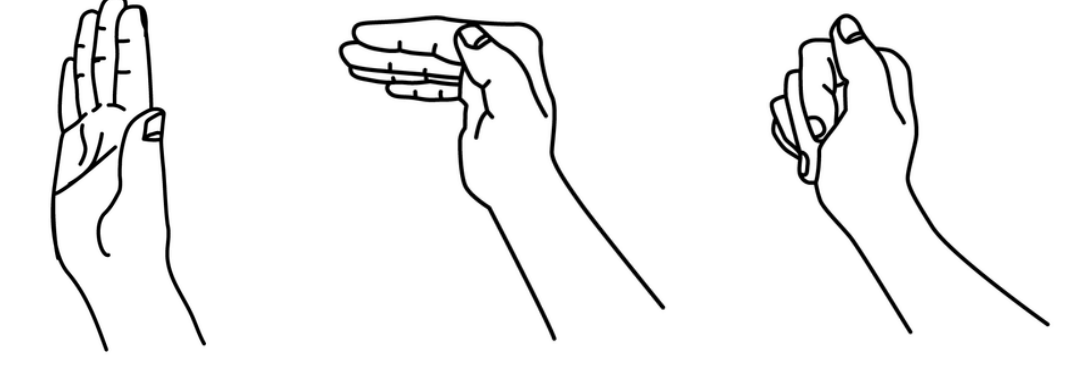
腱滑动——B系列
将手置于身前,手腕保持伸直,将所有手指完全伸直(1)。通过弯曲手指最下方的关节(掌指关节)并保持手指伸直,使手指呈“桌面”状——确保手腕不向前下垂(2)。在中间关节处弯曲手指,使手指触及手掌(3)。
5–10 次,每天 2–3 次,每日
请仅在Hirpara医生和您的手部治疗师的指导下开始进行下面这些练习,并严格保持在您被允许的活动范围和限制之内。阻挡练习是特定的练习:通过固定下方的关节,您迫使运动发生在您试图松解的关节上,而不是在已经容易活动的关节上。肌腱滑动系列练习可保持屈肌腱在腱鞘内顺畅滑动,而手腕拉伸则防止在手指成为重点时手腕僵硬。少量多次比偶尔长时间练习效果更好。停止任何引起剧烈疼痛的动作。
您的方案之后
本方案与本诊所的一般康复建议配合使用;请参阅术后疼痛管理、伤口护理和手部治疗基础。对于本程序常用于其后的手术,请参阅扳机指松解术和杜普伊特伦腱鞘纤维瘤切除术。
本运动方案由认证手部治疗师 Sarah Farrell(BOccThy)合作撰写。
参考文献
[1] Miller LK, Jerosch-Herold C, Shepstone L. Effectiveness of edema management techniques for subacute hand edema: a systematic review. J Hand Ther. 2017;30(4):432–446. https://pubmed.ncbi.nlm.nih.gov/28807598/ [2] Wehbé MA, Hunter JM. Flexor tendon gliding in the hand. Part II. Differential gliding. J Hand Surg Am. 1985;10(4):575–579. https://pubmed.ncbi.nlm.nih.gov/4020073/
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: This is a general post-operative finger rehabilitation program, not a single-procedure protocol. It applies as the default hand-therapy pathway after common finger operations where the repaired or released structure does not mandate its own protected range — most typically trigger finger (A1 pulley) release and Dupuytren's fasciectomy, and as a baseline mobility/oedema program after finger fracture fixation (proximal/middle phalanx ORIF or K-wire), PIP joint and volar-plate / collateral-ligament procedures, and minor soft-tissue work. The program rests on three levers the patient handout puts into practice — (1) oedema control, (2) early gentle protected movement, and (3) tendon gliding / joint-blocking to preserve differential excursion. It explicitly defers to the operation-specific protocol whenever the surgery carries a defined protected arc, motion limit or splinting regime (most importantly flexor or extensor tendon repair), which this general program does not attempt to reproduce.
Defining principle: fingers stiffen faster than almost any other joint complex in the body. The small interphalangeal joints, the gliding flexor/extensor tendons within their sheaths, and the dense soft-tissue envelope are all exquisitely sensitive to swelling and immobility — adhesions and joint contracture establish within days, not weeks. Rehabilitation is therefore a constant balancing act: protect the repaired structure for exactly the window it needs, and not one day longer, while restoring controlled glide and range early to outrun the stiffness. When in doubt, the default after finger surgery is controlled motion, not rest.
A. WHY EARLY CONTROLLED MOTION (THE CORE RATIONALE)
The unifying problem after any finger operation is the stiff finger: persistent oedema and immobility drive scar between the gliding planes, contract the joint capsule and collateral ligaments, and convert a mechanically sound repair into a functionally poor hand. The hand-surgery literature treats the stiff finger as a largely preventable complication of inadequate early rehabilitation rather than an inevitable consequence of surgery [The Stiff Finger; Stiff Digit, JAAOS].
- Immobilisation has a cost. Reduced range of motion after immobilisation arises from increased swelling, scarring between tendons and surrounding structures, and joint/ligament contracture — the exact mechanisms early motion is designed to defeat (BSSH early-mobilisation guidance).
- Adhesions establish early. The rationale for getting the patient moving — ideally with instructions given pre-operatively — and for a first therapy review at 5–7 days is to begin glide before adhesions become established (BSSH). The synthesis mirrors this: the home program starts as soon as the wound and operation allow, not at an arbitrary late milestone.
- Time to active exercise predicts the end result. In hand-fracture rehabilitation, earlier commencement of active exercise predicts greater total active range of motion at 6 weeks — a direct, measurable dose-response between early motion and outcome [Time to commencement of active exercise predicts TAM, Hand Therapy 2016].
B. EVIDENCE BY PROCEDURE GROUP
Finger fracture fixation (phalangeal ORIF / K-wire)
- The modern standard is stable fixation that permits early protected motion. Wide-awake surgery with early protected movement and pain-guided progression yields better finger ROM than rigid immobilisation (Saint John / pain-guided protocols; "better results with wide-awake surgery and early protected motion"). A systematic review and meta-analysis of mobilisation after ORIF of hand fractures supports earlier mobilisation over prolonged immobilisation for range without compromising union (ScienceDirect 2025 SR).
- Stable construct is the prerequisite. The whole early-motion strategy is contingent on the surgeon's judgement that the fixation will tolerate movement — which is why the synthesis hands the precaution set (load limits, the up-to-6-week no-lift window) back to the post-operative review. Surgeon to confirm per case.
- Minimally invasive fixation techniques are explicitly framed around preserving the soft-tissue envelope to reduce stiffness and allow early motion [Minimally Invasive Finger Fracture Management, Hand Clin].
PIP joint, volar-plate and collateral-ligament injuries
- These are stiffness-prone injuries where the management trade-off (stability vs early motion) is sharpest. The literature on PIP dislocations, fracture-dislocations and volar-plate injuries consistently favours early protected/active motion, often with buddy-strapping or a dorsal blocking approach, over static immobilisation, precisely because the PIP joint contracts so readily [PIP dislocations in athletes, Hand Clin; PIP fracture-dislocations, JBJS Rev; finger joint dislocations, Clin Sports Med].
- Buddy taping — depicted in the handout's hero image — is the canonical low-tech "protected early movement" tool here: it shares load with the neighbouring digit while permitting active glide.
Trigger finger (A1 pulley) release
- Release of the A1 pulley is a high-yield day procedure with reliably good patient-perceived recovery [Patient-Perceived Outcomes of Recovery After Trigger Digit Release, JHS 2023].
- Formal supervised therapy is usually NOT required for an uncomplicated release. A prospective randomised controlled trial found no significant difference in DASH, grip strength, ROM or pain between a structured post-operative occupational-therapy arm and a simple home-advice/ROM arm at final follow-up (RCT, PMC10671987). This validates the synthesis framing this as a home program with therapy escalation reserved for those who are slow to settle, stiff or swollen — not mandated for everyone.
Dupuytren's fasciectomy
- Therapy after fasciectomy centres on oedema and wound management, a home exercise program, and night extension splinting — a typical "brief" protocol runs 4 sessions (days 0-3, 2 wk, 4 wk, 8 wk) with a night extension orthosis to ~3 months (post-fasciectomy rehab trials).
- Routine night-splinting for all is contested. The SCoRD-type trials and subsequent work show static night splinting does not clearly improve ROM over hand therapy alone for unselected patients — splinting is best targeted at those losing extension, not applied universally [SCoRD protocol; Dutch Multidisciplinary Guideline on Dupuytren Disease].
- For established post-fasciectomy or post-fracture flexion stiffness, casting motion to mobilise stiffness (CMMS) is an evidence-supported salvage technique to regain digital flexion [Casting motion to mobilise stiffness, Hand Therapy 2010].
C. OEDEMA, SCAR AND STIFFNESS MANAGEMENT
- Oedema control is first-line and non-negotiable. Persistent hand oedema stiffens the soft tissues and degrades both ROM and function. The best systematic review of subacute hand oedema management concluded that active exercise enabling tendon gliding and muscular contraction acts as a pump to drive oedema away from the periphery, and supports elevation and active movement as first-line, with retrograde massage, compression and manual oedema mobilisation as adjuncts — there is no single superior modality, so the program layers them [Miller, Jerosch-Herold & Shepstone, J Hand Ther 2017]. This is reference [1] in the synthesis.
- Tendon gliding works through differential excursion. The straight / hook / tabletop / full-fist positions are not interchangeable repetitions: each moves the FDP relative to the FDS and relative to the sheath by a different amount, and it is this differential glide that keeps the tendons from scarring to one another and to the sheath [Wehbe & Hunter, J Hand Surg Am 1985 — reference [2] in the synthesis]. Joint-by-joint DIP and PIP blocking isolates the same glide at a single joint.
- Scar management. Once the wound is healed, scar massage and desensitisation reduce adherent scar over the incision — relevant to every open finger procedure and the surgical interval through which the tendons must glide.
- Heat before, ice after the exercise session is a standard hand-therapy adjunct to improve tissue extensibility for movement and settle the post-exercise inflammatory flare (consensus practice).
Phased timeline (maps to the synthesis sections)
| Phase | Window | Protect | Motion / glide | Oedema & scar | Notes |
|---|---|---|---|---|---|
| I — Settle & protect | Week 0-~2 | Protect per the specific operation (buddy tape / splint / load limits as set at review); light functional use for self-care, dressing, writing, typing | Begin gentle active motion within the operation's limits; tendon glides and DIP/PIP blocking as the wound and fixation allow | Elevation + active movement first-line for swelling; wound care per handout | First therapy review ideally 5-7 days to start glide before adhesions set (BSSH). No lifting/gripping/impact |
| II — Restore glide & range | Week ~2-6 | Wean protection as the structure consolidates; precautions confirmed at post-op review | Progress active ROM, full tendon-glide series, joint blocking; buddy strapping for PIP/collateral injuries | Once healed: commence scar massage (firm circles); heat before / ice after exercises; retrograde massage + compression if oedema persists | Most ROM is won in this window — frequent gentle practice beats occasional hard effort |
| III — Strengthen & return | Week ~6-12 | Protection generally off (operation-dependent) | Restore full ROM; introduce grip and functional strengthening | Continue scar work until mature; night extension splint to ~3 mo if losing extension (Dupuytren) | Return to lifting/gripping/impact from ~6 weeks per the operation; escalate persistent stiffness to hand therapy / CMMS |
Phase windows are typical and consensus-based; the operation-specific protocol and the surgeon's post-operative review override any timing here.
D. KEY CONTROVERSIES / EVIDENCE QUALITY
- Universal supervised therapy vs home program. For simple procedures (trigger finger release) an RCT shows no benefit of routine formal therapy over good home advice — supporting a targeted therapy model. For complex/stiffness-prone injuries (PIP, fracture-dislocation, fracture ORIF) early supervised hand therapy is far more clearly beneficial. The synthesis correctly pitches a home program with therapist escalation rather than mandating identical input for every operation. Moderate.
- Night-splinting after Dupuytren's fasciectomy. Routine static night splinting is not supported for unselected patients (SCoRD, Dutch guideline); reserve it for those demonstrably losing extension. Moderate (RCT/guideline).
- How early, and how much, to move a fixed fracture. Early protected motion is favoured, but it is strictly contingent on a stable construct — a judgement only the operating surgeon can make. The "early motion is better" evidence assumes adequate fixation. Moderate (SR), construct-dependent.
- The general protocol itself is a consensus scaffold. A single "finger surgery" rehab program necessarily generalises across heterogeneous operations; its three principles (oedema, early motion, glide) are very well supported, but the exact dosing/timing is expert-consensus, individualised by the treating therapist and surgeon.
E. EVIDENCE STRENGTH FLAGS (summary)
- STRONG: oedema control via elevation + active tendon-gliding exercise as first-line (SR, J Hand Ther 2017); tendon differential-excursion rationale for the varied glide positions (mechanistic, Wehbe & Hunter); early motion reduces stiffness/adhesions after finger surgery (consistent across the stiff-finger and BSSH literature).
- MODERATE (RCT / SR / guideline): early mobilisation > immobilisation after hand-fracture ORIF (SR + meta-analysis, 2025); time-to-active-exercise predicts 6-week TAM; no added benefit of routine formal therapy after simple trigger-finger release (RCT); selective (not universal) night splinting after Dupuytren's fasciectomy (SCoRD/Dutch guideline).
- WEAK / CONSENSUS: the precise phase windows and exercise dosing in this general program (expert hand-therapy consensus, individualised); heat-before/ice-after adjunct; the principle that operation-specific protocols override this general scaffold (sound clinical practice, not trial-derived).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Time to commencement of active exercise predicts total active range of motion 6 weeks after hand-fracture fixation. Hand Therapy. 2016. DOI: 10.1177/1758998316679386
- Hardy MA. The Stiff Finger. Hand Clinics. 2010. DOI: 10.1016/j.hcl.2010.02.001
- Etiology, Evaluation, and Management Options for the Stiff Digit. JAAOS. DOI: 10.5435/jaaos-d-18-00310
- Phalangeal neck fractures of the proximal phalanx of the fingers in adults. Injury. 2010. DOI: 10.1016/j.injury.2010.06.017
- Minimally Invasive Finger Fracture Management. Hand Clinics. 2013. DOI: 10.1016/j.hcl.2013.08.014
- Management of Proximal Interphalangeal Joint Dislocations in Athletes. Hand Clinics. 2009. DOI: 10.1016/j.hcl.2009.05.008
- Treatment of Proximal Interphalangeal Joint Fracture-Dislocations. JBJS Reviews. DOI: 10.2106/jbjs.rvw.o.00019
- Management of Finger Joint Dislocation and Fracture-Dislocations in Athletes. Clinics in Sports Medicine. 2019. DOI: 10.1016/j.csm.2019.10.006
- Patient-Perceived Outcomes of Recovery After Trigger Digit Release. J Hand Surg Am. 2023. DOI: 10.1016/j.jhsa.2023.03.016
- Comparative Study of A1 Pulley Release and Ulnar Superficialis Slip Resection (trigger digit). J Hand Surg Am. 2022. DOI: 10.1016/j.jhsa.2022.04.021
- Use of casting motion to mobilize stiffness (CMMS) to regain digital flexion. Hand Therapy. 2010. DOI: 10.1258/ht.2010.010008
- Dutch Multidisciplinary Guideline on Dupuytren Disease. J Hand Surg Glob Online. 2022. DOI: 10.1016/j.jhsg.2022.11.008
- Factors affecting functional recovery after surgery and hand therapy in Dupuytren's patients. J Hand Ther. 2014. DOI: 10.1016/j.jht.2014.11.006
- Rehabilitation Regimens Following Surgical Repair of Extensor Tendon Injuries of the hand. DOI: 10.1007/s12593-012-0075-x
Hand-therapy / rehabilitation literature (URLs)
- Miller LK, Jerosch-Herold C, Shepstone L. Effectiveness of edema management techniques for subacute hand edema: a systematic review. J Hand Ther. 2017;30(4):432-446. https://pubmed.ncbi.nlm.nih.gov/28807598/
- Wehbe MA, Hunter JM. Flexor tendon gliding in the hand. Part II. Differential gliding. J Hand Surg Am.
- https://pubmed.ncbi.nlm.nih.gov/4020073/
- Systematic review and meta-analysis of mobilisation following ORIF of hand fractures. ScienceDirect.
- https://www.sciencedirect.com/science/article/pii/S1748681525003109
- Better results of finger fractures with wide-awake surgery and early protected motion. PMC. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4445035/
- The effectiveness of rehabilitation after open surgical release for trigger finger: a prospective, randomized, controlled study. PMC. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10671987/
- Splinting after contracture release for Dupuytren's contracture (SCoRD): RCT protocol. PMC. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2386788/
Published rehab protocols (patient-guidance / society — basis for the phase structure)
- The British Society for Surgery of the Hand (BSSH) — Guidelines. https://www.bssh.ac.uk/professionals/guidelines.aspx
- Pain-Guided Hand Therapy for early protected movement of finger fractures (The Saint John Protocol), ASSH. https://handsurgery.org/multimedia/files/preCourse/Pain%20Guided%20Hand%20Therapy%20for%20early%20protected%20movement%20finger%20fractures.pdf
- Rehabilitative Strategies Following Hand Fractures. Hand Clinics. https://www.hand.theclinics.com/article/S0749-0712(13)00066-8/fulltext
- University of Kentucky HealthCare — Hand Rehabilitation Protocols. https://ukhealthcare.uky.edu/sites/default/files/m21-0609_ortho_protocols-final.pdf





