

肱骨外上髁炎(网球肘) 资料
本页面介绍网球肘的治疗方法及康复方案,无论您接受非手术治疗(绝大多数患者的情况)还是接受清创手术后的恢复。该页面由 Mater Private Hospital Rockhampton 的 Kieran Hirpara 医生负责监督。内容从您的家庭锻炼计划开始,随后是为您物理治疗师或手部治疗师编写的结构化临床方案;请在治疗就诊时携带本页面或其 PDF 文件,以确保您的康复过程协调一致。您的治疗师可能会根据恢复进展调整计划。
预期情况
网球肘(肱骨外上髁炎)是肘部外侧肌腱的问题,具体涉及伸肌总腱,尤其是一块称为桡侧腕短伸肌(ECRB)的小肌肉。尽管名称中含有“-itis”(炎),但它并非一种可以通过休息消除的炎症。它是肌腱的磨损性改变(肌腱病),其中肌腱纤维变得紊乱且未能正常愈合。
这一点至关重要,因为它完全改变了治疗方案。您不能通过休息和保护肘部来康复;事实上,长时间休息往往会使肌腱变得更弱,恢复速度更慢。您需要通过逐渐增加肌腱负荷,使其重塑并重建其对工作和抓握的耐受能力,从而获得康复。其模式为:首先缓解疼痛,然后逐步增强力量,从温和的等长(静力)练习开始,逐渐过渡到受控的、缓慢的力量训练,如泰勒扭转(Tyler twist)。
好消息是,在正确的负荷训练方案下,网球肘通常会自行缓解。大约80–90%的人在一年内好转,尽管偶尔可能需要12–18个月才能完全解决。只有在至少六个月的高质量、持续康复失败后,才会考虑手术,且只有极少数人(大约4–11%)会达到这一步。
注意事项与局限性
应当:
- 继续使用该手臂:对肌腱施加负荷,不要使其休息。
- 以疼痛为指引:运动期间及运动后出现轻微酸痛是正常的且符合预期的;若出现尖锐或逐渐加重的疼痛,则应减轻强度。
- 掌心向上进行提举(如同端着一碗汤),以减轻受损肌腱的负荷。
- 在抓握和提举任务期间,在前臂肌肉上使用反力支具。
不应当:
- 对于接受非手术治疗的网球肘,不要使用石膏或悬吊带固定肘部;对于肌腱病而言,这是错误的治疗方法。(术后情况则不同:第一周会使用悬吊带以提供舒适感,详见下文的术后路径。)
- 不要进行肘部伸直且手腕弯曲的重度诱发性抓握(例如,掌心向下提举重物)。
- 不要急于进行皮质类固醇注射。虽然可的松(皮质类固醇)在几周内可能让人感觉良好,但证据表明,与物理治疗或单纯等待相比,它在 6–12 个月时会导致更差的结果和更多的复发。它不是一线治疗方案。
您的锻炼
Kieran Hirpara 4.0
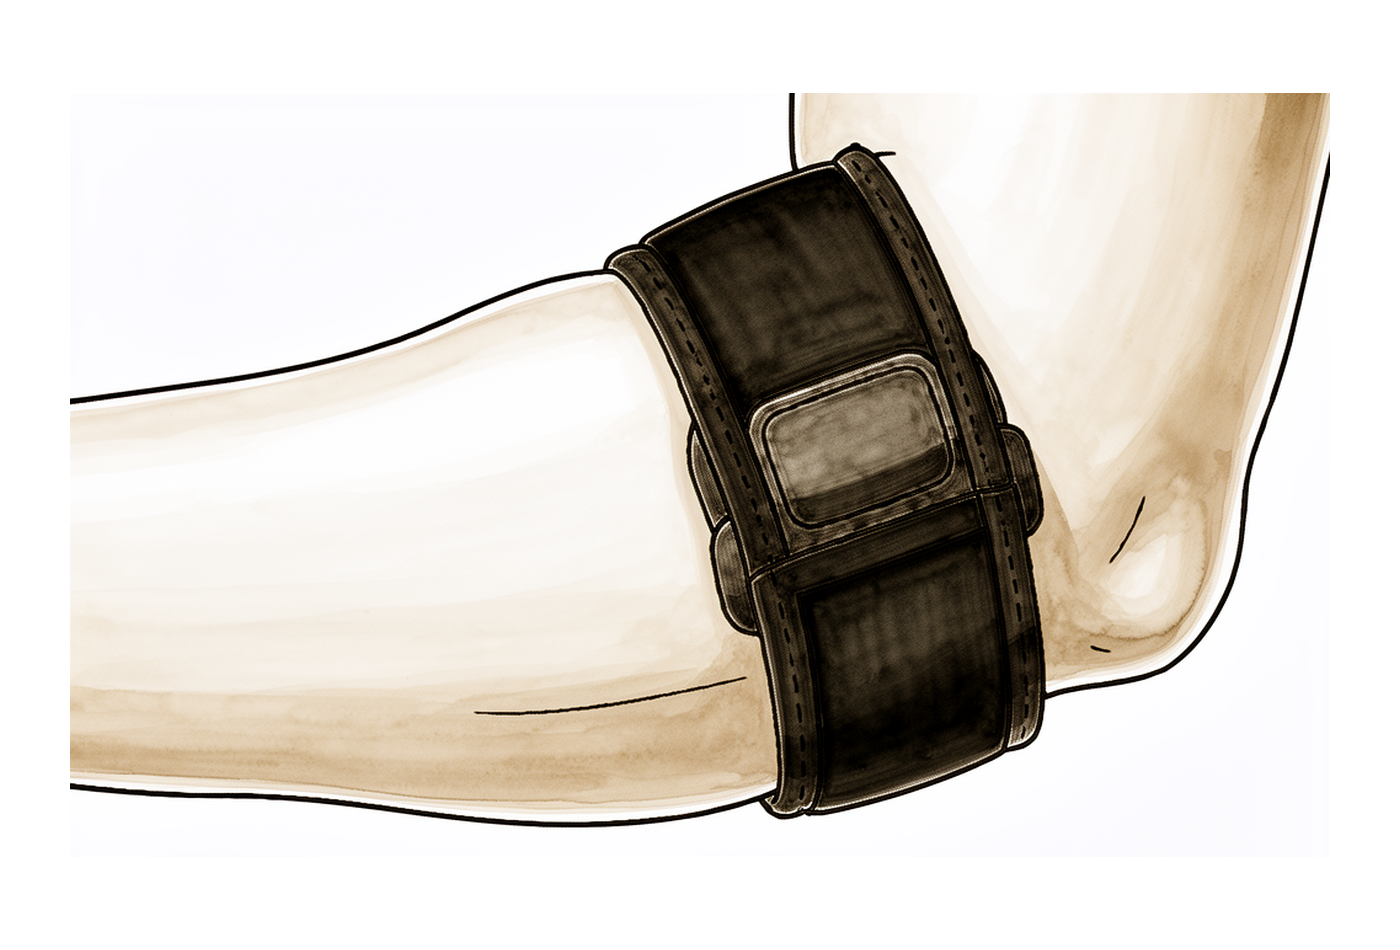
反力支具
将反力支具佩戴于前臂,位置在肘部下方约两指宽处,覆盖肌肉丰厚区域(而非骨性突起本身)。佩戴时应保持稳固,但不可过紧以致引起手部刺痛感。在进行抓握和提举动作时使用该带,以减轻受损肌腱的负荷;在静息状态或卧床时无需佩戴。
在加重症状的活动期间佩戴;若手部出现刺痛感,请松开
Kieran Hirpara 4.0
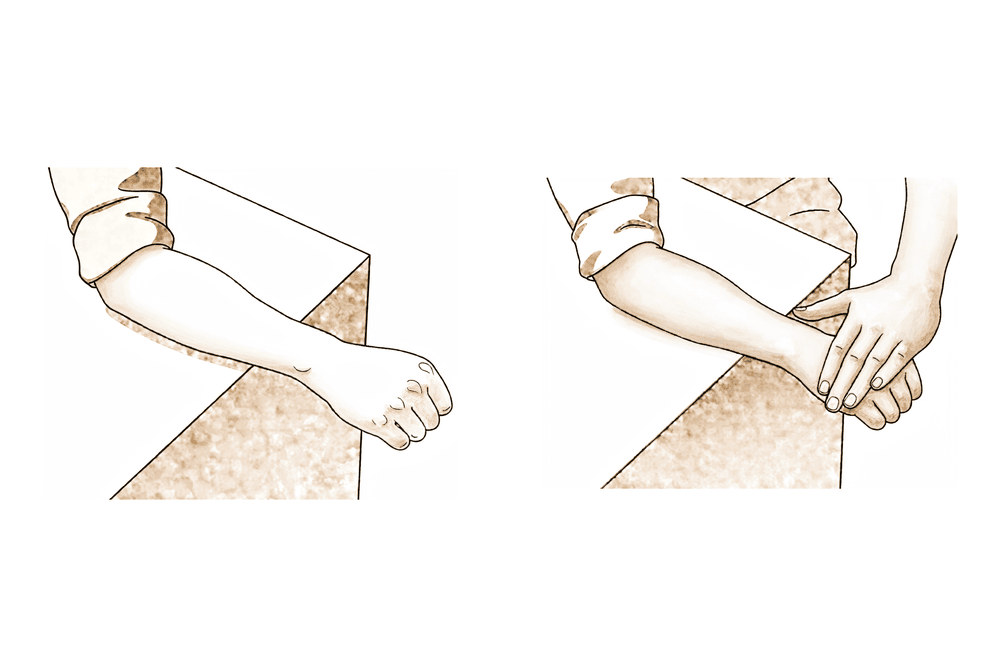
腕关节等长伸
将前臂放在桌面上,掌心向下,手悬于桌边。将另一只手放在疼痛手的背侧。尝试将手背向天花板方向抬起,同时用另一只手将其固定,使手部实际不发生移动——这是一种等长抗阻练习。应感觉用力但不应产生剧烈疼痛。保持推压姿势,然后放松。
保持 30–45 秒,5 次,每日 1–2 次
Kieran Hirpara 4.0
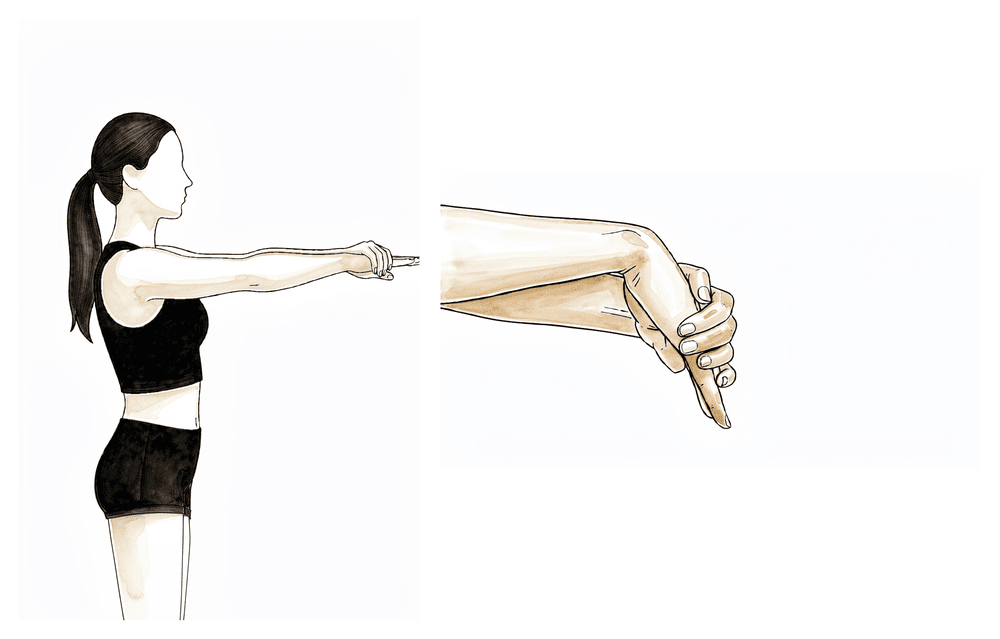
腕部伸肌拉伸
将疼痛的手臂向前伸直,肘部保持伸直,掌心朝下。用另一只手轻轻向下弯曲手腕,使手指指向地面,直到您感到前臂上侧有舒适的牵拉感。保持肘部伸直。如果完全伸直肘部时疼痛过于剧烈,可先从肘部略微弯曲开始,随着疼痛缓解逐渐过渡到肘部完全伸直。
保持30秒,3次,2–3 次/天
Kieran Hirpara 4.0
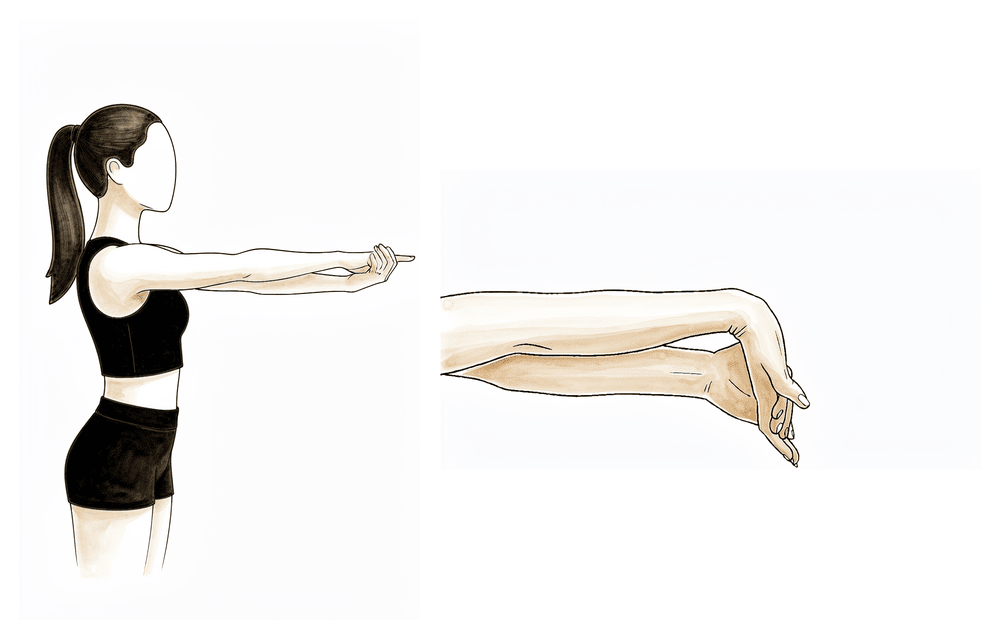
腕部屈肌拉伸
将手臂向前伸直,肘关节保持伸直,掌心向上。用另一只手轻轻将手指和手腕向后下方牵拉,直到感到前臂下方有舒适的牵拉感。保持肘关节伸直。
保持30秒,3次,2–3 次/日
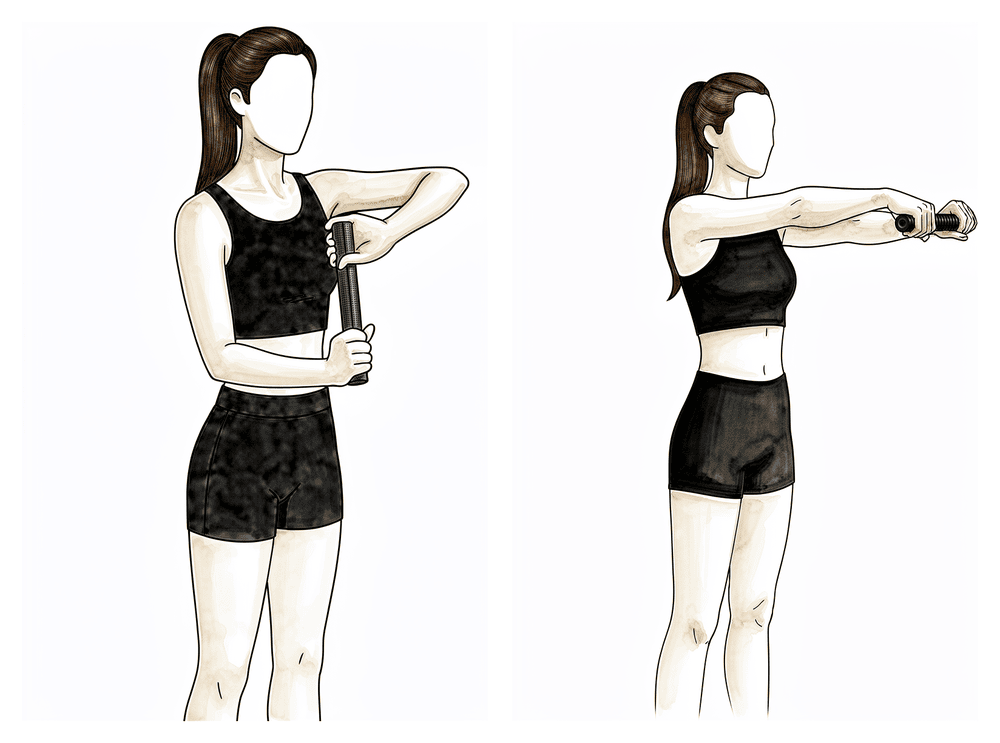
Kieran Hirpara 4.0
泰勒扭转(离心性腕背伸)
用患手握持一根柔性橡胶棒(FlexBar),使其保持垂直,手腕处于背伸位。用另一只手握持棒的顶端并施加扭转。随后将棒移至身体前方,保持扭转状态,并在3–4秒内缓慢、有控制地让患侧手腕屈曲——这种缓慢、有控制的降低动作是强化肌腱的关键部分。释放扭转的过程应感觉费力,但不应出现锐痛。动作过程中及之后出现轻微酸痛属预期现象,且无碍。
3组,每组15次,每日一次(核心强化练习)

Kieran Hirpara 4.0
前臂旋转
将肘部贴紧身体侧面,并将其弯曲至直角。缓慢旋转前臂,使掌心朝上,然后翻转使掌心朝下,同时保持肘部贴紧身体。随着动作变得更容易,可手持较轻的重物(如锤子或罐头)以增加负荷。
每个方向10次,每日2–3次;视能力增加轻重量

Kieran Hirpara 4.0
握力强化
在手中挤压一个软球或治疗用橡皮泥,短暂保持挤压状态,然后放松。随着肌腱耐受度的提高,逐渐增加挤压的力度。如果抓握仍然非常疼痛,请从较晚的时间点和较轻的力度开始——抓握训练属于强化阶段,应在早期刺激消退后进行。
挤压 10–15 次,每日 2–3 次;根据耐受情况逐渐增加硬度
这些是您的手册中的锻炼项目。它们按照康复顺序进行:反力支具和等长保持有助于早期缓解疼痛,拉伸动作保持前臂柔韧,而泰勒扭转、前臂旋转和抓握训练则有助于重建肌腱。请按照Hirpara医生和治疗师的指导开始锻炼,您不必从第一天起就完成所有项目;您的治疗师会告诉您应从哪些项目开始,以及何时加入强化训练。
您的临床方案
本页其余部分为肱骨外上髁炎(网球肘)的临床康复方案。本节内容应提供给您的物理治疗师或手部治疗师,每个阶段均以通俗易懂的语言解释当前正在发生的情况。
该方案包含两条路径:一条是非手术路径(适用于几乎所有患者的首选方案),另一条是术后路径(适用于少数在经历至少六个月高质量保守治疗无效后接受桡侧腕短伸肌(ECRB)清创术的患者)。
非手术路径
核心原则是渐进性肌腱负荷,以疼痛为指导。目标是缩短症状持续时间并恢复负荷耐受性,而非让肌腱休息。
第一阶段 — 急性期 / 疼痛控制(0–2 周)
此处的重点在于缓解疼痛并恢复无负重活动。无需固定;这是相对休息,而非石膏固定。
致您的物理治疗师:
- 目标: 缓解疼痛;恢复完整的无负重主动活动范围(AROM)。
- 管理: 活动调整、关节保护及人体工学建议。可选在伸肌总腱上佩戴反力支具,以在抓握时减轻桡侧腕短伸肌(ECRB)起点的负荷;若伸展活动时急性疼痛明显,可使用腕部(背伸位)夹板。缓解疼痛的辅助手段包括:冰敷、软组织/器械辅助软组织松动术(IASTM)、轻柔的无痛主动活动范围(AROM)练习、可选干针疗法、神经滑动练习。
- 晋级标准: 无负重主动活动范围(AROM)完整且无痛;能独立执行家庭锻炼计划。
第二阶段 — 亚急性期 / 早期负荷期(2–4 周)
肌腱负荷训练应轻柔开始,并针对近端链(肩胛骨和肩袖)进行处理,因为上臂近端的肌力不足会导致肘部过度负荷。
致您的物理治疗师:
- 目标: 开始肌腱负荷训练;处理近端动力链。
- 练习: 等长腕伸肌和屈肌负荷训练(轻负荷;在反应性肌腱病中,等长运动耐受性良好且具有镇痛作用);肘关节屈曲 90° 时,对腕屈肌和伸肌进行渐进性拉伸;近端训练:前锯肌、中/下斜方肌、肩袖及肩胛骨稳定肌群。
- 晋级标准: 维持全范围关节活动度;耐受肘关节屈曲 90° 时的拉伸;达到对侧握力/肌力的约 70%。
第三阶段 — 强化/恢复期(4–6 周及以后,通常持续至 12 周)
此阶段旨在重建肌腱并恢复工作与运动所需的负荷耐受能力。离心-向心负荷是核心治疗驱动因素。
致您的物理治疗师:
- 目标: 恢复负荷耐受能力及运动/工作能力。
- 练习: 手腕伸展及前臂旋前/旋后的离心-向心负荷训练;泰勒扭转(FlexBar)是典型的家庭离心训练工具。将拉伸动作逐步进展至肘关节伸直位;结合运动进行松动术(Mulligan技术)。握力强化及任务/运动特异性负荷训练;运动员进行增强式训练。随着患者症状消失,逐渐撤除反力支具。为运动员调整装备(握把尺寸、弦张力、技术动作)。
- 进阶标准(重返运动): 约为对侧力量的90%,无痛功能活动,以及具备自我管理胜任力。
术后路径(ECRB清创 ± 松解)
手术仅保留给约4–11%在≥6个月的高质量保守治疗失败的患者。开放式Nirschl型清创和关节镜下ECRB清创效果相当。以下时间线遵循Brigham & Women's医院关于外上髁清创的标准护理方案。
第一阶段 — 保护(第 1–7 天)
吊带仅在第一周用于提供舒适感。
致您的物理治疗师:
- 吊带用于舒适;冰敷 20 分钟,每日 2–3 次;在切口处覆盖肘部护垫。
- 轻柔的无痛手部、腕部和肘部主动活动范围(AROM);肩部主动活动范围(ROM);肩胛周围肌肉练习。
- 尽量减少对伸肌机制产生压力的日常活动(ADLs)(如提重物、肘关节完全伸直同时伴腕关节屈曲);掌心向上提起以减轻伸肌负荷;若急性疼痛,可选用腕部支具。
第二阶段 — 早期活动(第 2–4 周)
致您的物理治疗师:
- 停止使用悬吊带。 在疼痛耐受范围内开始被动活动(PROM)和主动辅助活动。
- 温和强化训练:主动活动及次最大等长收缩。开始瘢痕管理。
第3阶段 — 强化训练(第5–7周)
致您的物理治疗师:
- 进阶抗阻强化训练(负重 / 治疗带),重点强调腕伸肌群的耐力(轻负荷,高次数)。恢复完全主动和被动活动范围。
- 引入针对伸肌总腱的反力支具(并教育患者避免神经受压);进行轻柔的交叉纤维按摩;开始功能性准备。
第4阶段 — 功能/恢复期(第8–12周)
致您的物理治疗师:
- 任务特异性功能训练;恢复较高水平的工作和休闲活动。
- 根据需要继续佩戴反力支具,以实现无痛的日常活动(ADLs)和肌力强化。
重返工作与活动
如果您正在接受非手术方式治疗网球肘,则没有固定的“停工”期限;在整个康复过程中,您可以继续使用该手臂,通过调整最费力的抓握和提举任务,并使用反力支具来应对这些任务。现实的预期是肘部将在 6–12 个月内逐渐稳定,大多数人(80–90%)会在一年内好转。这是一个缓慢的肌腱问题,因此进展是以周和月为单位衡量的,而不是以天为单位。坚持负荷训练计划是达到目标的关键;在此过程中出现的症状反复是正常的,只要轻微的酸痛在第二天就能缓解,这就不算倒退。
如果您已经接受了手术,吊带仅在第一周用于提供舒适感,随着肘部稳定即可弃用。力量在 5–7 周内逐步建立,大多数人会在 8–12 周左右实现工作和休闲活动的功能性恢复。在此期间,较重及运动专项的需求将根据肌腱对负荷的耐受情况逐步重新引入。
重返运动(适用于两种治疗路径)的指导标准是达到另一侧手臂力量的大约 90%,并具备无痛的功能表现及自我管理的信心,而不仅仅依据日历时间。
方案结束后
本方案与本诊所的一般康复建议配合使用;请参阅术后疼痛管理,以及如果您接受过手术,请查阅伤口护理和手部治疗基础。上述分阶段计划反映了针对网球肘(渐进性肌腱负荷而非休息)的最新最佳证据,您的持续康复将由您的物理治疗师或手部治疗师根据您肘部的恢复进展进行个别指导。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: (A) the natural history and stepped non-operative management of lateral epicondylitis (relative rest → progressive tendon loading: isometric → eccentric–concentric; counterforce bracing; controversies around corticosteroid and PRP injection), and (B) post-operative rehabilitation after open or arthroscopic ECRB debridement ± release, reserved for the minority who fail ≥6 months of quality conservative care.
Defining principle: despite the "-itis" suffix, lateral epicondylitis is a degenerative tendinopathy (tendinosis) of the extensor carpi radialis brevis (ECRB) origin, not an inflammatory condition. This reframes treatment away from rest and anti-inflammatory measures and toward progressive tendon loading — settle pain with isometrics, then rebuild load tolerance with eccentric–concentric loading (the Tyler twist / FlexBar). KH's stance: load the tendon, do not immobilise it; corticosteroid injection is avoided as first line because it is better short-term but worse at 6–12 months; surgery is a last resort after ≥6 months of genuine conservative care.
A. NATURAL HISTORY & NON-OPERATIVE MANAGEMENT
Natural history (self-limiting in most)
Lateral epicondylitis is self-limiting in the majority: roughly 80–90% resolve within about one year regardless of treatment, with the conservative literature ranging out to 12–18 months [Coonrad & Hooper 1973; Nirschl 1999]. This high spontaneous-resolution rate is the central methodological challenge of the field — any intervention must beat natural history, a high bar most fail to clear. The goal of therapy is therefore to shorten the symptomatic course and restore load tolerance, not to "cure" a condition that largely settles on its own.
Phased non-operative rehabilitation
First-line for essentially all comers. The therapeutic core is progressive tendon loading guided by pain.
Phase I — Acute / pain control (~0–2 weeks). Relative rest, NOT immobilisation — avoid full wrist/elbow casting (Nirschl). Activity modification, joint protection, ergonomics. Optional counterforce brace over the common extensor mass (offloads the ECRB origin during grip) ± a wrist cock-up splint if acutely painful. Adjuncts: ice, soft-tissue/IASTM, pain-free AROM, optional dry needling, nerve glides. Criterion to progress: full unloaded AROM without pain; independent with home program. Consensus / institutional protocol.
Phase II — Sub-acute / early loading (~2–4 weeks). Begin isometric wrist flexor/extensor loading (minimal load; isometrics are well tolerated and analgesic in reactive tendinopathy). Progressive stretching of wrist flexors/extensors with the elbow at 90°. Add proximal kinetic-chain work (serratus anterior, mid/lower trapezius, rotator cuff, scapular stabilisers — proximal deficits drive distal overload). Criteria to progress: full ROM maintained; tolerates stretch at 90° elbow flexion; ~70% contralateral grip/strength. Moderate (strengthening trials) / Consensus (timeline).
Phase III — Late / strengthening & return (~4–6+ weeks, often to 12 weeks). Eccentric–concentric loading of wrist extension and forearm pronation/supination is the core driver; the Tyler twist (FlexBar eccentric wrist-extension) is the prototypical home tool. Progress stretching to the elbow-extended position; add mobilisation-with-movement (Mulligan). Grip strengthening and task-/sport-specific loading; plyometrics for athletes. Gradually wean the counterforce brace as the patient becomes asymptomatic. Return-to-sport criteria: ~90% contralateral strength, pain-free function, self-management competence. Moderate–High (RCT/SR for exercise & loading) / Consensus (phase timings).
B. POST-OPERATIVE REHABILITATION (open or arthroscopic ECRB debridement ± release/repair)
Surgery is reserved for the ~4–11% who fail ≥6 months (commonly 6–12 months) of quality conservative care. Open Nirschl-type debridement and arthroscopic ECRB debridement give comparable complication and reoperation rates (national database, Arthroscopy 2022); arthroscopy additionally allows intra-articular inspection. The phased timeline below is the Brigham & Women's Standard of Care for lateral epicondyle debridement, cross-checked against community ECRB-release protocols.
| Phase | Window | Sling / support | Motion & strengthening | Notes |
|---|---|---|---|---|
| 1 — Protect | Days 1–7 | Sling for comfort; optional wrist splint if painful | Pain-free hand/wrist/elbow AROM; active shoulder ROM; periscapular work | Ice 20 min 2–3×/day; elbow pad over incision; lift palm-up to offload extensors |
| 2 — Early motion | Weeks 2–4 | Discontinue sling | PROM + active-assisted motion within pain tolerance; sub-maximal isometrics | Begin scar management |
| 3 — Strengthening | Weeks 5–7 | Introduce counterforce brace | Advance resistive strengthening (weights/Theraband); wrist-extensor endurance (light load, high rep); restore full A/PROM | Education to avoid nerve compression; cross-fibre massage |
| 4 — Functional / return | Weeks 8–12 | Counterforce brace as needed | Task-specific functional training; return to work/recreation | Functional return wk 8–12 |
Alternative published timelines (community ECRB-release protocols): wrist splint full-time 0–2 wk with no strengthening; full ROM goal by 4–6 wk; strengthening + transition to counterforce brace
6 wk; full activity ~8–10+ wk. Note: one comparative series found post-op bracing/immobilisation delayed symptom resolution versus PRP (mean time to full ROM 96 days surgery vs 42 days PRP) — reinforcing that early controlled motion, not protection, is the goal.
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Corticosteroid injection: better short-term, WORSE long-term. The Bisset/Smidt body of work (and the BMJ 2006 mobilisation-with-movement RCT) shows steroid gives early relief but higher recurrence and worse 6–12-month outcomes than physiotherapy or wait-and-see. Some authors now call it "always inadvisable" for lateral elbow (Orthop Trauma Surg Res 2019). Prior injection is associated with eventual surgery (a proxy for severity). Strong (Level-1 RCT).
- PRP / autologous blood: contested. Some Level-1 RCTs (Peerbooms 2010; Gosens 2-yr) show PRP superior to corticosteroid with ongoing 2-year benefit; others (Krogh 2013) found PRP ≈ glucocorticoid ≈ saline (no benefit over placebo). Meta-analyses are heterogeneous. Net: a reasonable second-line for refractory cases, but evidence is inconsistent. Conflicting (Level-1).
- Eccentric vs concentric vs isometric. Pure eccentric (Alfredson-style) is effective but not clearly superior; current view favours eccentric–concentric combined loading, with isometrics for early analgesia. Grip/isometric demands of the elbow differ from the Achilles, so blanket extrapolation of eccentric-only protocols is questioned. Moderate.
- Surgical indication/timing & technique. Reserve for failure of ≥6 months conservative care. Open vs arthroscopic debridement: no significant difference in complication or reoperation rates (national database, Arthroscopy 2022); choice is surgeon-/training-dependent. Repair after debridement vs debridement alone remains unsettled. Surgical incidence is declining, attributed to eccentric-exercise protocols and injections. Moderate.
- Self-limiting nature complicates all evidence: ~80–90% resolve within a year regardless of treatment, so any intervention must beat natural history. Strong (natural-history signal).
D. EVIDENCE STRENGTH FLAGS (summary)
- MODERATE–HIGH (RCT / SR): progressive loading (eccentric / eccentric–concentric) and exercise therapy for non-operative lateral epicondylitis; mobilisation-with-movement (BMJ 2006); the natural-history signal (~80–90% resolve within ~1 year).
- MODERATE (cohorts / database): post-operative ECRB debridement outcomes; equivalence of open vs arthroscopic debridement (no difference in complication/reoperation rates).
- CONSENSUS / institutional (Level-5): the phase timelines themselves derive from Standard-of-Care protocols (Brigham & Women's, Mass General Brigham, Campbell's/Nirschl) — broadly concordant across sources but not trial-derived.
- STRONG (against, Level-1): corticosteroid injection as first-line — better short-term, worse at 6–12 months.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Bisset L et al. Mobilisation with movement and exercise, corticosteroid injection, or wait and see for tennis elbow: randomised trial. BMJ. 2006. DOI: 10.1136/bmj.38961.584653.AE
- Krogh TP et al. Treatment of lateral epicondylitis with platelet-rich plasma, glucocorticoid, or saline: a randomized, double-blind, placebo-controlled trial. Am J Sports Med. 2013. DOI: 10.1177/0363546512472975
- Peerbooms JC et al. Positive effect of an autologous platelet concentrate in lateral epicondylitis in a double-blind randomized controlled trial. Am J Sports Med. 2010. DOI: 10.1177/0363546509355445
- Gosens T et al. Ongoing positive effect of platelet-rich plasma versus corticosteroid injection in lateral epicondylitis: a double-blind randomized controlled trial with 2-year follow-up. Am J Sports Med. 2011. DOI: 10.1177/0363546510397173
- Ortega-Castillo M, Medina-Porqueres I. Effectiveness of the eccentric exercise therapy in physically active adults with symptomatic shoulder impingement or lateral epicondylar tendinopathy: a systematic review. J Sci Med Sport. 2016. DOI: 10.1016/j.jsams.2015.05.010
- Nirschl RP, Ashman ES. Elbow tendinopathy: tennis elbow. Clin Sports Med. 2003. (Current Concepts — Tendinosis of the Elbow, J Bone Joint Surg Am. 1999. DOI: 10.2106/00004623-199902000-00016)
- Coonrad RW, Hooper WR. Tennis elbow: its course, natural history, conservative and surgical management. J Bone Joint Surg Am. 1973. DOI: 10.2106/00004623-197355060-00002
- Lattermann C et al. Arthroscopic debridement of the extensor carpi radialis brevis for recalcitrant lateral epicondylitis. J Shoulder Elbow Surg. 2010. DOI: 10.1016/j.jse.2010.02.008
Lateral epicondylitis literature (URLs)
- Comparative efficacy and safety of nonsurgical treatment options for enthesopathy of the ECRB: a systematic review and meta-analysis of randomized trials. Am J Sports Med. 2018. https://pubmed.ncbi.nlm.nih.gov/29268037/
- Eccentric, eccentric–concentric, and eccentric–concentric + isometric training in lateral elbow tendinopathy. J Hand Ther. 2017. https://pubmed.ncbi.nlm.nih.gov/28732560/
- Role of strengthening during nonoperative treatment of lateral epicondyle tendinopathy. J Hand Ther. 2021. https://pubmed.ncbi.nlm.nih.gov/33041157/
- Chronic lateral elbow tendinopathy managed with a supervised graded exercise protocol. J Hand Ther. 2023. https://pubmed.ncbi.nlm.nih.gov/36127241/
- Management of lateral epicondylitis. Orthop Traumatol Surg Res. 2019. https://pubmed.ncbi.nlm.nih.gov/30414784/
- No difference in complication or reoperation rates between arthroscopic and open debridement for lateral epicondylitis: a national database study. Arthroscopy. 2022. https://pubmed.ncbi.nlm.nih.gov/34838651/
- Wang D et al. Trends in surgical practices for lateral epicondylitis among newly trained orthopaedic surgeons. Orthop J Sports Med. 2017. https://pubmed.ncbi.nlm.nih.gov/28840148/
- Factors associated with failure of nonoperative treatment in lateral epicondylitis. Am J Sports Med. 2015. https://pubmed.ncbi.nlm.nih.gov/26015443/
Published rehab protocols (patient-guidance — basis for the phase structure)
- Brigham & Women's Hospital — Post-Op Protocol for Lateral Epicondyle Debridement. https://www.brighamandwomens.org/assets/bwh/patients-and-families/rehabilitation-services/pdfs/elbow-lateral-epicondyle-debridement-postoperative-bwh.pdf
- Mass General Brigham Sports Medicine — Rehabilitation Protocol for Medial/Lateral Epicondylitis (non-operative), rev. April 2021. https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-medial-lateral-epicondylitis.pdf
- Beacon Orthopaedics — Lateral Epicondylitis ECRB Surgical Release Protocol. https://www.beaconortho.com/wp-content/uploads/Lateral-Epicondylitis-Release.pdf





