

掌指关节置换术 资料
本方案指导您在 Mater Private Hospital Rockhampton 接受 Kieran Hirpara 医生进行硅胶(Swanson)指关节(即掌指关节或“MCP”关节)置换术后的康复过程。内容首先介绍您的居家锻炼计划,随后是专为您的手部治疗师撰写的结构化临床方案:请在首次治疗就诊时携带此页面或其 PDF 文件,以确保您的康复过程协调一致。您的手部治疗师可能会根据您的康复进展调整计划。
这是一种以手部治疗为核心、依赖支具的康复过程。动态支具和每日锻炼并非可选附加项:它们是使新关节塑形为矫正后伸直位置的关键。您的治疗效果在很大程度上取决于是否忠实地执行支具佩戴和运动。
如果您对术后伤口有任何疑虑,请联系诊所。通常,拍摄伤口照片并通过电子邮件发送以供审阅会很有帮助。
预期情况
指间关节(指关节)可能出现磨损、疼痛和严重畸形,最常见于类风湿性关节炎,此时手指向小指侧偏斜(尺侧偏斜),且手指基部向掌侧滑脱(掌侧半脱位);骨关节炎也可能导致关节磨损。在此手术中,磨损的指间关节将被切除,并用柔性硅胶间隔物(经典的Swanson假体)进行置换。手术目标是缓解疼痛,纠正偏斜和下垂的指关节(伸肌滞后),并恢复有用的屈曲活动范围。
该假体并非刚性铰链。它作为柔性间隔物发挥作用,同时在其周围形成新的衬里(“关节囊”),这一过程通常在最初几周内完成。康复的核心在于确保关节囊在手指保持伸直和纠正(而非偏斜)的状态下形成。因此,夹板固定和早期活动至关重要。
因此,康复过程围绕动态伸肌外展夹板构建,通常在术后最初几天内佩戴:
- 休息时,夹板将指关节保持伸直,并轻轻向拇指侧牵拉(桡偏),直接对抗原有的尺侧偏斜。
- 在夹板内,您需对指关节进行早期受控的主动屈曲运动,对抗柔软的弹性环,弹性环会将手指弹回伸直位置。早期活动(但仅限于此受保护且已纠正的位置)能正确塑造新的关节囊,并防止关节僵硬。
您需几乎连续佩戴动态夹板约六周,随后过渡至休息/夜间夹板,并在后期加入分级强化训练。手部轻功能在最初几周内恢复;大多数人约三个月后可恢复大部分日常活动,最终效果将在随后的数月内继续稳定。
注意事项与限制
- 按指示佩戴您的动态伸展夹板: 在最初约六周内,需昼夜佩戴。夹板用于维持矫正效果;若过早或频繁取下,手指偏斜(drift)可能会复发。
- 切勿让手指向小指侧偏斜。所有练习均旨在引导手指向另一侧,即拇指方向移动。
- 早期切勿进行强力抓握、捏取或提重物:强力抓握会将手指推向尺侧偏斜(ulnar drift),并在新关节尚未稳定时对其造成应力。强化训练需等待您的手部治疗师评估许可后方可进行。
- 从一开始就保持拇指、手腕和指尖的活动,并在舒适范围内使用手部进行轻微的日常生活任务。
- 密切观察伤口是否有感染迹象(红肿加剧、发热、肿胀或渗出物),如有疑虑请联系病房;植入物周围的感染虽不常见,但早期发现至关重要。
关于伤口、肿胀及疤痕管理,请参阅本诊所的 伤口护理 指南。
您的锻炼
Kieran Hirpara 4.0
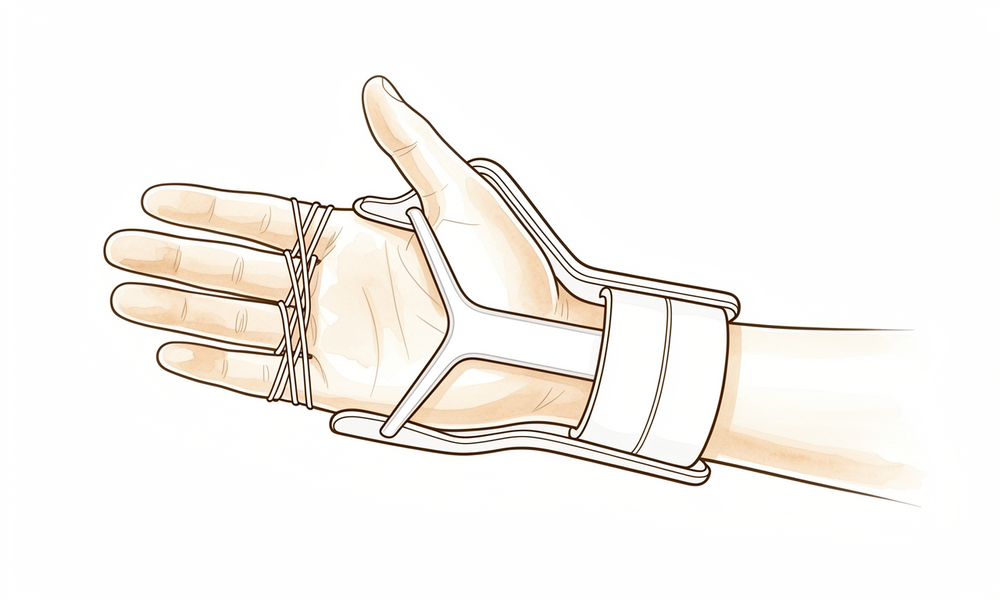
佩戴您的动态支具
您的动态伸指夹板为您起到保护作用:在静止状态下,它使您的指关节保持伸直,并轻柔地向拇指侧(桡侧)牵引,以矫正既往的偏斜。请遵医嘱佩戴——最初约六周内需昼夜佩戴——仅在清洗及手部治疗师允许脱离夹板进行锻炼时取下。手指上的环带应佩戴舒适;如有任何摩擦或压迫感,请告知您的治疗师。
持续佩戴约6周,随后按指导在夜间/休息时佩戴
Kieran Hirpara 4.0
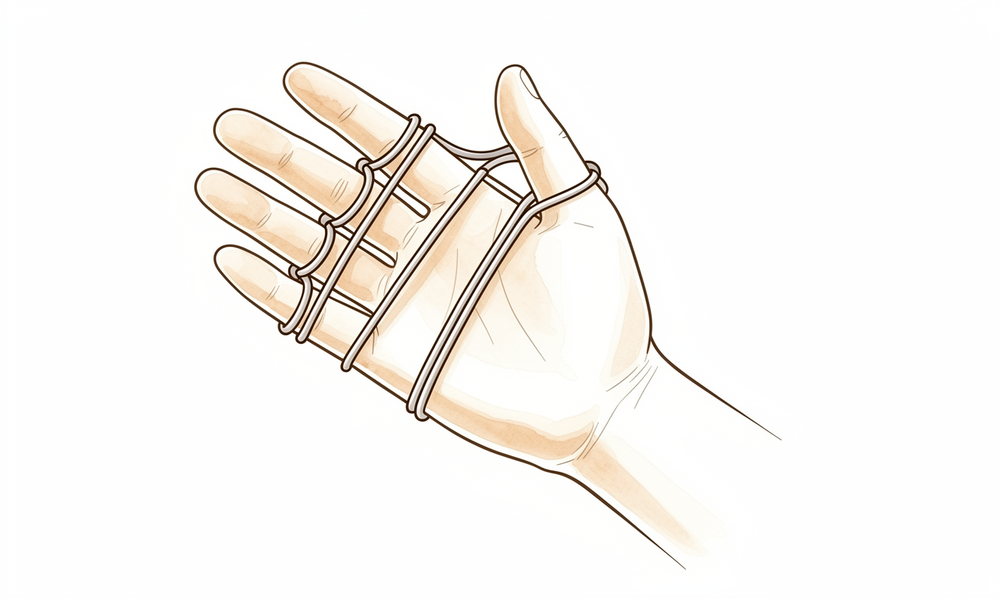
支具中受控的指关节屈曲
佩戴支具时,在掌指关节处轻轻向下弯曲手指,对抗弹性环的阻力,然后放松,让支具将手指弹回伸直位置。这种早期的受控运动有助于使新关节周围的愈合关节囊处于良好位置。动作应平稳,并在疼痛出现前停止——您是在引导关节,而非强行移动它。
清醒状态下,每小时进行10次弯曲练习,在夹板内进行,并遵循指导
Kieran Hirpara 4.0
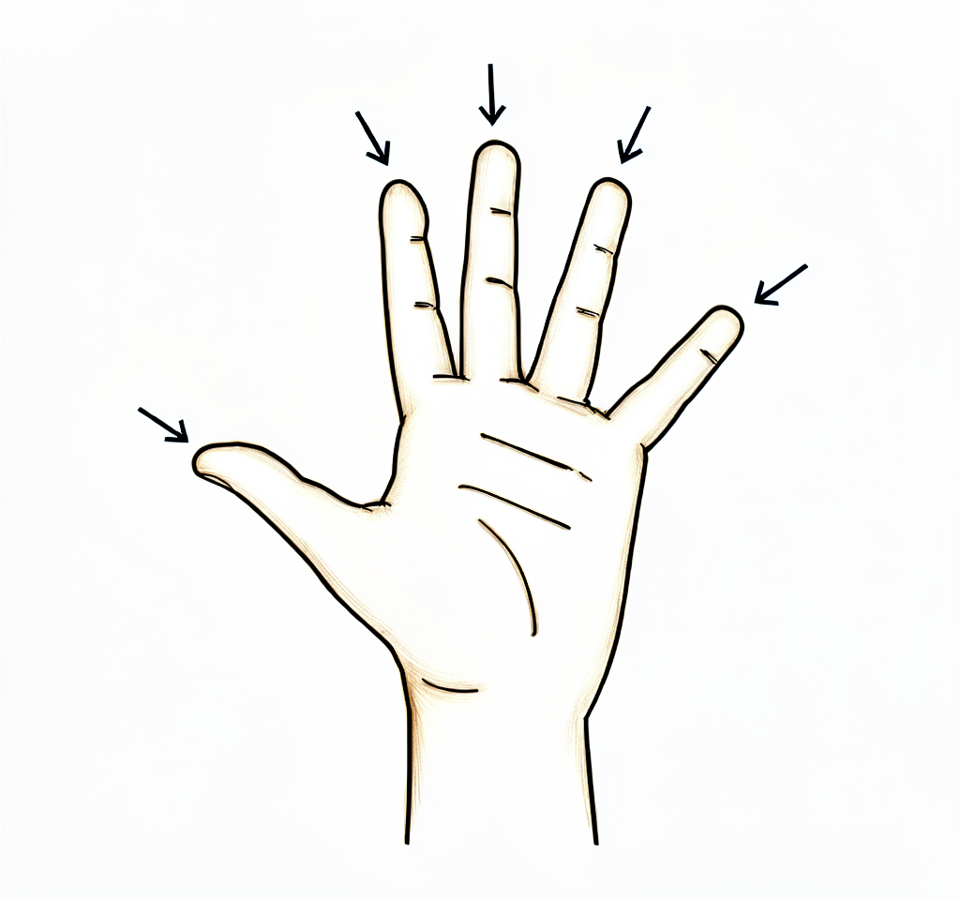
主动伸直(抬起指关节)
在自身力量的作用下,将指关节完全伸直——将手指向上抬起至水平位置。术后指关节可能出现下垂(伸肌迟滞),因此主动抬起手指有助于保持伸直肌腱的滑动,并帮助维持矫正效果。治疗师会在夹板内开始进行此练习,随后逐步过渡到脱离夹板后进行。
10次抬举,每天数次,按指导进行
Kieran Hirpara 4.0
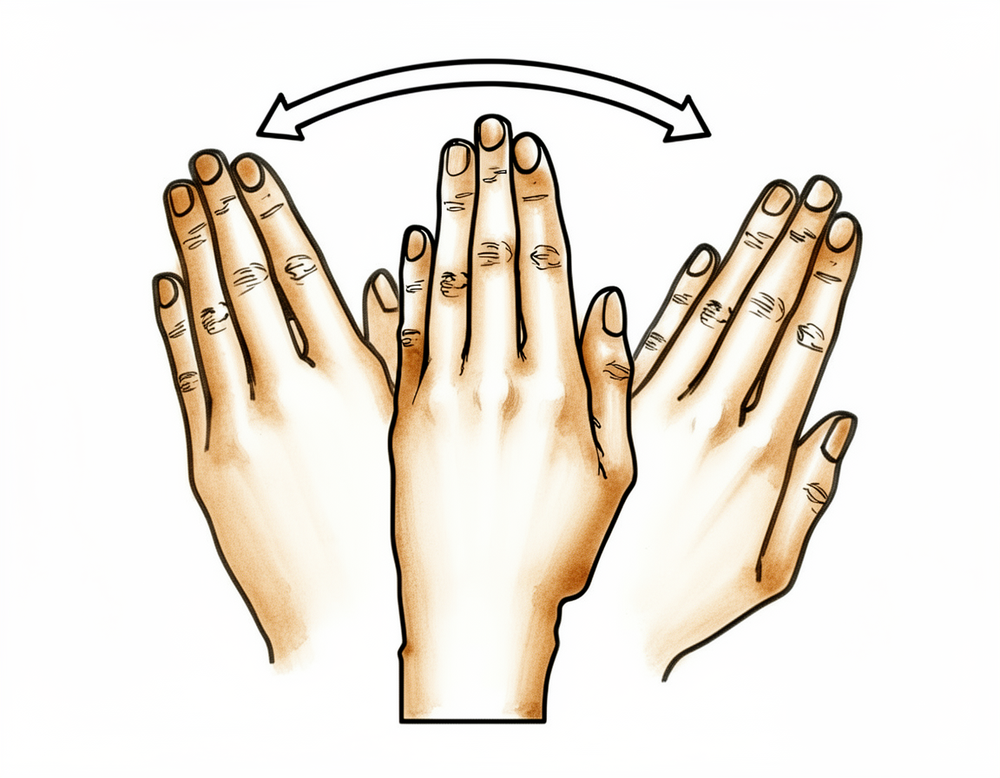
手指向拇指(桡侧)方向行走
轻轻引导手指向拇指方向(桡侧)移动——与旧的偏斜方向相反。您可以借助另一只手,或让指尖沿桌面向拇指方向滑动。这有助于重新训练手指保持笔直排列,是整个方案的核心矫正要点。切勿让手指再次向相反方向偏斜。
10次,每天数次,遵医嘱

Kieran Hirpara 4.0
疤痕护理
待您的伤口完全愈合且治疗师确认安全后,请使用少量普通乳霜按摩手背上的疤痕,以小而有力的圆圈方式按摩几分钟。这有助于保持疤痕柔软,防止皮肤粘连于肌腱之上,从而使指关节活动更加自如。
每天2-3次,每次几分钟,愈合后

Kieran Hirpara 4.0
握力强化(后期)
后期练习——仅在手部治疗师确认可进行强化训练后方可开始,通常在约十二周时。轻轻挤压软球或治疗用橡皮泥,然后松开。逐步增加强度。早期不进行此练习,是因为用力抓握会促使手指向尺侧偏斜,并在关节囊变得牢固之前对新关节造成压力——因此它始终是最后开始的练习。
遵照您的手部治疗师的指导(仅在约12周后开始)
这些是您的手册中列出的锻炼项目。仅在Hirpara医生和您的手部治疗师的指导下开始这些锻炼,并严格保持在您被允许的范围内和限制内。早期的锻炼均在佩戴动态支具的情况下进行:对抗环扣进行受控弯曲,主动伸直,以及轻轻将手指向拇指方向移动以维持矫正效果。伤口愈合后开始疤痕护理,握力强化属于后期阶段,在获得明确许可前不应开始。停止任何导致指关节剧烈疼痛的动作。
您的临床方案
本页其余部分为硅胶(Swanson)掌指关节(MCP)置换术后康复的分阶段临床方案。本节内容应提供给您的手部治疗师,每个阶段均以通俗易懂的语言解释正在发生的情况。核心原则是,新的掌指关节囊会围绕植入物在您保持的任何位置上进行重塑,因此夹板和练习旨在将关节保持在伸展伴轻度桡偏的位置,同时允许早期受控的主动屈曲,从而在矫正后的位置重塑关节并逆转尺侧偏斜。
在治疗前,请查阅患者的手术报告及既往病史,并与主刀医生就诊断(类风湿性关节炎与骨关节炎)、所进行的软组织重建手术(桡侧副韧带加固、尺侧内在肌松解、伸肌腱中央化/交叉内在肌转位)以及术中实现的矫正角度和活动范围进行沟通。类风湿性手部较骨关节炎手部更易出现偏斜和复发,因此需要格外严谨的桡偏夹板固定。以下方案假设采用标准的动态伸展支具方案。
第一阶段 — 动态伸指夹板配合早期可控活动(第0至约6周)
前六周是决定性窗口期:关节囊此刻正在植入物周围形成,而动态夹板决定了其形成的位置。通常在术后 3-5 天内,佩戴基于前臂的动态掌指关节(MCP)伸指外展架夹板。静止状态下,该夹板使MCP关节处于完全伸直位,近节指骨被拉向轻微桡偏位(纠正旧的尺侧偏斜);外展架吊带位于近节指骨上,弹性张力允许受控的主动屈曲,随后将手指复位至伸直位。患者需在清醒的每个小时进行夹板内的早期受控主动MCP屈曲。腕关节和指间关节(IP)保持自由活动。
致您的手部治疗师:
健康教育与注意事项 - 佩戴并调节动态伸指外展架夹板的张力:MCP关节保持在伸直位 + 轻微桡偏位,吊带位于近节指骨,桡侧拉力以对抗尺侧偏斜 - 连续佩戴(昼夜)约6周,仅在清洁和监护下的锻炼时取下 - 禁止强力抓握、捏持或侧向(尺向)负荷:这些动作会重现畸形力 - 保护软组织重建(桡侧副韧带/内在肌平衡):始终避免强制的尺偏应力 - 保持拇指、腕关节和IP关节的活动度;仅允许轻负荷手部使用
管理 - 伤口:按医嘱使用外科敷料;监测感染迹象(存在植入物) - 水肿:抬高患肢、轻柔的逆向按摩、在可耐受范围内进行轻度加压 - 锻炼:在夹板内对抗环扣进行受控的主动MCP屈曲,旨在建立有用的屈曲活动范围(目标为术中所确定的活动范围,通常食指至小指的MCP关节可达约70度),并通过外展架实现完全被动复位至伸直位;主动MCP伸直(纠正伸肌滞后);桡偏再教育(引导手指向拇指方向);IP关节和腕关节自由活动范围(ROM)
进展标准 - 伤口愈合;水肿消退;在约六周时,出现主动屈曲活动范围,同时保持伸直位并纠正(桡向)对线
第二阶段 — 逐步停用支具并巩固矫正(约第6周至第12周)
从大约第6周开始,关节囊正在成熟,动态支具逐步过渡为休息/夜间伸展位支具(通常持续至约第12周,对于易复发的类风湿性关节炎手部,夜间佩戴时间可能更长)。支具外的主动活动逐步增加,始终侧重于伸展位和桡侧对线。轻度功能性使用范围扩大;强握力和捏力仍被禁止。
致您的手部治疗师:
评估 - 主动和被动掌指关节(MCP)屈伸活动范围;伸肌滞后;尺侧偏斜(与术中矫正情况进行比较);疼痛和肿胀;伤口/瘢痕检查
教育与注意事项 - 逐步停用动态支具;继续佩戴夜间/休息位伸展位支具至约第12周(类风湿性关节炎患者夜间佩戴时间更长) - 继续避免强力握持/捏取以及任何导致尺侧偏斜的负荷 - 密切保持桡侧矫正;偏斜复发是主要的晚期失败原因
管理 - 练习:在支具外逐步进行主动及轻柔的主动辅助掌指关节(MCP)屈伸;持续进行伸肌滞后训练和桡侧偏斜再教育;愈合后开始瘢痕管理;在舒适范围内进行轻度功能性任务,避免尺侧偏斜模式
进展标准 - 在成熟的关节囊上矫正稳定(尺侧偏斜复发极少,伸肌滞后可接受);舒适的功能性活动范围;疼痛缓解
第三阶段——强化与恢复(约12周及以后)
当关节囊坚固且对位保持稳定(约12周时),应谨慎且较晚地引入分级强化训练,因为抓握力会驱动尺侧偏斜。力量和最终功能结果在接下来的数月内仍会继续改善。
致您的手部治疗师:
评估 - 抓握/捏力与对侧及术前对比;负重下维持的活动范围、伸展及对位;功能性及任务特异性测试
教育与注意事项 - 仅从约 12 周开始进行分级抓握/强化训练,并逐渐增加负荷 - 指导不驱动尺侧偏斜的抓握模式;根据指征持续使用夜间支具,尤其是类风湿手部 - 设定现实预期:目标是缓解疼痛、纠正位置和功能活动范围,而非正常或有力的手部
管理 - 练习:渐进性橡皮泥/球抓握和捏力,掌指关节等长控制,功能性强化;继续活动度训练及任何残留的伸肌滞后/对位训练 - 一旦纠正稳定、获得有用的活动范围且患者能管理日常功能,可考虑出院;提供长期夜间支具和关节保护计划 - 如果对位恶化、活动范围丧失或怀疑植入物问题,请转回主治医生
出院标准 - 稳定的纠正对位,无痛的功能活动范围,足够的功能抓握力,良好的关节保护和夜间支具常规
重返工作与活动
鼓励从初期开始进行轻度日常手部使用(如进食、书写、轻度自我护理),以舒适为限,前提是避免强力抓握、捏持以及手指的任何侧向(尺侧)应力。计划在前六周内几乎全天佩戴动态夹板,这将限制双手操作和重体力任务;请相应安排协助。驾驶将在您能够安全控制车辆且驾驶时已脱离动态夹板后恢复(通常在六周左右),并经复查确认。
强化训练和较重的手部使用需等待至约十二周,随后在手治疗师的指导下逐步增加强度。大多数人约在三个月时即可恢复大多数日常活动,最终效果(舒适度、对位及有效活动范围)将在随后的数月内继续稳定。进展由Hirpara医生和您的手治疗师根据手部矫正和功能情况评估,而非仅依据日历时间。较重或重复性体力工作遵循相同的基于标准的进展方案,并提供关节保护建议以长期维持矫正效果。
您的方案之后
本方案与本诊所的一般康复建议并行使用:请参阅 术后疼痛管理、伤口护理 和 疤痕管理。上述分阶段计划反映了硅胶 MCP 关节置换术后长期沿用的 Swanson 式康复方案,您的持续康复将由 Hirpara 医生和您的手部治疗师根据您手部的矫正情况和进展进行个别指导。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: post-operative rehabilitation after silicone (Swanson) replacement of the metacarpophalangeal (MCP) joints — flexible silicone-elastomer spacer arthroplasty of the knuckle joints, most often for the rheumatoid hand with ulnar drift and volar subluxation, and less commonly for MCP osteoarthritis. This is a resection-replacement with soft-tissue rebalancing, not a simple decompression: the deforming forces that destroyed the joint (ulnar drift, extensor subluxation, intrinsic tightness) are still present, so the rehabilitation is an active, splint-driven re-shaping programme, not a rest-and-protect pathway.
Defining principle of the rehab here: a silicone MCP implant is a flexible spacer around which a new fibrous capsule ("encapsulation") forms over the first weeks — and that capsule remodels in whatever position the hand is held. The classic post-operative regime therefore uses a dynamic extension outrigger splint that holds the MCPs in extension with slight radial deviation (opposing the ulnar drift) while permitting early controlled active flexion against elastic loops. Move early, but only in the corrected position: this is what reverses the drift and builds a functional flexion arc. The single biggest branch point is the diagnosis — the rheumatoid hand drifts and recurs far more readily than the osteoarthritic hand and warrants more diligent, more prolonged radial-deviation splinting.
A. PROCEDURE OUTCOMES (rheumatoid and osteoarthritis)
Silicone MCP arthroplasty is a deformity-correcting, pain-relieving operation rather than a motion- or strength-restoring one. Its great strength is reliable correction of alignment and relief of pain; its accepted limitations are a modest final arc, gradual implant fracture over years, and—in rheumatoid hands—a tendency to recurrent drift.
- In rheumatoid arthritis it produces durable improvement in deformity, appearance and patient-reported function. The multicentre prospective SARA (Silicone Arthroplasty in Rheumatoid Arthritis) cohort compared 70 surgical with 93 non-surgical RA patients with severe MCP deformity: the surgical group showed significant, sustained gains in the Michigan Hand Outcomes Questionnaire and in ulnar deviation, extensor lag and arc of motion, maintained at 1 year, at long-term (3-year) follow-up, and out to 7 years, whereas the non-surgical cohort did not improve [Chung 2009; Chung 2012; Chung 2017]. Moderate–strong (prospective comparative cohort; not randomised).
- Correction of ulnar drift and extensor lag is the headline result; arc and grip gains are modest. Series consistently report large reductions in ulnar deviation and extensor lag with a re-centred, more functional arc (commonly a final arc on the order of ~40–50° centred nearer extension), with grip strength only modestly changed. The operation buys alignment, pain relief and hand appearance/function, not power [Goldfarb & Dovan 2006; Rizzo 2011; Kirschenbaum 1993]. Moderate.
- For MCP osteoarthritis, long-term results are favourable and durable. A long-term series of silicone MCP arthroplasty for OA reported lasting pain relief and satisfactory function, with better-preserved bone stock and less recurrent deforming force than the rheumatoid hand [Morrell & Weiss 2018]. Moderate.
- Implant fracture accrues with time but is often clinically silent. Long-term radiographic follow-up shows implant fracture rates rising over the years, yet many fractured implants remain asymptomatic and revision is driven by symptoms/instability rather than radiographic fracture alone [Koenuma 2024; Kirschenbaum 1993]. Moderate.
- Revision is uncommon but defined, most often for recurrent deformity, implant fracture/instability or infection; revision MCP arthroplasty is feasible but technically demanding with poorer results than primary surgery [Wagner 2019; Carlson Strother 2023]. Moderate.
B. REHABILITATION / THERAPY EVIDENCE
The central rehab questions are (1) which splint regime, and (2) does adding continuous passive motion or particular splint variants change the outcome. The evidence base is dominated by a strong heritage regime (Swanson-style dynamic extension splinting) supported mostly by expert consensus and low-level studies, with the few controlled comparisons failing to show benefit from add-ons. The rehabilitation is nonetheless indispensable — it is integral to the operation, not an optional adjunct.
- The standard regime is a dynamic extension outrigger splint with early controlled motion. Fitted within the first few days, it holds the MCPs in extension and slight radial deviation at rest and permits active flexion against finger slings, worn essentially continuously for ~6 weeks then weaned to night/rest splinting. The shared aim across published regimes is to encourage MCP flexion and extension without recurrence of flexion contracture or ulnar deviation while the capsule encapsulates the implant in a corrected position [Goldfarb & Dovan 2006; Massy-Westropp Cochrane 2008]. Consensus / heritage — widely practised, low-level evidence.
- Adding continuous passive motion (CPM) to dynamic splinting does not help. The Cochrane review identified a single small controlled trial (22 participants) comparing dynamic splinting ± CPM and concluded CPM is not effective at increasing motion or strength after MCP arthroplasty (controls actually gained more motion); it rated the evidence "silver level" and called for well-designed RCTs given wide practice variation [Massy-Westropp Cochrane 2008]. Moderate (Cochrane SR of low-certainty primary evidence).
- A static-splint alternative achieves comparable correction in small studies. A prospective series using alternating static flexion/extension splints (rather than a dynamic outrigger) reported improved total active arc (21.6°→47.2°) and corrected ulnar deviation (30.4°→9.7°), suggesting the position held and active motion matter more than the specific splint mechanism [Burr/Massy-Westropp J Hand Ther 2002]. Weak (small prospective cohort).
- The specific dynamic-splint protocol has not been shown superior to simpler regimes in controlled comparison. A randomised study found no clear added value of dynamic splinting over a simpler post-operative regime for MCP replacement, reinforcing that the dynamic outrigger is a sound, traditional default rather than a proven optimum [Delaney 2003]. Weak–moderate (small RCT).
Recovery trajectory (expected, evidence-anchored)
| Phase | Window | Splint / position | Hand-therapist focus | Strength / load | Notes |
|---|---|---|---|---|---|
| I — Dynamic extension splint + early controlled motion | Week 0–~6 | Dynamic extension outrigger worn day & night; MCPs in extension + slight radial deviation | Controlled active MCP flexion within the splint (toward the surgeon's arc, often up to ~70°); active extension (correct extensor lag); radial-deviation re-education; free IP/wrist; oedema control | Light unloaded use only; no grip/pinch, no ulnar load | Capsule forms now — position held = position kept. Rheumatoid hands need the most diligent radial pull |
| II — Wean to night/rest splint, consolidate correction | Week ~6–12 | Wean dynamic splint → night/resting extension splint (longer at night in RA) | Progress active/active-assisted flexion–extension out of splint, biased to extension + radial; scar massage once healed; preserve correction | Still no strong grip/pinch; light functional tasks | Recurrent ulnar drift is the main late failure — guard alignment |
| III — Strengthening & return | Week ~12+ | Night splint as indicated (esp. RA) | Graded putty/ball grip and pinch, isometric MCP control, functional/task strengthening | Begin grip strengthening ~8–12 wk, build gradually; coach non-ulnar-deviating grip | Most everyday activity by ~3 months; alignment/comfort/arc settle over several more months |
(Phase windows mirror the patient protocol; they are typical, heritage-based guides — not trial-derived deadlines.)
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Heritage regime, modest evidence. The Swanson-style dynamic extension outrigger with early controlled motion is deeply established and near-universally taught, but its supporting evidence is largely expert consensus and small/low-level studies. The defensible position is to follow the heritage regime faithfully while acknowledging its evidence tier [Goldfarb & Dovan 2006; Massy-Westropp Cochrane 2008]. Consensus.
- Which splint? Dynamic outrigger vs alternating static splints vs simpler regimes give broadly similar correction in small studies; CPM adds nothing. What matters is holding the MCPs in extension + radial deviation while moving early — the mechanism of the splint is secondary [Massy-Westropp Cochrane 2008; Burr 2002; Delaney 2003]. Weak–moderate.
- Rheumatoid vs osteoarthritis. The rheumatoid hand has ongoing deforming forces (tendon subluxation, intrinsic tightness, soft-tissue laxity) and recurs, demanding more prolonged radial-deviation/night splinting and joint protection; the osteoarthritic hand has better bone and soft tissue and a more durable correction [Morrell & Weiss 2018; Rizzo 2011]. Moderate.
- Realistic goals. The operation reliably delivers pain relief, corrected alignment and a functional arc, not a normal or powerful hand. Mis-set expectations (large grip gains) are a common source of dissatisfaction [Chung patient-expectations 2015; SARA cohort]. Moderate.
- Implant fracture ≠ failure. Radiographic implant fracture accrues over years but is frequently asymptomatic; revision is symptom-driven. Counsel accordingly rather than revising on imaging alone [Koenuma 2024; Wagner 2019]. Moderate.
D. EVIDENCE STRENGTH FLAGS (summary)
- MODERATE–STRONG: silicone MCP arthroplasty improves deformity, alignment (ulnar deviation, extensor lag), MHQ and arc versus non-surgical care in severe rheumatoid MCP disease, durable to 7 years (SARA prospective cohort — comparative, not randomised).
- MODERATE: correction-over-power outcome profile; favourable long-term OA results; time-related implant fracture (often asymptomatic); defined but uncommon revision rate; greater recurrence in rheumatoid than osteoarthritic hands.
- WEAK / CONSENSUS / HERITAGE: the specific dynamic-extension-outrigger + early-controlled- flexion + radial-deviation rehabilitation programme (strong heritage, low-level evidence; CPM shown unhelpful; dynamic vs static vs simpler regimes not clearly differentiated); exact phase timings (typical, not trial-derived).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Kirschenbaum D, Schneider LH, Adams DC, et al. Arthroplasty of the metacarpophalangeal joints with use of silicone-rubber implants in patients who have rheumatoid arthritis. Long-term results. J Bone Joint Surg Am. 1993;75(1):3-12. DOI: 10.2106/00004623-199301000-00002
- Goldfarb CA, Dovan TT. Rheumatoid arthritis: silicone metacarpophalangeal joint arthroplasty indications, technique, and outcomes. Hand Clin. 2006;22(2):177-188. DOI: 10.1016/j.hcl.2006.02.001
- Rizzo M. Metacarpophalangeal joint arthritis. J Hand Surg Am. 2011;36(2):345-353. DOI: 10.1016/j.jhsa.2010.11.035
- Morrell NT, Weiss AC. Silicone metacarpophalangeal arthroplasty for osteoarthritis: long-term results. J Hand Surg Am. 2018;43(3):229-233. DOI: 10.1016/j.jhsa.2017.10.010
- Koenuma N, Ikari K, Oh K, et al. Long-term implant fracture rates following silicone metacarpophalangeal joint arthroplasty in rheumatoid arthritis. J Hand Surg Am. 2024. DOI: 10.1016/j.jhsa.2024.01.009
- Wagner ER, Houdek MT, Packard B, et al. Revision metacarpophalangeal arthroplasty: a longitudinal study of 128 cases. J Am Acad Orthop Surg. 2019. DOI: 10.5435/JAAOS-D-17-00042
- Carlson Strother CR, Moran SL, Rizzo M. Small joint arthroplasty of the hand: an update on indications, outcomes, and complications. J Am Acad Orthop Surg. 2023;31(15):e739-e749. DOI: 10.5435/JAAOS-D-23-00034
- Blazar PE, Gancarczyk SM, Simmons BP. Rheumatoid hand and wrist surgery: soft tissue principles and management of digital pathology. J Am Acad Orthop Surg. 2019;27(21):e924-e933. DOI: 10.5435/JAAOS-D-17-00608
- Naniwa S, Nishida K, Nasu Y, et al. A comparative study of short-term outcomes between INTEGRA and AVANTA silicone implants for metacarpophalangeal joints in patients with rheumatoid arthritis. J Hand Surg Am. 2026. DOI: 10.1016/j.jhsa.2026.04.003
MCP arthroplasty outcomes & rehabilitation literature (URLs)
- Chung KC, Burns PB, Wilgis EFS, et al. A multicenter clinical trial in rheumatoid arthritis comparing silicone metacarpophalangeal joint arthroplasty with medical treatment. J Hand Surg Am. 2009;34(5):815-823. DOI: 10.1016/j.jhsa.2009.01.018 — https://pmc.ncbi.nlm.nih.gov/articles/PMC4381953/
- Chung KC, Burns PB, Kim HM, et al. Long-term followup for rheumatoid arthritis patients in a multicenter outcomes study of silicone metacarpophalangeal joint arthroplasty. Arthritis Care Res (Hoboken). 2012;64(9):1292-1300. DOI: 10.1002/acr.21705 — https://pubmed.ncbi.nlm.nih.gov/22511483/
- Burns PB, Zhong L, Chung KC. Seven-year outcomes of the Silicone Arthroplasty in Rheumatoid Arthritis (SARA) prospective cohort study. Arthritis Care Res (Hoboken). 2017. DOI: 10.1002/acr.23105 — https://pmc.ncbi.nlm.nih.gov/articles/PMC5376377/
- Chung KC, Burns PB, et al. Patient expectations and long-term outcomes in rheumatoid arthritis patients: results from the SARA study. Clin Rheumatol. 2015;34(4):641-651. DOI: 10.1007/s10067-014-2775-z — https://pubmed.ncbi.nlm.nih.gov/25267562/
- Massy-Westropp N, Johnston RV, Hill C. Post-operative therapy for metacarpophalangeal arthroplasty. Cochrane Database Syst Rev. 2008;(1):CD003522. DOI: 10.1002/14651858.CD003522.pub2 — https://pmc.ncbi.nlm.nih.gov/articles/PMC8715905/
- Burr N, Pratt AL, Stott D. An alternative splinting and rehabilitation protocol for metacarpophalangeal joint arthroplasty in patients with rheumatoid arthritis. J Hand Ther. 2002;15(1):41-47. DOI: 10.1053/hanthe.2002.v15.01541 — https://pubmed.ncbi.nlm.nih.gov/11866351/
- Delaney R, Trail IA, Nuttall D. Value of dynamic splinting after replacement of the metacarpophalangeal joint in patients with rheumatoid arthritis. Scand J Plast Reconstr Surg Hand Surg. 2003;37(4):232-233. DOI: 10.1080/02844310310005658 — https://pubmed.ncbi.nlm.nih.gov/12755512/





