

Blood Thinners Around Surgery Info
Reviewed by Dr Kieran Hirpara, Specialist Orthopaedic Surgeon Last reviewed
"Blood thinner" covers two families of medicine that work in completely different ways, and for upper-limb surgery our instruction depends on which family you take. Antiplatelet medicines such as aspirin and clopidogrel are continued. Anticoagulants such as warfarin, Xarelto, Eliquis and Pradaxa are stopped 48 hours before your operation. Knowing which one you take, and how it actually works, makes those two instructions far less mysterious.
First, how does blood actually clot?
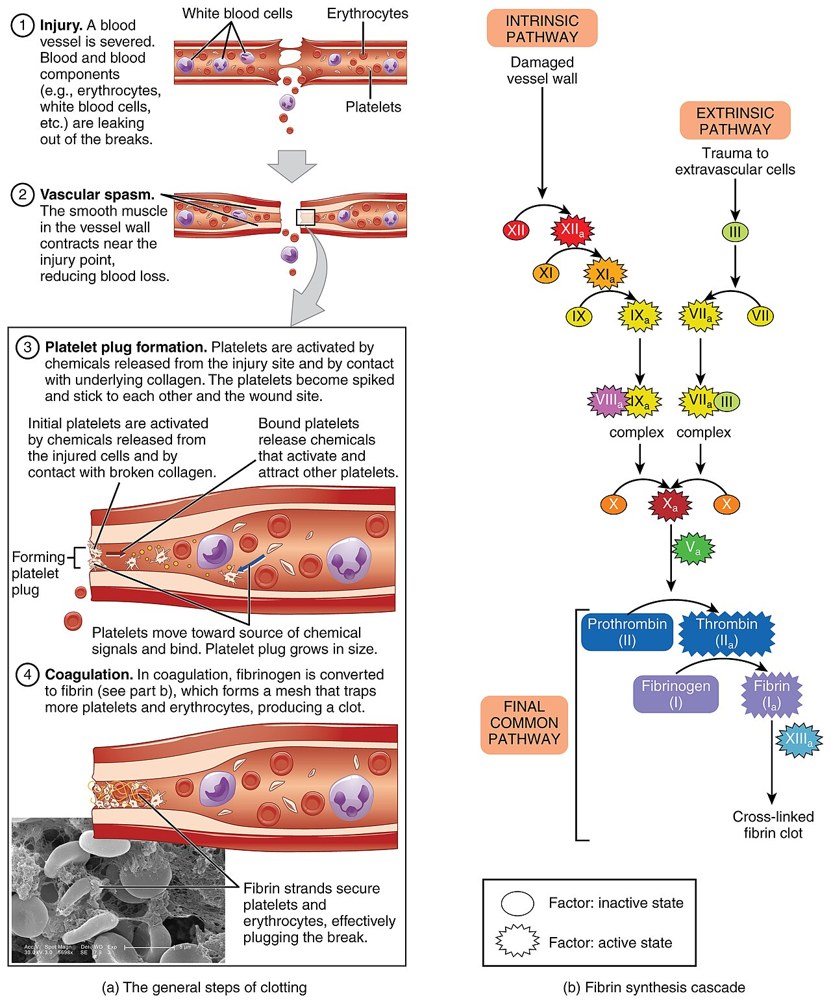
To make sense of the different blood thinners it helps to know how your blood normally seals a leak, because each medicine interrupts a different step.
When a blood vessel is cut or damaged, your body plugs it in two stages:
-
Platelets plug the gap: the fast first responders. Platelets are tiny cell fragments that circulate in the blood doing nothing until they are needed. The instant they meet a damaged vessel wall they turn sticky, pile onto the injury and clump together, forming a soft, temporary plug within seconds to minutes. Think of it as the body's emergency patch.
-
The clotting cascade sets the plug solid. That platelet plug is fragile on its own. To reinforce it, the blood runs a chain reaction called the clotting cascade, a series of proteins called clotting factors (most made by the liver, several of them needing vitamin K) that switch one another on in sequence, like a row of dominoes. The cascade finishes by turning a protein called fibrinogen into fibrin, a mesh of fine threads that weaves through the platelet plug and locks it into a firm, stable clot.
So a finished clot is really platelets held together by a fibrin mesh. When it seals a wound that is exactly what you want; but the same process happening unwanted inside an artery or vein causes a heart attack, stroke or DVT. That is what blood thinners are prescribed to prevent.
Here is the key to everything below: the two families of blood thinner each jam a different stage. Antiplatelet medicines blunt the first step (the platelets); anticoagulant medicines interrupt the second (the clotting- factor cascade). That single difference also explains why the timing before surgery is so different, because "undoing" a platelet is not the same as "undoing" a clotting factor.
Antiplatelet medicines
(aspirin, clopidogrel/Plavix, ticagrelor/Brilinta, prasugrel/Effient)
These stop the tiny blood cells called platelets from sticking together to start a clot.
- Aspirin and clopidogrel (and prasugrel) work irreversibly: once the drug reaches a platelet, that platelet is switched off for the rest of its life. Your body cannot turn it back on. The only way back to normal clotting is to make brand-new platelets, and platelets live only about 7–10 days, with roughly 10% replaced each day. A short break therefore achieves very little, and a long enough break to matter would leave a heart stent or a stroke risk unprotected for a week. That is why we do not ask you to stop them: the small bleeding risk is outweighed by the clot risk.
- Ticagrelor is reversible; it lets go of the platelet rather than permanently disabling it, so it clears a little faster than the irreversible ones.
- Aspirin and clopidogrel are continued. Do not stop them for your operation, and that includes the combination tablets (DuoCover, DuoPlidogrel, Piax Plus Aspirin). We ask whether you take them so that the team knows and can plan around it. If we do want you to stop a blood thinner, the instruction will be in your surgery details email; if your email carries no such instruction, keep taking everything as normal.
Anticoagulants
These work further down the clotting chain, on the clotting factors in the blood rather than on the platelets.
Warfarin (Coumadin, Marevan). Warfarin stops your liver from making several vitamin-K-dependent clotting factors. It does not remove the factors already circulating; those have to be used up and cleared naturally, which takes about 5 days. Our instruction for warfarin is to stop it 48 hours before, so on the day it is still having some effect. That is expected; if we want a blood test (the INR) before your operation, we will arrange it and tell you.
The newer tablets: DOACs (apixaban/Eliquis, rivaroxaban/Xarelto, dabigatran/Pradaxa, edoxaban). Each blocks a single specific clotting factor, and the body clears them quickly, with a half-life of around 12 hours. Because they wash out so fast, 48 hours is long enough for them to have largely cleared. Tell us if you have kidney problems, because the drug then takes longer to leave the body (especially dabigatran, which leaves mostly through the kidneys). They need no INR monitoring.
Heparin / low-molecular-weight heparin (enoxaparin/Clexane) injections. Short-acting; used to prevent clots. Because they wear off in hours, if you are on injections you will be given a specific time for your last one.
Why the timing is what it is — in one line
Two rules, one for each family.
Antiplatelet medicines (aspirin, clopidogrel and the combination tablets): keep taking them. A short break achieves little and a long one is dangerous, so we do not ask for either.
Anticoagulants (warfarin, Xarelto, Eliquis, Pradaxa): last dose 48 hours before your operation. In practice:
- Surgery on a Monday: last dose on the previous Friday night, or Saturday morning, depending on when you usually take it.
- Surgery on a Friday: last dose on the previous Tuesday night, or Wednesday morning.
Your surgery details email gives you the day and time worked out for you.
What you must do
- Bring an exact list of everything you take to your pre-operative assessment, including aspirin and supplements like fish oil, which also affect bleeding.
- If you take aspirin or clopidogrel, keep taking them, and make sure we know.
- If you take an anticoagulant, follow the last-dose day and time in your surgery details email, and the restart instructions you are given afterwards, exactly.
- Never stop, start or change a blood thinner on your own, and don't assume your timing matches a friend's.
- Tell every clinician involved that you take one.
After your operation
Blood thinners are restarted once the bleeding risk has settled, sometimes within a day, sometimes longer after higher-bleeding-risk surgery. You'll be told exactly when. The clot the medicine prevents doesn't disappear because you've had an operation, so restarting on time matters as much as stopping did.
Call us if
- You realise you took a dose you were told to skip, or skipped one you were told to take
- You have unusual or heavy bruising or bleeding, blood in the urine or stool, black tarry stools, or bleeding that won't stop
- You are unsure what to do with your blood thinner before your operation: always ask rather than guess





