

Các bài tập dành cho bệnh nhân nội trú — Thay khớp vai Thông tin
Đây là những bài tập nhẹ nhàng mà bạn có thể bắt đầu thực hiện tại bệnh viện sau khi phẫu thuật thay khớp vai (thay khớp toàn bộ, thay khớp ngược chiều, hoặc thay khớp do gãy xương). Các bài tập này giúp duy trì sự vận động của tay, khuỷu tay và vai trong lúc vết mổ đang lành lại.
Các bài tập của bạn

Kieran Hirpara 4.0
Chuyển động cổ tay
Hãy liên tục cử động tay bằng cách gập cổ tay về phía trước, phía sau và sang hai bên.
10 lần, 3 lần mỗi ngày.

Kieran Hirpara 4.0
Mở và nắm tay
Hãy cử động tay và các ngón tay bằng cách mở ra, khép lại, hoặc nắm chặt quả bóng giảm căng thẳng.
10 lần, 3 lần mỗi ngày.

Kieran Hirpara 4.0
Cử động gập khuỷu tay
Hãy gập và duỗi khuỷu tay của bạn.
10 lần, 3 lần mỗi ngày.

Kieran Hirpara 4.0
Con lắc
Đây là bài tập thụ động. Hãy cúi người về phía trước và để cánh tay thả lỏng. Dùng cơ thể để nhẹ nhàng di chuyển cánh tay theo chiều kim đồng hồ hoặc ngược chiều kim đồng hồ, đồng thời di chuyển về phía trước, phía sau và sang hai bên.
Khoảng 30 giây cho mỗi hướng, 3 lần mỗi ngày.

Kieran Hirpara 4.0
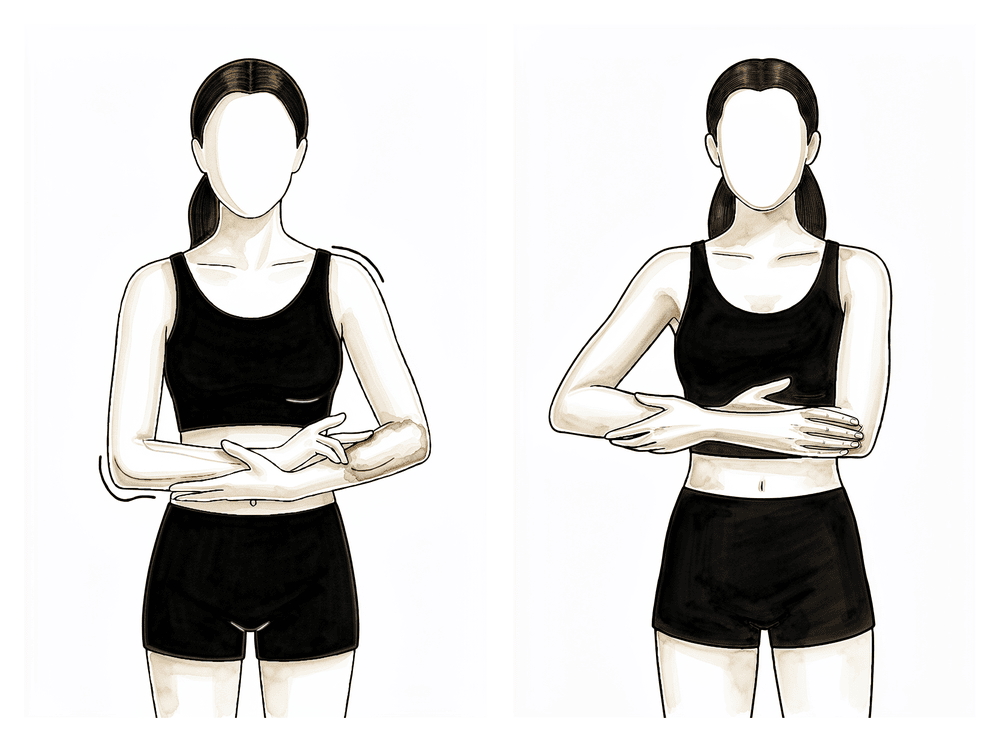
Hỗ trợ gập cánh tay về phía trước
Ngồi trên ghế và hơi cúi người về phía trước; dùng tay còn lại ôm lấy cánh tay vừa được phẫu thuật rồi nhẹ nhàng nâng nó lên phía trước người. Sau đó, dùng tay không phẫu thuật để hỗ trợ hạ cánh tay xuống. Nếu thích, bạn cũng có thể nằm ngửa trên giường và dùng tay không phẫu thuật để nâng cánh tay lên.
10 lần, 3 lần mỗi ngày
Kieran Hirpara 4.0
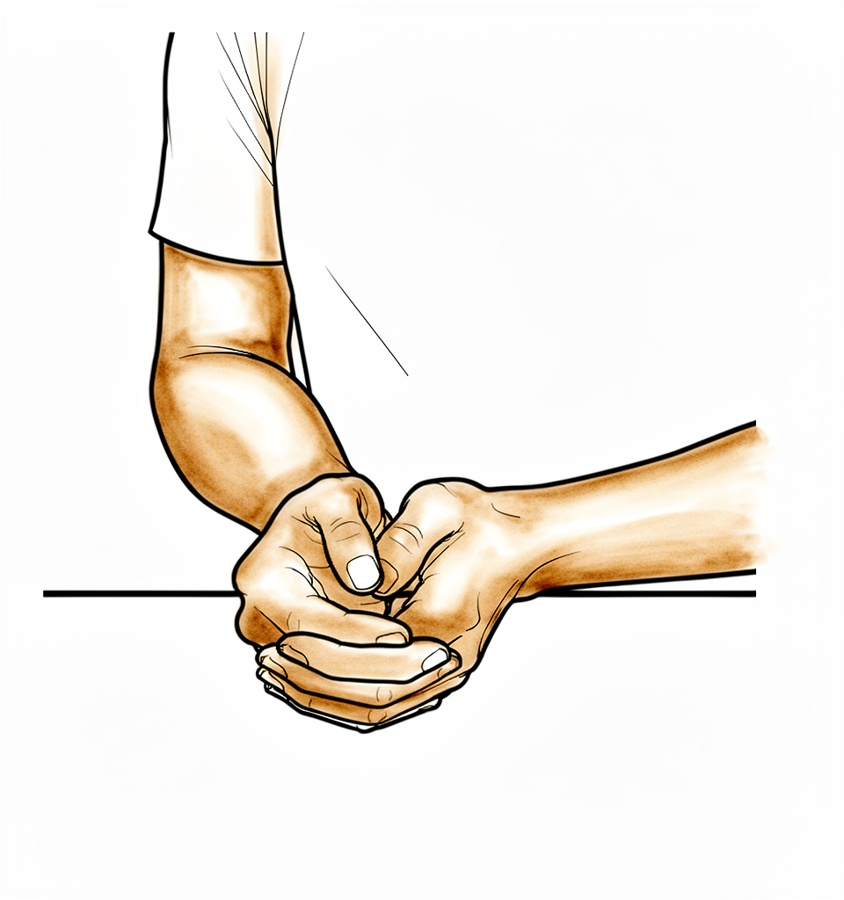
Hỗ trợ vận động cánh tay ra xa thân
Ngồi trên ghế và nghiêng người về phía trước; sau đó ôm lấy cánh tay và nhẹ nhàng đưa nó sang bên cạnh (giống như cách ru em bé vậy).
10 lần, 3 lần mỗi ngày.
Kieran Hirpara 4.0
Xoay ngoài
Ngồi trên ghế, chỉ cần di chuyển cánh tay từ vị trí đang được treo trong dây đeo sao cho nó hướng thẳng về phía trước. Đừng di chuyển cánh tay ra ngoài quá mức.
10 lần, 3 lần mỗi ngày.

Kieran Hirpara 4.0
Siết giữ cơ thang dưới
Hãy siết hai xương bả vai xuống dưới và khép lại gần nhau.
Giữ nguyên trong 5 giây, thực hiện 5 lần, ngày 3 lần.
Kieran Hirpara 4.0
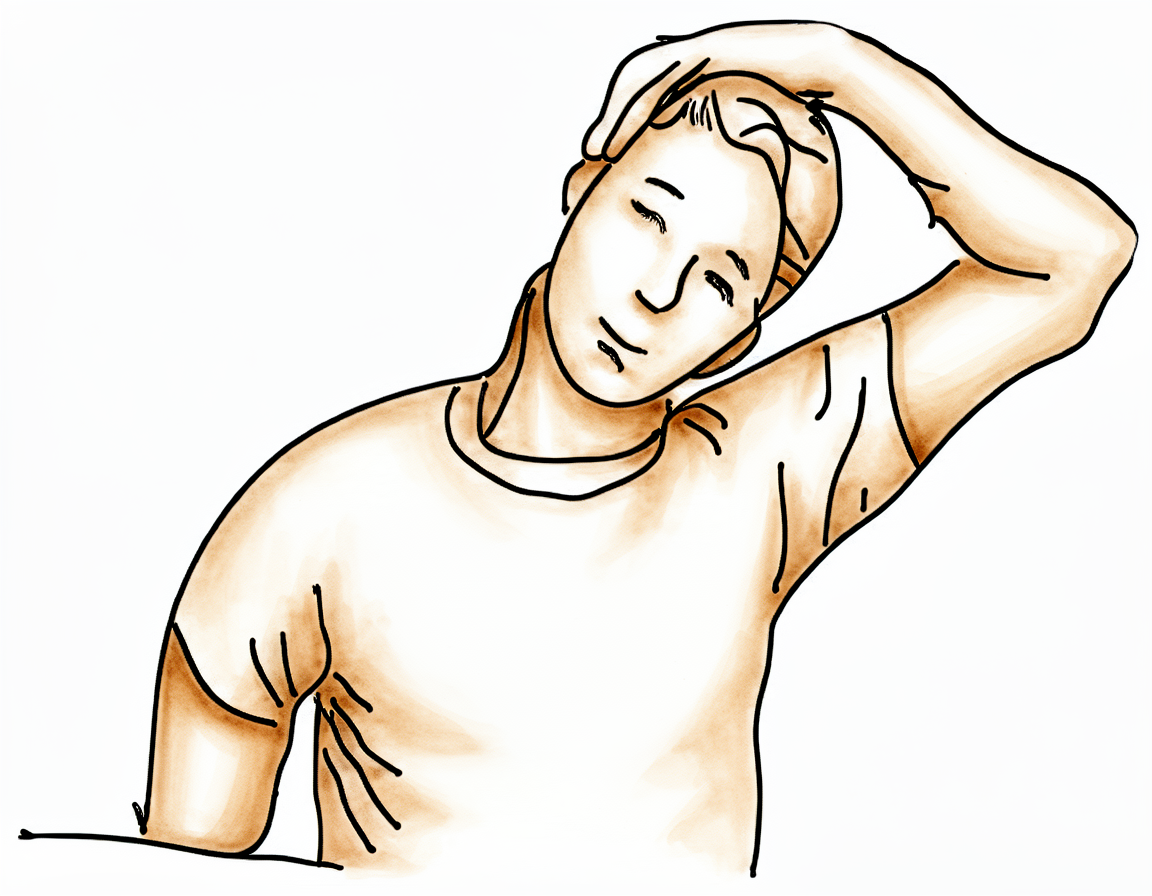
Kéo giãn cơ thang trên
Hãy dùng cánh tay chưa được phẫu thuật để đưa tai về phía vai, hướng ra xa phía cánh tay đã được phẫu thuật.
Giữ nguyên trong 10 giây, thực hiện 3 lần, ngày 3 lần.
Kieran Hirpara 4.0
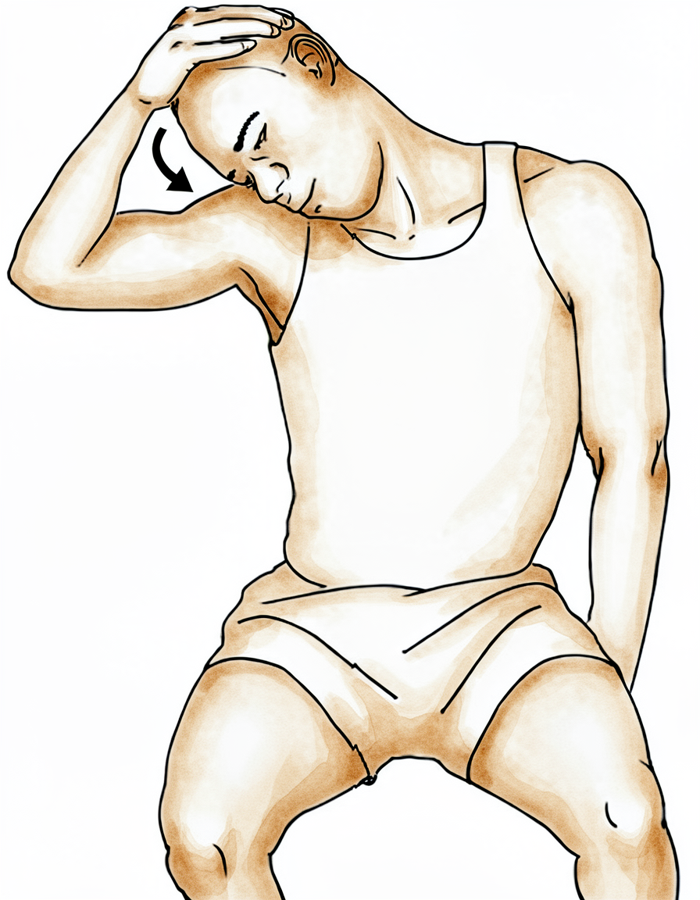
Bài tập kéo giãn cơ nâng xương bả vai
Hãy dùng cánh tay chưa được phẫu thuật để đưa mũi về phía vùng nách, hướng ra xa khỏi bên đã phẫu thuật.
Giữ nguyên trong 10 giây, thực hiện 3 lần, ngày 3 lần.
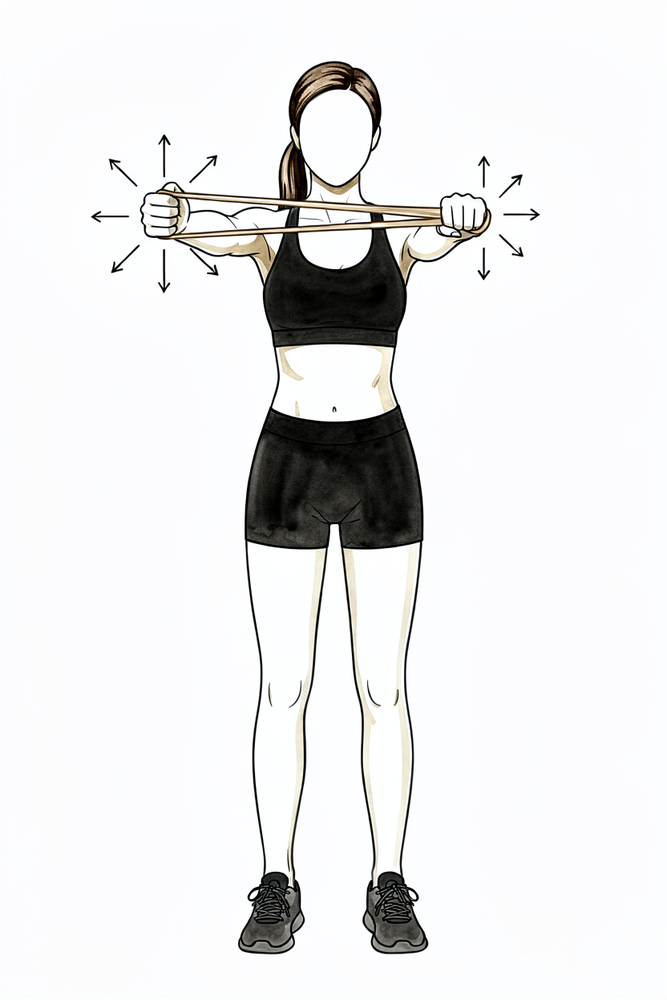
Kieran Hirpara 4.0
Ổn định theo nhịp điệu
Khi cánh tay được giữ nâng ngang tầm vai phía trước, hãy nhờ chuyên viên vật lý trị liệu (hoặc tay lành của bạn) thực hiện những lực đẩy nhẹ, nhỏ từ nhiều hướng khác nhau; trong lúc đó bạn phải giữ cánh tay cố định, không được để nó di chuyển. Bài tập này giúp các cơ ổn định vai phản ứng lại các lực tác động. Hãy thực hiện mọi động tác một cách nhẹ nhàng.
Theo hướng dẫn của chuyên viên vật lý trị liệu của bạn.
Hãy bắt đầu thực hiện những bài tập nhẹ nhàng này tại bệnh viện rồi tiếp tục ở nhà. Các bài tập này cần phải mang lại cảm giác thoải mái; hãy giảm mức độ tập nếu cảm thấy đau tăng lên.
Nếu bạn đã thực hiện phẫu thuật thay khớp ngược chiều, bạn có thể bắt đầu vận động vai sớm; hãy bắt đầu với các động tác có sự hỗ trợ hoặc dựa vào trọng lực (dễ thực hiện nhất là nằm ngửa để trọng lực hỗ trợ), sau đó mới thêm các động tác chủ động nhẹ nhàng khi cảm thấy thoải mái, nhưng vẫn phải giữ trong giới hạn cho phép. Chỉ cần tránh những tư thế được liệt kê trong mục “Cách đeo nẹp vai”.
Nếu bạn đã thực hiện phẫu thuật thay khớp toàn bộ (giải phẫu) hoặc thay khớp do gãy xương, hãy thực hiện các động tác ban đầu một cách nhẹ nhàng và có sự hỗ trợ như đã hướng dẫn; hãy để cánh tay còn lại thực hiện thay vì cánh tay được phẫu thuật, đồng thời không được vận động cánh tay này ra ngoài phạm vi quy định trong các bài tập, nhằm bảo vệ quá trình hồi phục ở phía trước vai.
Cách sử dụng đai treo cánh tay
Thời gian đeo đai treo phụ thuộc vào loại phẫu thuật thay khớp mà bạn đã thực hiện; vui lòng tuân theo hướng dẫn tương ứng.
Nếu bạn đã thực hiện phẫu thuật thay khớp ngược:
- Đai treo chủ yếu nhằm mang lại sự thoải mái và hỗ trợ; bạn chỉ cần đeo khoảng 2 tuần thay vì đeo suốt 6 tuần liên tục.
- Bạn có thể tháo đai ra để tập luyện và tắm rửa.
- Bạn có thể bắt đầu thực hiện các động tác nhẹ nhàng cho vai ngay lập tức (xem hướng dẫn tập luyện); không cần thiết phải giữ cánh tay hoàn toàn yên bất động.
- Trong những tuần đầu, có một vài tư thế cần tránh cho đến khi vết thương lành: không vươn tay ra phía sau người, không kết hợp động tác vươn tay ra sau với việc xoay cánh tay vào trong, không nâng vật gì lên, và không dùng tay để đẩy người lên (ví dụ: đẩy mình ra khỏi ghế). Chuyên viên vật lý trị liệu sẽ hướng dẫn cụ thể cho bạn về những điều này.
Nếu bạn đã thực hiện phẫu thuật thay khớp toàn phần (giải phẫu) hoặc thay khớp do gãy xương:
- Bạn phải đeo đai treo khi ngủ.
- Bạn có thể tháo đai ra để tập luyện và tắm rửa.
- Bạn cần đeo đai treo trong 6 tuần, đặc biệt là khi ra ngoài.
- Vết khâu ở phía trước vai cần thời gian để lành; vì vậy các động tác vận động ban đầu cần thực hiện một cách nhẹ nhàng và thận trọng. Hãy tuân thủ các bài tập có hỗ trợ được hướng dẫn và không nên cố gắng vươn tay ra ngoài phạm vi cho phép trong các bài tập.
Đối với tất cả các trường hợp:
- Nếu cần thiết, hãy chườm đá để giảm đau.
- Khi đeo đai treo, hãy thả lỏng vai và để đai gánh trọng lượng của cánh tay.
- Hãy uống thuốc giảm đau trước khi tập luyện và trước các buổi trị liệu vật lý.
- Trừ khi bạn đã tự sắp xếp dịch vụ vật lý trị liệu riêng, một lịch hẹn đã được đặt cho bạn và được ghi rõ trong bộ hồ sơ xuất viện.
- Nếu gặp bất kỳ vấn đề nào, hãy liên hệ với phòng khám hoặc thông báo cho chuyên viên vật lý trị liệu của bạn.
Khi về nhà
Sau khi về nhà, quá trình hồi phục của bạn sẽ tiếp tục theo đúng quy trình phục hồi chức năng sau phẫu thuật: thay khớp vai kiểu ngược; thay khớp vai toàn phần; thay khớp vai do gãy xương.
Những bằng chứng khoa học chứng minh tầm quan trọng của giai đoạn phục hồi sớm trong bệnh viện (tại sao cần đeo đai cố định và thực hiện các động tác nhẹ nhàng; tại sao bệnh nhân sau thay khớp vai kiểu ngược có thể vận động sớm và tự do, với lưu ý duy nhất là không để tay vươn ra phía sau cơ thể; tại sao bệnh nhân sau thay khớp vai toàn phần cần hạn chế vận động xoay ngoài để bảo vệ vùng phía trước khớp vai) đã được tóm tắt trong mục “Bằng chứng khoa học”, có sẵn dưới dạng tệp PDF ở đầu trang này.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: This page covers only the early in-hospital phase of recovery after a shoulder replacement — the first days on the ward and the principles of the first protected weeks — for anatomic total shoulder arthroplasty (TSA), reverse total shoulder arthroplasty (RSA), and shoulder replacement performed for a proximal-humerus fracture. The companion patient page (the synthesis) lists the actual in-hospital exercises and sling rules; this page sets out the evidence behind them. The full course of rehabilitation for each operation lives in its own protocol — follow that one once you are home: total shoulder replacement, reverse shoulder replacement, and shoulder replacement for fracture, each of which carries its own detailed evidence page.
Defining principle of the early phase: the two pathways now differ. A reverse replacement is run on an accelerated, permissive footing, while an anatomic total replacement (and a replacement for a fracture) remains protective. In every case the hand/wrist/elbow are kept active from the start, but what the shoulder itself is allowed to do — and what is being protected — differs by operation:
- Anatomic TSA protects the subscapularis repair. To put the ball-and-socket implant in, the surgeon detaches and re-attaches the subscapularis tendon (or its bone block) at the front of the shoulder. Early external rotation is limited, active and resisted internal rotation is delayed, and shoulder elevation is kept passive/assisted — because these are the positions that strain the healing repair. This is why the in-hospital ER exercise only moves the arm from the sling position to pointing straight ahead — and no further. The sling is worn full-time for about 6 weeks.
- Reverse TSA is accelerated. Often there is no subscapularis repair to protect, and the deltoid (not the cuff) powers the arm, so the shoulder can move early. The sling is for comfort and support only (~2 weeks), and active-assisted and active-as-tolerated shoulder motion begins from the start (supine/gravity-assisted first), within comfort. The main early constraint is dislocation precautions, whose at-risk position is hand-behind-the-back (combined extension + adduction + internal rotation): avoid reaching the arm behind the body or behind the back, no lifting, and no pushing up through the hands. This aligns with the accelerated reverse literature (see the reverse protocol's evidence page).
- Replacement for fracture adds a third constraint: the tuberosities (the bony muscle attachments) must heal, so this pathway follows the protective line (like anatomic TSA) and is usually the most protective of the three.
Common to all three: the hand/wrist/elbow are kept active immediately, and adequate analgesia makes early gentle motion possible. The sling duration and how freely the shoulder moves then differ — permissive for reverse, guarded for anatomic and fracture.
The early in-hospital phase, in brief
Most patients stay in hospital a short time after a shoulder replacement — commonly about one to two nights, and selected patients are now safely discharged the same day. Before discharge the ward physiotherapist fits the sling, teaches independent sling management, and starts the gentle exercises shown in the synthesis: keeping the hand, wrist and elbow active; pendulums; and shoulder elevation — assisted (passive) and limited in external rotation after an anatomic repair, but active-assisted and active-as-tolerated from the start after a reverse replacement. The arm is commonly numb from a nerve block when you wake, with sensation returning over roughly 24 hours. The job of this phase is pain control, swelling reduction, keeping the non-shoulder joints moving, and protecting the new joint while it settles — not building strength, which comes later in the home protocol.
Evidence by theme
1. Length of stay is short, and same-day discharge appears safe in selected patients
Shoulder replacement has traditionally been an inpatient operation, but length of stay is short and falling. At an orthopaedic specialty hospital the average stay was about 1.3 days versus ~1.85 days at a general centre [RAG corpus — 10.1016/j.jse.2016.01.010]. A large series found same-day discharge was not inferior to a longer in-hospital stay for 90-day readmissions [RAG corpus — 10.1016/j.jse.2019.09.037], and outpatient TSA in an ambulatory centre was reported as a safe alternative to inpatient care in a matched cohort (2016 Neer Award) [RAG corpus — 10.1016/j.jse.2016.07.011]. Same-day discharge appears safe even in patients aged ≥65 with appropriate selection [RAG corpus — 10.1016/j.jse.2021.02.022]. Whether you stay one night or go home the same day is an individual decision; the early-exercise and sling principles are the same either way.
Evidence: MODERATE (cohort / matched-cohort data).
2. Pain control is the patient's and the system's primary early concern
When patients consider shorter stays, perioperative pain control is their primary concern [RAG corpus — 10.1016/j.jse.2022.07.009] — which is why the synthesis emphasises taking analgesia before exercises and physiotherapy. Adequate pain relief is also what makes early gentle motion possible. A regional nerve block is commonly used, explaining the early numbness that recovers over about a day.
Evidence: MODERATE (survey / practice data).
3. Early motion depends on the operation — accelerated for reverse, guarded for anatomic
The ward starts active hand/wrist/elbow motion immediately after every replacement. What the shoulder is allowed to do then splits by operation. For reverse replacement the conservative-versus-early question has been tested directly: randomised trials show that earlier motion and shorter (or even no) immobilisation do not increase dislocation or complications, including a 3-week-versus-no-immobilisation RCT in primary RSA [RAG corpus — 10.1016/j.jse.2025.02.015], and home-based physiotherapy matched formal outpatient therapy after RSA [RAG corpus — 10.1016/j.jse.2023.03.023]. Dr Hirpara's reverse pathway now follows this accelerated line: a short (~2-week) comfort sling, and active-assisted and active-as-tolerated shoulder motion (supine/gravity-assisted first) from the start, within comfort — with dislocation precautions (no arm behind the body, no lifting, no pushing through the hands) the main early constraint. By contrast, anatomic TSA and replacement for fracture keep the protective early line — passive/assisted elevation only, no active shoulder lifting, and the front-of-shoulder repair (or the tuberosities) guarded — because there is a repair that the reverse construct does not have.
Evidence: MODERATE–STRONG for RSA early motion (RCTs), which the reverse pathway now reflects; the specific in-hospital timings are consensus/surgeon preference.
4. Why external rotation is limited after anatomic TSA but freer after reverse
In anatomic TSA the subscapularis must be detached to seat the implant and then repaired, and external rotation (especially with the arm out to the side) puts the greatest strain on that repair — so early ER is restricted while forward elevation and scaption, which do not load the repair, are allowed sooner [literature — Brigham & Women's Faulkner TSA guideline; subscapularis management review]. Typical published protocols cap early external rotation at around 20–30° and release it at about 6 weeks; the synthesis applies this by moving the arm only from the sling position to "pointing straight ahead." After reverse replacement there is usually no subscapularis repair to protect, so ER is more permissive and the dominant precaution is instead the hand-behind-the-back dislocation position [parent reverse protocol — RAG corpus 10.1016/j.jse.2016.12.073; 10.1016/j.jse.2020.05.019].
Evidence: MODERATE (biomechanical + protocol consensus); no single defining rehab RCT for the early in-hospital window.
Phased timeline — the early phase only
This focuses on the in-hospital and immediately-post-discharge window. The complete multi-phase course (intermediate, transitional, advanced strengthening, return to sport) lives in each parent protocol; the rows below are intentionally consistent with the Phase I content of those pages.
| Phase | Window | Sling | Shoulder motion | Operation-specific note |
|---|---|---|---|---|
| In hospital | Days 0–2 | Reverse: comfort/support. Anatomic + fracture: worn incl. overnight | Active hand/wrist/elbow (all); pendulums. Reverse: active-assisted + active-as-tolerated from the start (supine/gravity-assisted first). Anatomic + fracture: passive/assisted elevation, limited assisted ER | Ward physio fits sling, teaches management, starts the synthesis exercises before discharge |
| Early protection | Weeks 0–3 | Reverse: ~2 weeks for comfort. Anatomic + fracture: full-time (worn overnight) | Reverse: continue active-assisted/active motion within comfort; dislocation precautions (no arm behind body, no lifting, no pushing through hands). Anatomic TSA: passive/assisted only, no active lifting, ER limited (sling-to-straight-ahead), IR delayed. Fracture: most protective | Pain + swelling control; keep adjacent joints moving |
After this early window, follow the full protocol for your specific operation (linked above), where the sling is weaned, active motion is progressed, and strengthening begins.
Key controversies / evidence quality
- Inpatient vs same-day discharge. Cohort evidence supports same-day discharge in selected patients, but selection matters and pain control is the limiting factor; whether you stay overnight is a clinical judgement, not a fixed rule. Moderate.
- How protective to be early. Randomised data (strongest for reverse) show early motion and shorter immobilisation are safe. The reverse pathway now applies this accelerated approach (short comfort sling, early active-assisted/active motion, dislocation precautions). The anatomic pathway stays protective because it has a subscapularis repair to guard — there the protective early phase is a deliberate surgeon clinical decision, not an oversight relative to the accelerated literature. Moderate–strong evidence; applied per operation.
- The in-hospital protocol itself is consensus/expert. The specific early exercises and ROM limits are drawn from published institutional protocols and surgeon guidance, not from a rehab RCT of the in-hospital window. Weak/consensus.
Evidence-strength flags (summary)
- MODERATE (cohort): short length of stay; same-day discharge non-inferior for readmissions and safe in selected and older patients; pain control as the primary patient concern.
- MODERATE–STRONG (RCT, mainly reverse): early motion / shorter immobilisation safe after RSA; home-based PT equivalent to formal outpatient PT after RSA.
- MODERATE (biomechanical + protocol consensus): ER restriction protects the subscapularis repair in anatomic TSA; reverse rehab more permissive in ER but constrained by the dislocation position.
- WEAK / CONSENSUS: the specific in-hospital exercise set and early-phase timings (institutional protocols + surgeon preference; no defining rehab RCT of the inpatient window).
Citations
RAG corpus (180,000+ Orthopaedic articles) — real DOIs returned by search
- Length of stay after shoulder arthroplasty — the effect of an orthopedic specialty hospital. J Shoulder Elbow Surg. 2016. DOI: 10.1016/j.jse.2016.01.010
- Same-day discharge is not inferior to longer length of in-hospital stay for 90-day readmissions following shoulder arthroplasty. J Shoulder Elbow Surg. 2020. DOI: 10.1016/j.jse.2019.09.037
- Outpatient total shoulder arthroplasty in an ambulatory surgery center is a safe alternative to inpatient total shoulder arthroplasty in a hospital: a matched cohort study (2016 Neer Award). J Shoulder Elbow Surg. 2016. DOI: 10.1016/j.jse.2016.07.011
- Is outpatient shoulder arthroplasty safe in patients aged ≥65 years? A comparison of readmissions and complications in inpatient and outpatient settings. J Shoulder Elbow Surg. 2021. DOI: 10.1016/j.jse.2021.02.022
- Perioperative pain control represents the primary concern for patients considering outpatient shoulder arthroplasty: a survey-based study. J Shoulder Elbow Surg. 2022. DOI: 10.1016/j.jse.2022.07.009
- Three-week immobilization vs. no immobilization in primary reverse total shoulder arthroplasty: a randomized controlled trial. J Shoulder Elbow Surg. 2025. DOI: 10.1016/j.jse.2025.02.015
- Home-based physical therapy results in similar outcomes to formal outpatient physical therapy after reverse total shoulder arthroplasty: a randomized controlled trial. J Shoulder Elbow Surg. 2023. DOI: 10.1016/j.jse.2023.03.023
- The American Society of Shoulder and Elbow Therapists' consensus statement on rehabilitation for anatomic total shoulder arthroplasty. J Shoulder Elbow Surg. 2020. DOI: 10.1016/j.jse.2020.05.019
- Dislocation following reverse total shoulder arthroplasty. J Shoulder Elbow Surg. 2017. DOI: 10.1016/j.jse.2016.12.073
Literature (URLs)
- The effect of subscapularis-specific rehabilitation following total shoulder arthroplasty: a prospective, double-blinded, randomized controlled trial. J Hand Ther / ScienceDirect. 2023. https://pubmed.ncbi.nlm.nih.gov/37263480/
- Management of the subscapularis tendon during total shoulder arthroplasty (early ER strains the repair most). J Hand Ther / ScienceDirect. 2016. https://www.sciencedirect.com/science/article/abs/pii/S1058274616305791
Published rehabilitation protocols (basis for the early-phase structure)
- Brigham & Women's Faulkner Hospital — Department of Rehabilitation Services: Total Shoulder Arthroplasty Guideline (early ER restriction to protect the subscapularis repair). https://www.brighamandwomensfaulkner.org/assets/BWH/patients-and-families/rehabilitation-services/pdfs/total-shoulder-arthroplasty-guideline.pdf
- Massachusetts General Brigham Sports Medicine — Rehabilitation Protocol for Total Shoulder Arthroplasty and Hemiarthroplasty (Revised December 2018). https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-total-shoulder-arthroplasty-and-hemi.pdf
- Massachusetts General Brigham Sports Medicine — Rehabilitation Protocol for Reverse Shoulder Arthroplasty (Revised December 2018). https://www.massgeneral.org/assets/mgh/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-reverse-shoulder-arthroplasty.pdf





