

肩锁关节稳定 资料
本方案涵盖在 Mater Private Hospital Rockhampton 由 Kieran Hirpara 医生进行肩锁(AC)关节固定术后的康复。该手术旨在通过悬吊装置(有时辅以肌腱移植物加固)恢复锁骨与肩胛骨之间关节在脱位后的对位。请携带本页面或其 PDF 文件至首次物理治疗就诊,以确保您的康复过程协调一致。您的物理治疗师将根据肩部恢复情况,通过以下阶段为您个体化地推进康复进程。
如果您对术后伤口有任何疑虑,请联系诊所。通常,拍摄伤口照片并发送电子邮件以供审阅会很有帮助。
预期情况
肩锁关节稳定术与大多数肩关节关节镜手术不同:存在一个需要在愈合期间加以保护的修复部位,而对其施加最大负荷的因素仅仅是您手臂自身的重量。重力持续将手臂(以及随之联动的肩胛骨)向下拉,使其远离锁骨,而这正是稳定术必须抵抗的方向。因此,早期康复是刻意采取保护性措施的:吊带承担手臂的重量,活动被限制在安全范围内,强化训练则需等待修复部位成熟后进行。
吊带具有保护作用。请佩戴6周,并在最初的三周内睡觉时也保持佩戴,因为即使平躺,手臂的重量也会牵拉修复部位。三周后,睡觉时可以取下吊带。在取下吊带进行洗漱或锻炼时,请保持手臂支撑:将前臂放在枕头或桌面上,而不是让手臂悬垂或提拿任何物品。夜间,大多数人仰卧或侧卧于非手术侧时最为舒适;如果您仰卧,在肘部和前臂下方垫一个小枕头可防止肩关节向后下垂。在修复部位愈合期间,避免侧卧于手术侧。
任何肩部手术后六周内严禁驾驶,佩戴吊带期间亦严禁驾驶。
您的锻炼计划包含三种类型的运动,您的医疗团队会标注哪些适用于您:
- 主动活动范围: 允许在无辅助或帮助的情况下进行运动。
- 主动辅助活动范围: 使用另一只手臂或物体辅助移动手臂。
- 被动活动范围: 完全放松,由另一只手臂或外力完成100%的工作。
康复历程概览:
- 第一阶段:保护修复部位, 第0–6周
- 第二阶段:恢复活动度, 第6–12周
- 第三阶段:强化训练, 第12–18周
- 第四阶段:重返运动和高强度工作, 第18周起
周数范围是典型值而非固定值;该手术已发表的方案存在差异,您的物理治疗师将根据修复部位和活动度的恢复情况推进您的康复进程,而非依据日历。大多数人约在三个月时即可使用手臂进行正常的日常活动。重返对抗性和碰撞性运动通常需要四到六个月,对于某些运动和职业,渐进恢复过程可能更长。
第一阶段 — 保护修复(第 0–6 周)

Kieran Hirpara 4.0
钟摆运动
将手臂从悬吊带中取出,腰部前屈,让手术侧手臂自然下垂并远离身体。让手臂做小而放松的圆周摆动——动作应源自躯干,而非肩部肌肉。保持在舒适范围内,然后将手臂重新支撑回悬吊带中。
每天数次

Kieran Hirpara 4.0
肩胛骨位置
坐姿或站姿保持挺拔,手臂得到支撑,轻轻将肩胛骨向后、向下收拢,使其远离耳部。保持数秒,然后放松。这能让姿势肌群保持活动,同时避免对修复部位施加负荷。
在您的物理治疗师指导下

Kieran Hirpara 4.0
手部及握力练习
手臂用吊带支撑,握紧拳头,然后将手指伸直张开。可挤压软球或卷起的袜子进行抓握训练。从第一天起,保持手、腕和肘部的活动。
在您的物理治疗师指导下
Kieran Hirpara 4.0
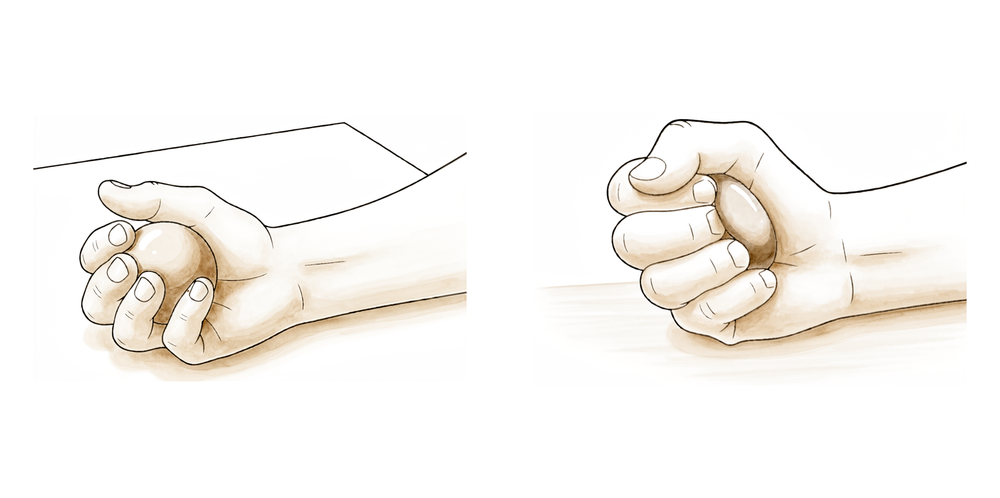
握球
手臂用吊带支撑时,手握软球或卷起的袜子并用力挤压,然后松开。这能在保护肩关节的同时,保持握力和前臂的活动。
在您的物理治疗师指导下

Kieran Hirpara 4.0
腕部运动
将手臂从悬吊带中取出并支撑前臂,向前、向后及左右方向弯曲手腕。从第一天起保持手腕活动,可在保护修复部位的同时防止其僵硬。
在您的物理治疗师指导下

Kieran Hirpara 4.0
肘部弯曲
上臂由身体一侧支撑,将肘关节弯曲至舒适的最大角度,然后完全伸直。仅肘关节活动——保持肩部放松并得到支撑,以免对修复部位产生负荷。
在您的物理治疗师指导下

Kieran Hirpara 4.0
前臂旋转
将肘部贴于体侧并屈曲至直角,掌心向上转向天花板,再向下转向地面。前臂旋转,而肩部保持静止并得到支撑。
在您的物理治疗师指导下

Kieran Hirpara 4.0
使用棍棒辅助外旋
仰卧,将手术侧肘部贴于体侧并屈曲成直角。双手握住一根棍棒,让健侧手臂轻轻带动患侧前臂向外旋转,仅在此阶段舒适允许的范围内进行。缓慢复位,并保持动作幅度小且有支撑。
在您的物理治疗师指导下
Kieran Hirpara 4.0
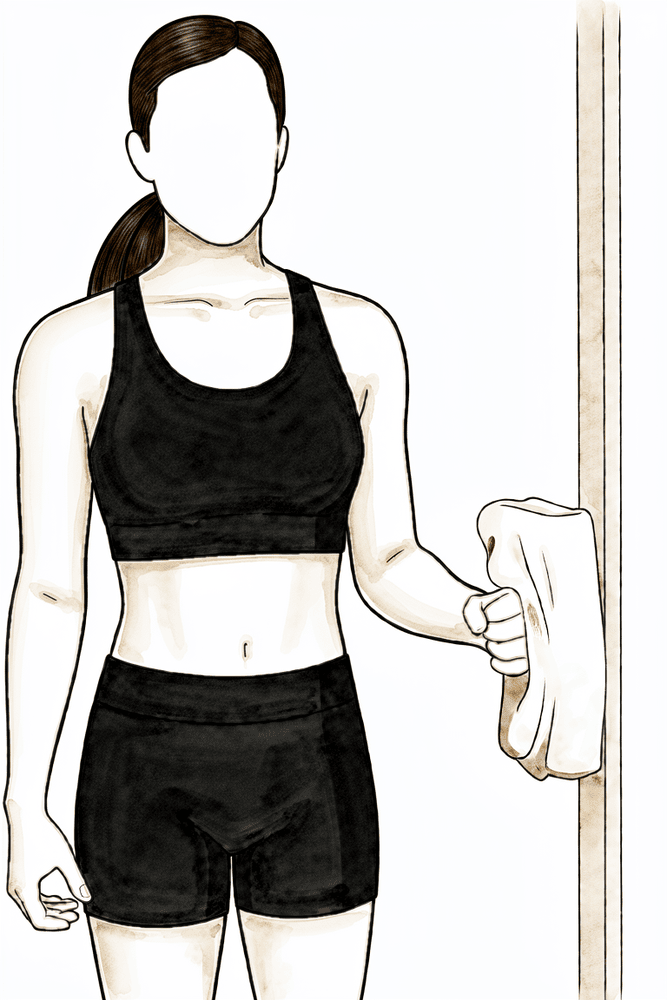
等长外旋
将肘部贴紧体侧并屈曲成直角,手背抵住墙壁或门框。轻轻向外推压,保持手臂不动,维持数秒,然后放松。肩部发力但关节不产生位移,因此修复部位未承受负荷。
亚最大强度且无痛;以您的物理治疗师指导为准
Kieran Hirpara 4.0
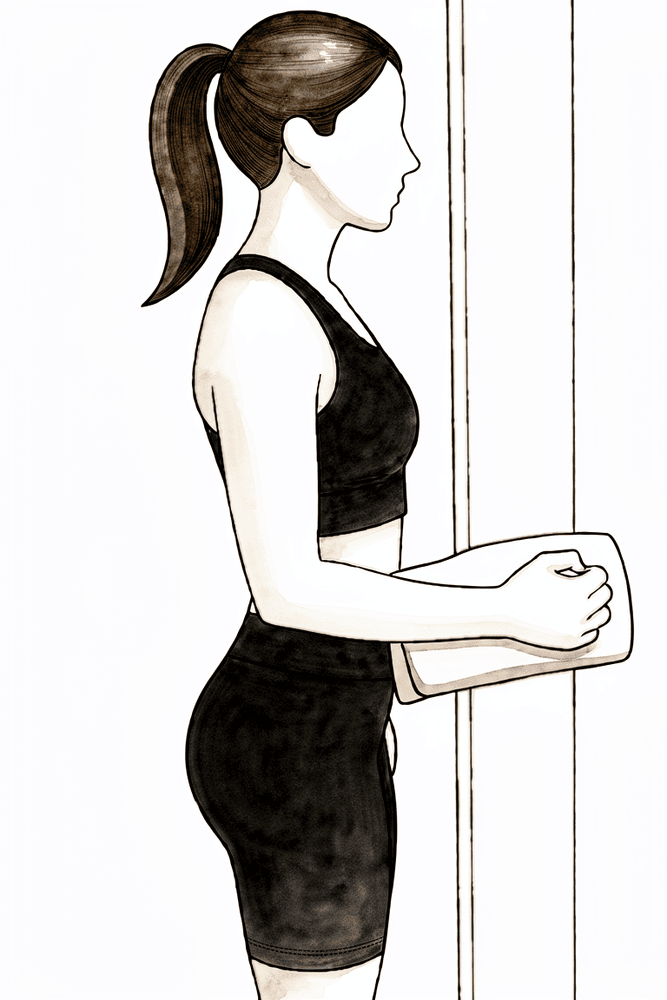
等长内旋
将肘部贴紧体侧并屈曲成直角,手掌抵住墙壁或门框。轻轻向内推压,同时保持手臂不动,保持数秒,然后放松。这是一种在早期保持肩袖肌群活动性的无运动方式。
亚最大强度且无痛;以您的物理治疗师指导为准
最初六周的重点是让修复部位愈合,同时保持手臂其余部分的运动。当您起身活动时,吊带需承担手臂的重量。从第一天起,您的手、手腕和肘部应保持活动:在手臂佩戴吊带时,可使用手进行书写和进食等轻度任务。肩关节本身从轻柔的钟摆运动和严格限制范围内的辅助运动开始:任何动作均不得高于肩部高度,不得跨越身体,也不得向后背伸手。冰敷和规律止痛可使运动变得可行。请在运动和物理治疗课程前服用止痛药。一旦伤口护理建议允许,您即可淋浴;为清洗手术侧手臂下方,请弯腰前倾,让手臂自然轻柔地远离身体,该姿势与钟摆运动相同。
在此阶段,请勿用手术侧手臂提起超过约半公斤的重物,不要在该侧提包,不要倚靠手臂或用手臂支撑自己从床或椅子上起身,也不要让手臂在无支撑状态下悬垂:上述每种情况都会使肩胛骨向下远离锁骨,从而对修复部位施加负荷。
致您的物理治疗师:
目标
- 保护手术稳定结构并允许软组织愈合
- 控制疼痛和肿胀;保护伤口愈合
- 在保护范围内预防肩关节僵硬
- 维持手、腕、肘和颈部的活动范围
管理
- 起身活动时佩戴吊带6周;吊带取下时手臂需有支撑
- 每日多次进行钟摆运动
- 在肩胛骨平面内进行被动和主动辅助上举,限制在90度以内
- 在舒适范围内进行被动和主动辅助外旋(初始约为30度)
- 手、腕、肘和前臂的主动活动范围训练;握球练习
- 肩胛骨定位(后缩和下沉)及姿势矫正
- 在中立位进行亚最大、无痛的等长内旋和外旋,以耐受程度为准
- 根据需要进行软组织和肩胸关节松动术;伤口愈合后进行瘢痕按摩
- 冰敷 15–20 分钟,每日多次,按需进行;运动和课程前给予镇痛
注意事项
- 不要让手臂重量牵拉固定装置:手臂不得悬垂,不得提物,不得向下牵拉
- 任何平面内上举不得超过90度
- 不得进行超出规定辅助计划的主动肩关节活动范围训练
- 不得进行跨身体(水平)内收,也不得在背后进行内旋
- 不得提起超过约半公斤的重物;不得通过手臂支撑体重
- 六周内不得驾驶(此规定适用于任何肩部手术),佩戴吊带期间亦不得驾驶
晋级标准
- 在肩胛骨平面内被动屈曲约90度
- 在肩胛骨平面内被动外旋约30度
- 耐受活动范围和等长训练计划,且疼痛和肿胀趋于稳定
第二阶段 — 恢复活动度(第 6–12 周)
Kieran Hirpara 4.0
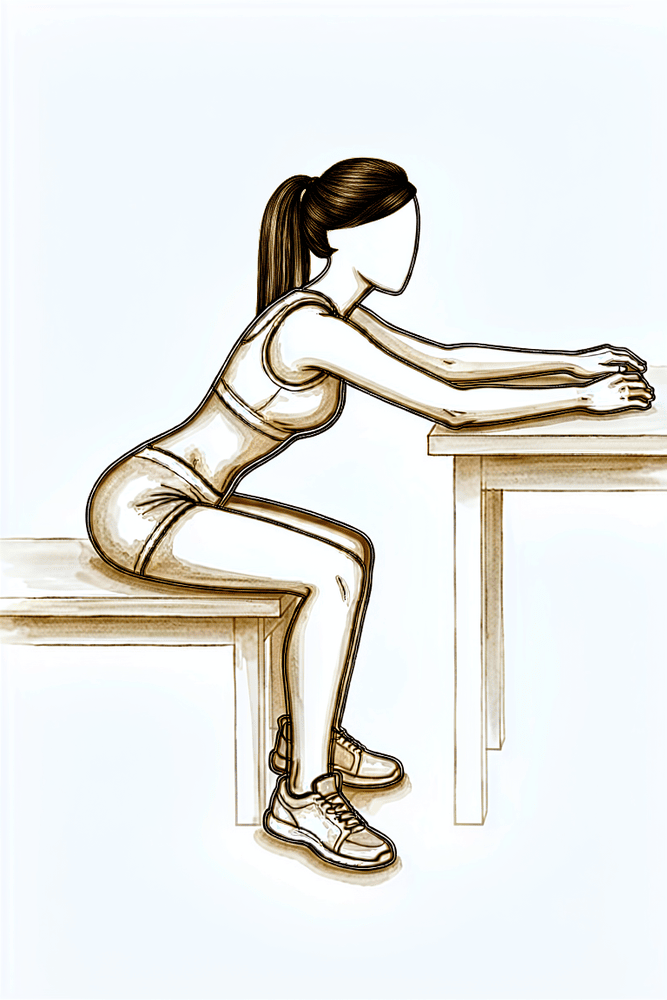
台面滑动
坐在桌子或长凳前,双手平放在台面上。将双手向前滑动,同时躯干前倾,使肩部在支撑下向上弯曲,然后返回。在舒适范围内平滑移动,避免将肩部向耳朵方向耸起。
在您的物理治疗师指导下
Kieran Hirpara 4.0
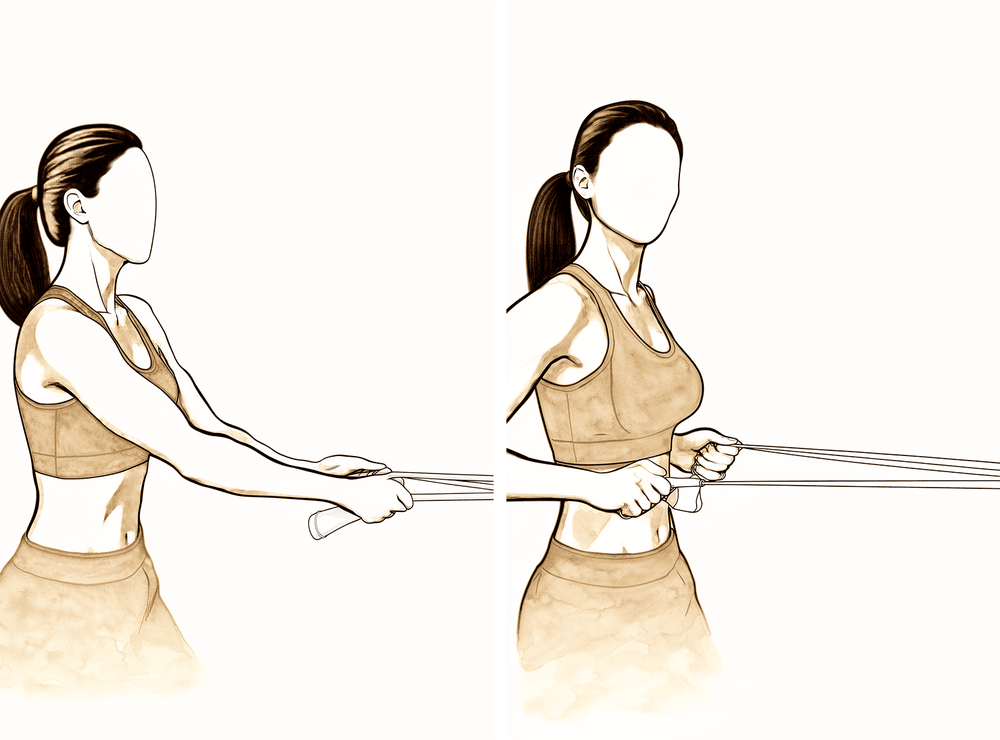
弹力带划船
将弹性阻力带固定在身前,高度约在腰部。将阻力带向身体方向拉动,当肘部经过身体侧方时,使肩胛骨向后、向下移动,然后有控制地回到起始位置。在此阶段,保持阻力较轻。
在您的物理治疗师指导下
Kieran Hirpara 4.0
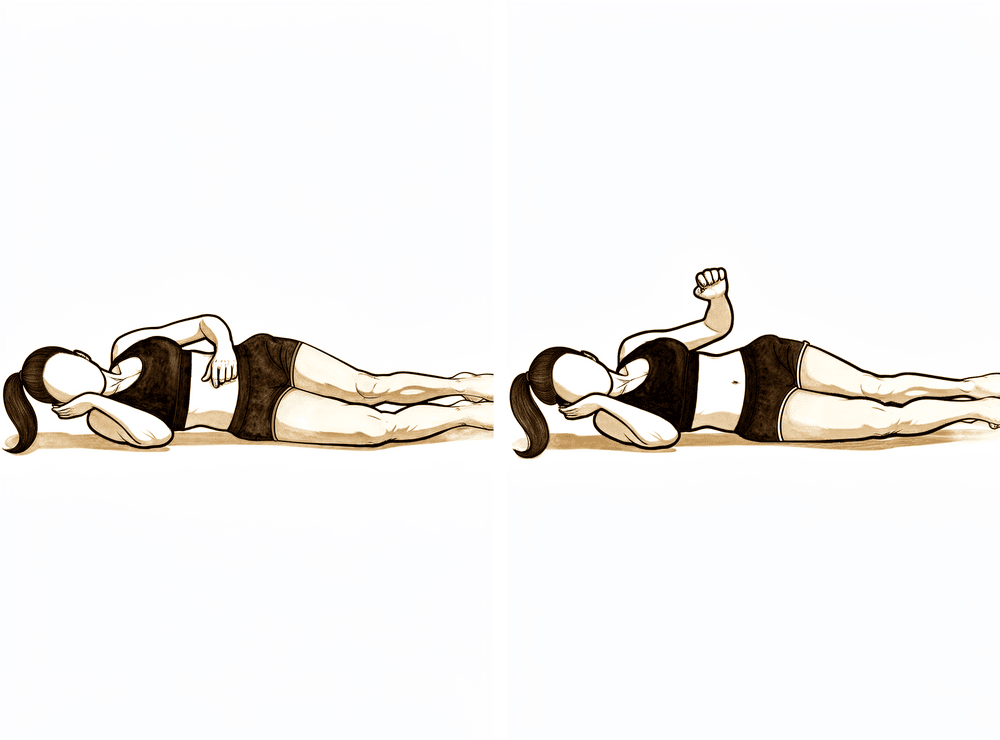
侧卧位外旋
侧卧于非手术侧,上方肘关节屈曲成直角并紧贴身体。保持肘部位于体侧,将前臂向上旋转朝向天花板,然后有控制地放下。此阶段不负重——负重将在后续阶段根据指导添加。
在您的物理治疗师指导下
Kieran Hirpara 4.0
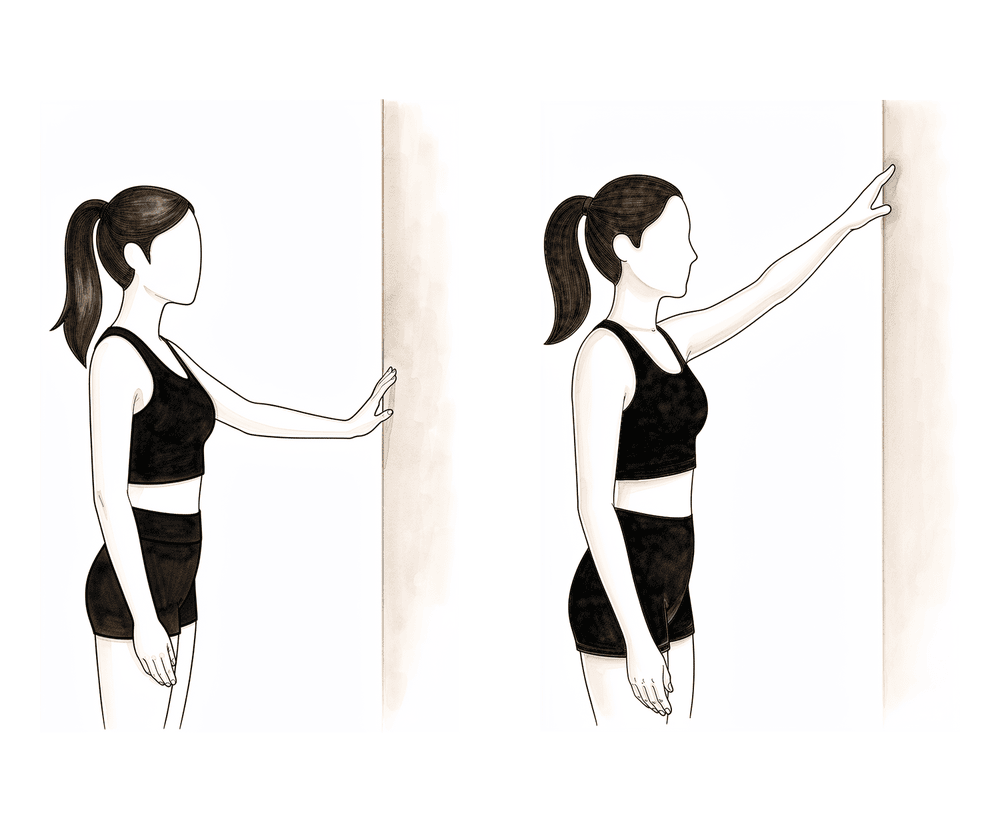
墙指行走
面对墙壁站立,将手术侧手的手指置于墙上。让手指沿墙面缓慢向上移动,随着肩部上抬,使手指承担部分手臂重量,然后沿墙面缓慢向下移动。保持肩胛骨放松——不要向耳朵方向耸肩。
在您的物理治疗师指导下
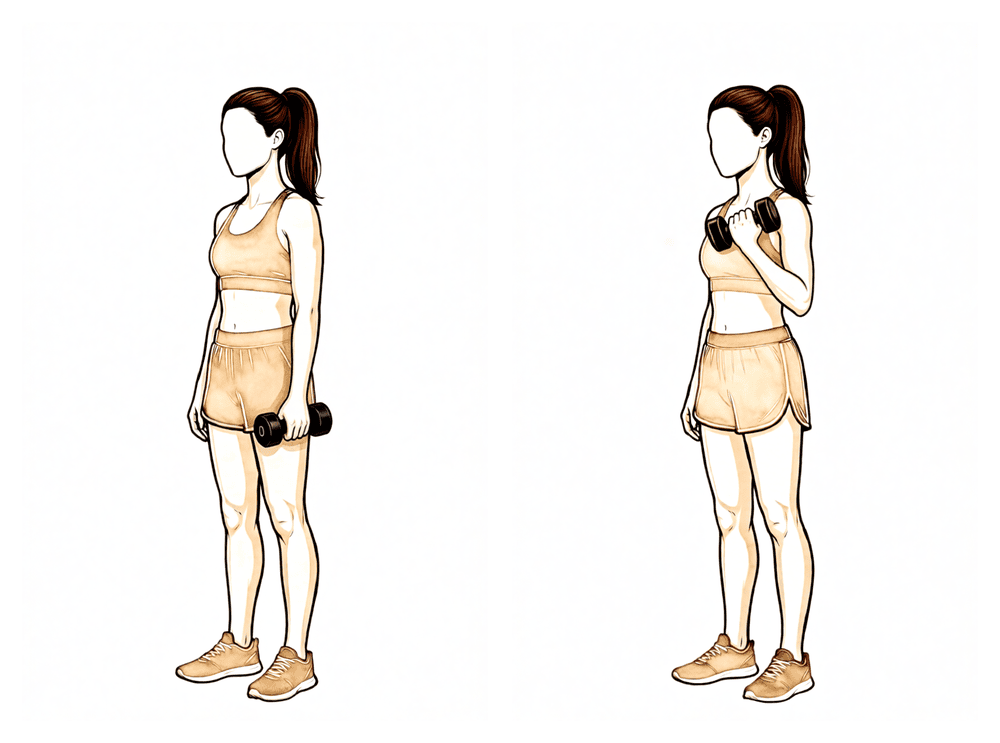
Kieran Hirpara 4.0
肱二头肌弯举
上臂贴于体侧,屈肘将轻重量物向上弯举至肩部,然后缓慢放下。在此阶段,请保持负荷较轻——这有助于在不牵拉修复部位的情况下重建手臂功能。
在您的物理治疗师指导下
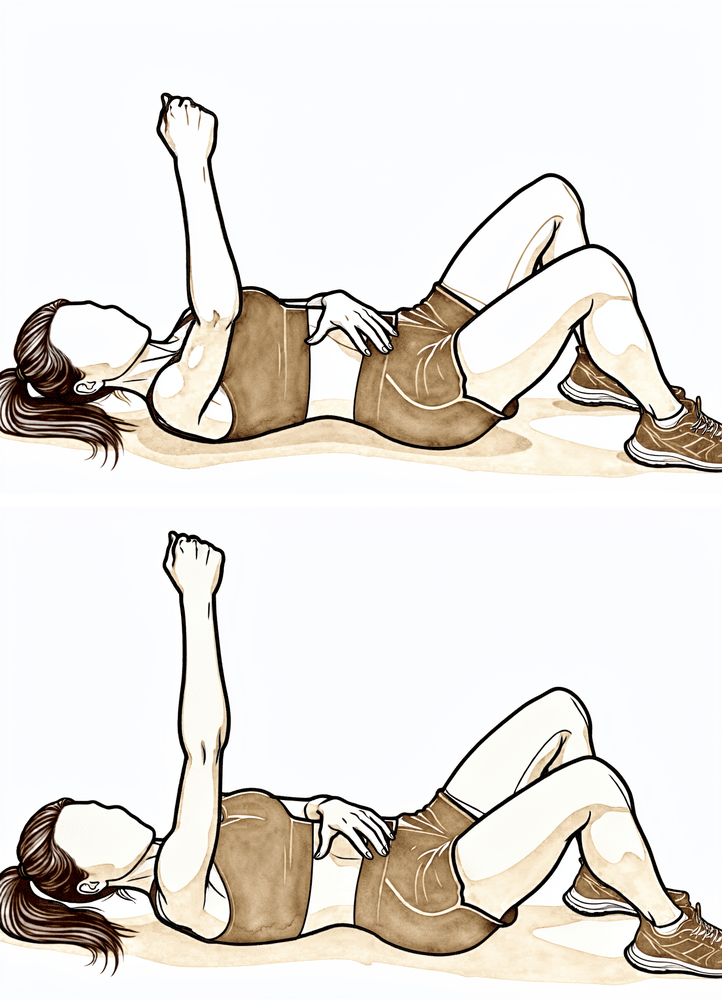
Kieran Hirpara 4.0
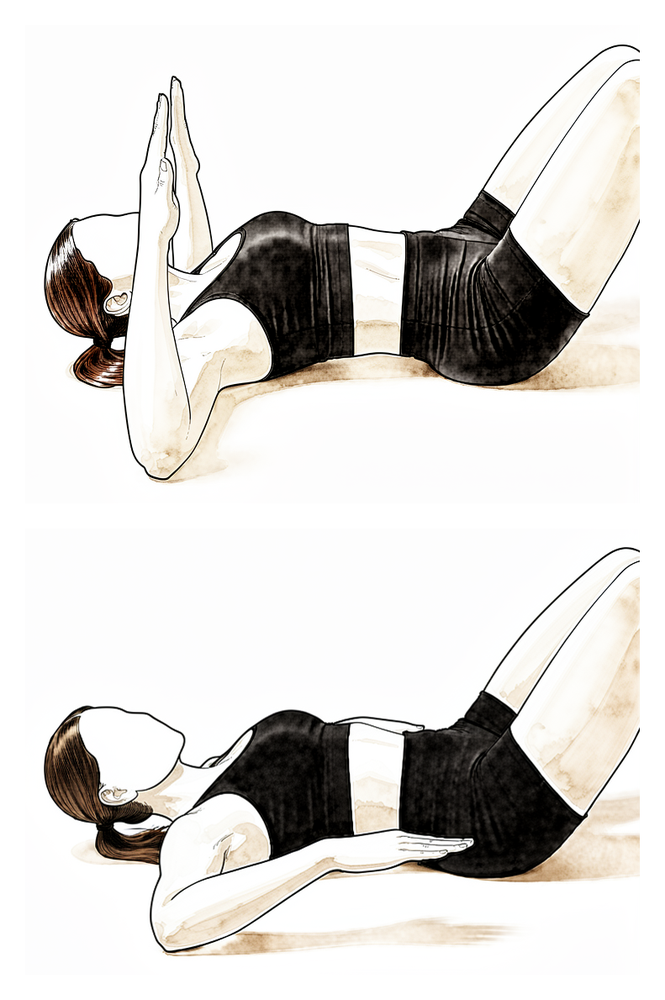
前锯肌推拳
仰卧,手术侧手臂向上指向天花板。在不弯曲肘关节的情况下,将拳头再向上伸展一点,使肩胛骨离开床面,然后有控制地放下。此动作可激活将肩胛骨固定在肋骨上的肌肉。
在您的物理治疗师指导下

Kieran Hirpara 4.0
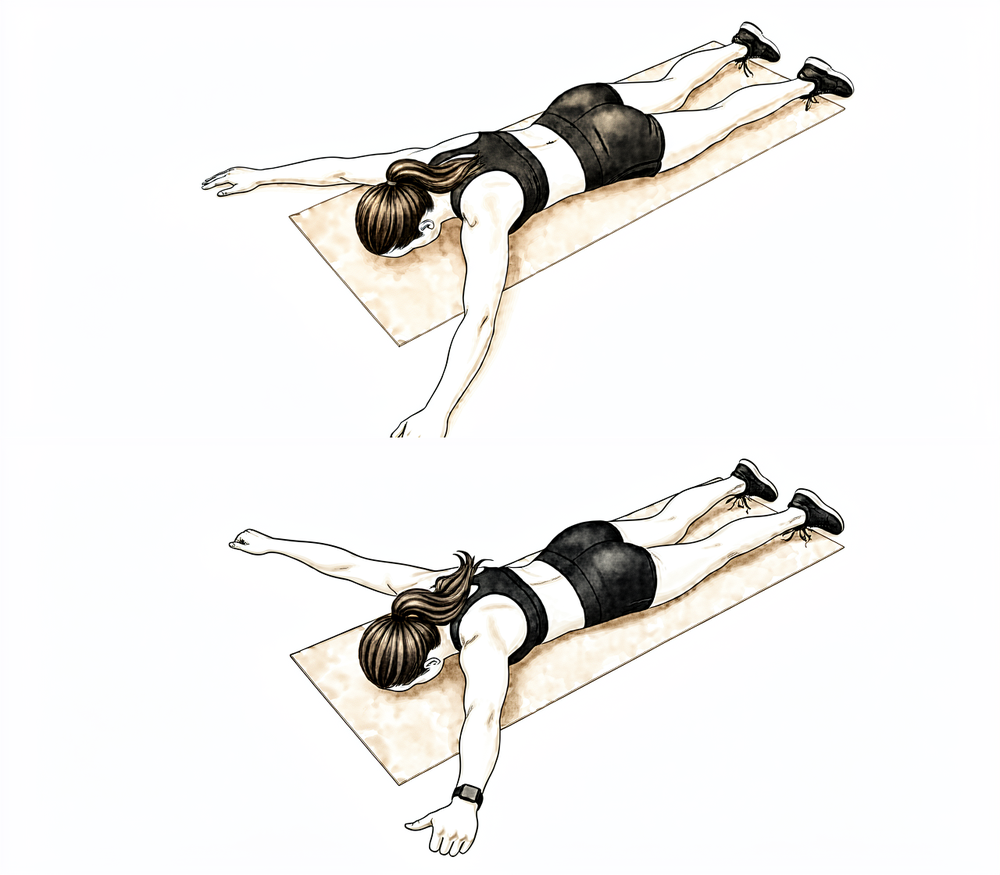
俯卧位 T 字
俯卧,双臂自然下垂指向地面。将肩胛骨相互挤压靠拢,然后将手术侧手臂向侧方抬起至“T”字形,随后缓慢放下。动作宜轻柔——此动作旨在锻炼肩胛骨肌肉,避免对关节施加过大负荷。
在您的物理治疗师指导下
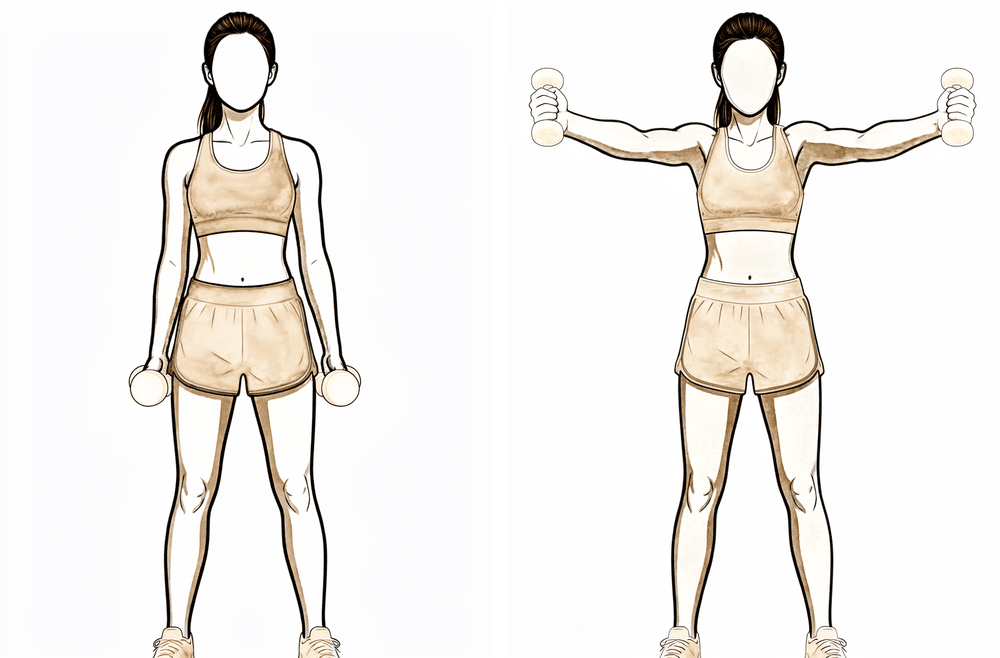
Kieran Hirpara 4.0
站立位肩胛平面上举
手臂置于体侧,拇指朝上站立。将手臂向前方角度抬起,位置介于正前方与侧方之间,高度不超过舒适范围,然后缓慢放下。保持肩胛骨稳定,避免耸肩。
在您的物理治疗师指导下
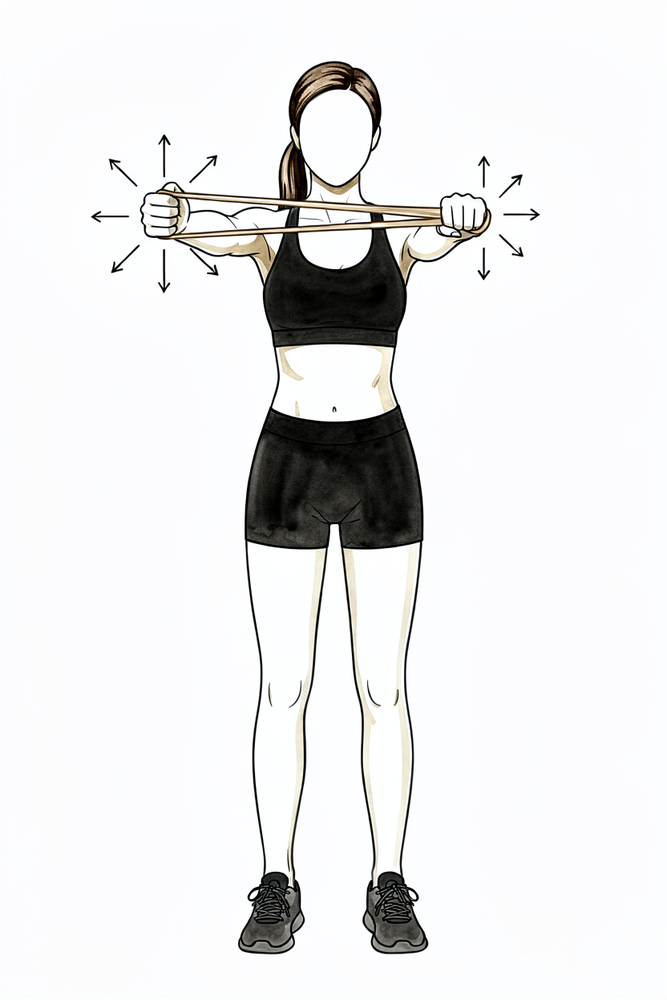
Kieran Hirpara 4.0
节律性稳定
将手臂支撑在身体前方,高度约与肩部齐平,请您的物理治疗师(或您的健侧手)从不同方向施加小而轻柔的推力,同时您保持手臂静止且稳定——不要让其移动。这旨在训练肩部稳定肌群的反应能力。所有动作力度均需保持轻柔。
在您的物理治疗师指导下
大约从第六周开始,您需逐渐停止使用吊带,并逐步解除对活动度的限制。辅助性动作转变为主动性动作,活动范围稳步增加;作为参考,已发表的康复方案通常每周以约15度的幅度增加活动范围,目标是在第12周左右恢复完全的活动度。此阶段开始进行针对肩袖和肩胛骨肌肉的轻阻力弹力带练习。修复部位仍需注意保护:提举重量限制在约1公斤以内,避免用力推、拉、做俯卧撑,以及跨身体或过头提举物体。向后背伸手通常是最后恢复的活动动作。
致您的物理治疗师:
目标
- 逐步停用吊带
- 逐步恢复各平面的主动活动范围(在第12周左右达到完全或接近完全)
- 开始温和的力量训练;最大限度减少肌肉萎缩
- 重建肩肱节律和神经肌肉控制
管理措施
- 从主动辅助上举进展至主动上举;通过墙壁滑动和台面滑动进行屈曲训练
- 在肩胛骨平面进行上举,注意肩胛骨力学机制:避免肩胛骨上提(hitching)
- 逐步引入背后内旋(初始阶段至腰带水平)
- 水平内收仅作为主动伸展动作:暂不进行被动拉伸
- 弹力带内旋和外旋、肱二头肌弯举、划船和锯肌推击
- 动态肩胛骨和肩袖训练:侧卧外旋、俯卧划船、俯卧伸展、俯卧“T”字和“Y”字、站立肩胛骨上举
- 本体感觉和节律稳定训练
- 根据需要进行手法治疗和关节松动术
注意事项
- 手术侧手臂提举重量不得超过约1公斤
- 禁止用力推或拉;禁止做俯卧撑
- 禁止过头或跨身体提举重物
- 避免在跨身体内收的终末位置进行拉伸;背后动作需逐步进展
进展标准
- 肩胛骨平面被动屈曲至少约140度,被动外旋至少约60度
- 抗重力主动屈曲至少约100度,且力学机制良好
- 能够耐受主动活动范围训练和早期力量训练方案
第三阶段 — 强化训练(第 12–18 周)
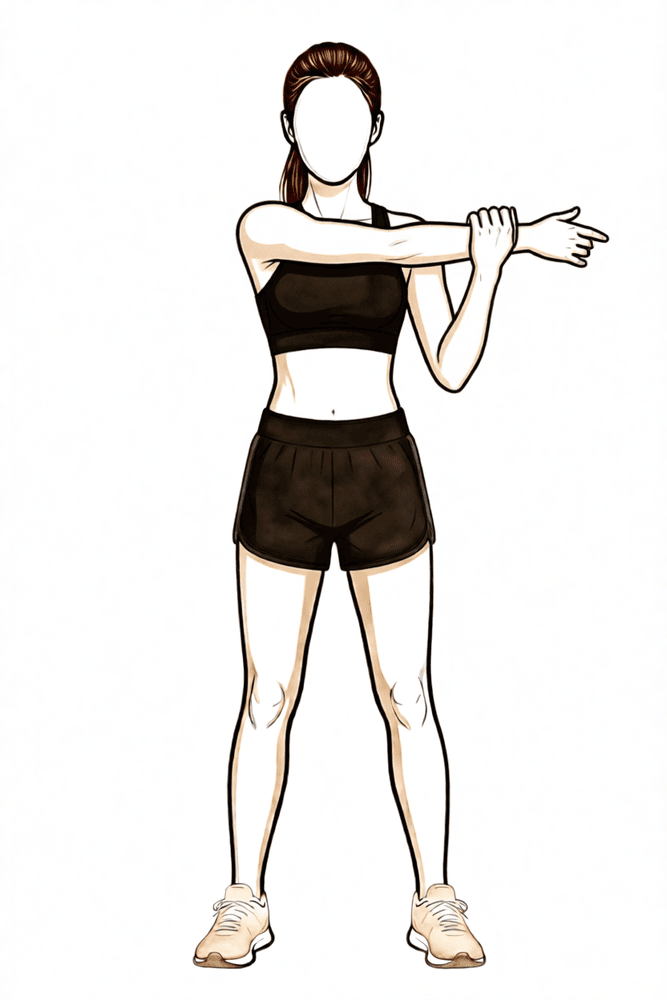
Kieran Hirpara 4.0
跨体拉伸
将手术侧手臂横过胸前,用另一只手置于肘关节上方,轻轻将其进一步拉向对侧,直至感到肩后部有牵拉感。保持该姿势片刻,然后放松。此前禁止进行的这一牵拉动作,现用于争取关节活动度的最后几个角度。
在您的物理治疗师指导下
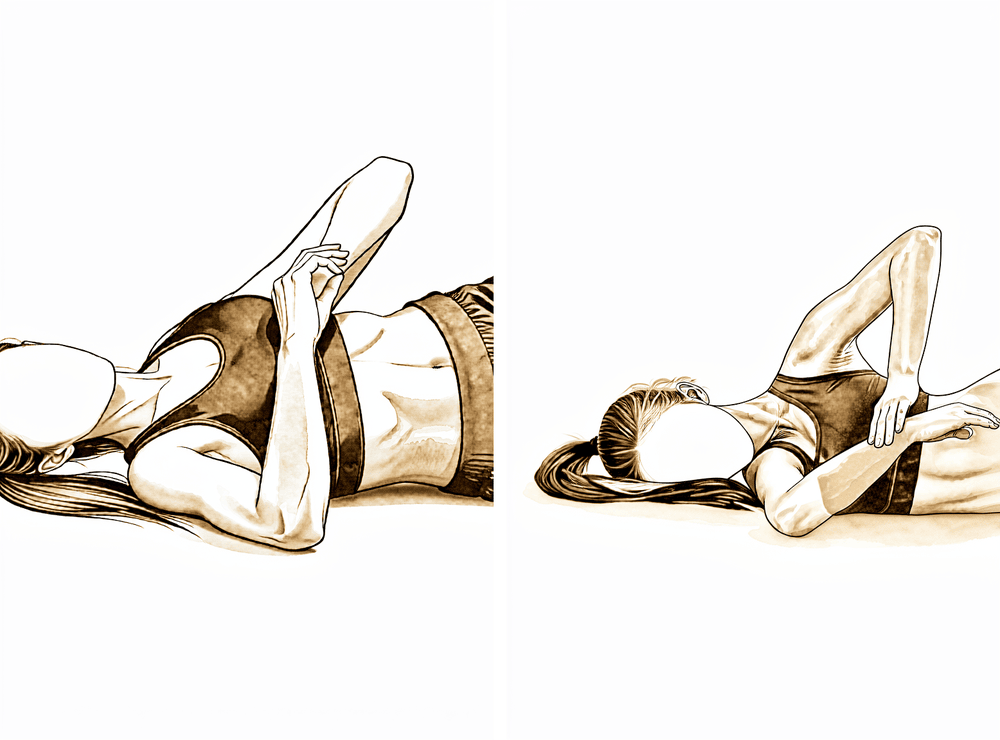
Kieran Hirpara 4.0
睡眠者拉伸
侧卧于手术侧,肩关节和肘关节各屈曲至直角。用另一只手轻柔地将前臂向下放向床面,直至肩后部感到牵拉感。保持该姿势,然后放松——应是牵拉感,而非疼痛。
在您的物理治疗师指导下
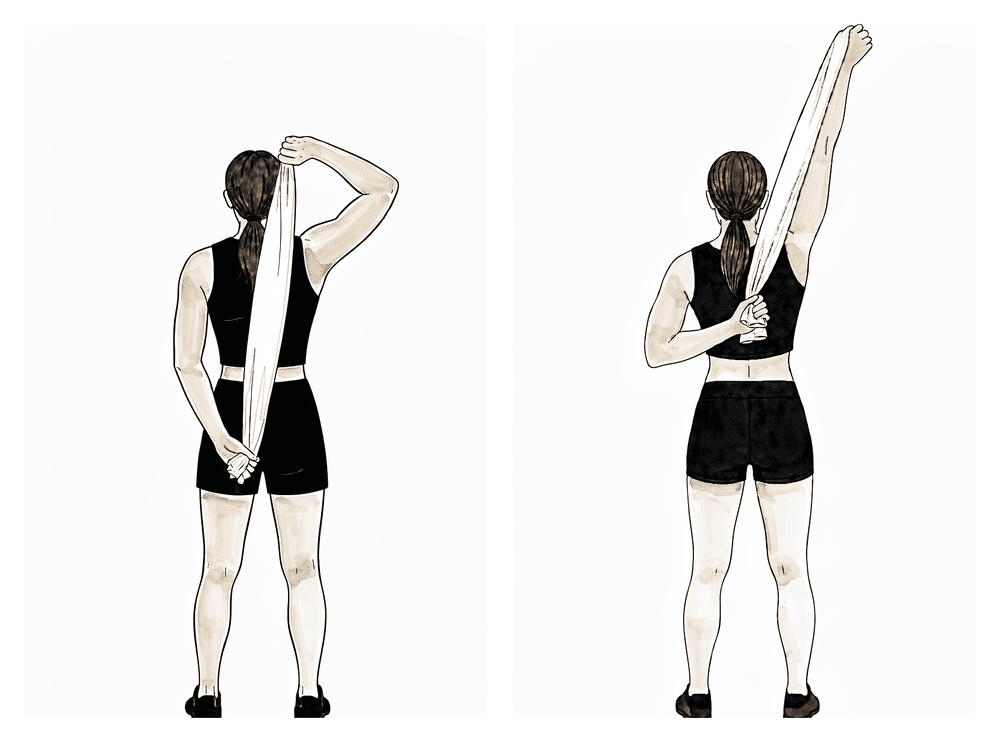
Kieran Hirpara 4.0
毛巾背后拉伸
将毛巾置于背后,健侧手越过肩部,术侧手置于腰骶部。用健侧手轻轻向上牵拉毛巾,使术侧手沿背部向上移动,直至感到牵拉感,然后放松。背后活动是最后恢复的动作之一,因此应温和地循序渐进。
在您的物理治疗师指导下
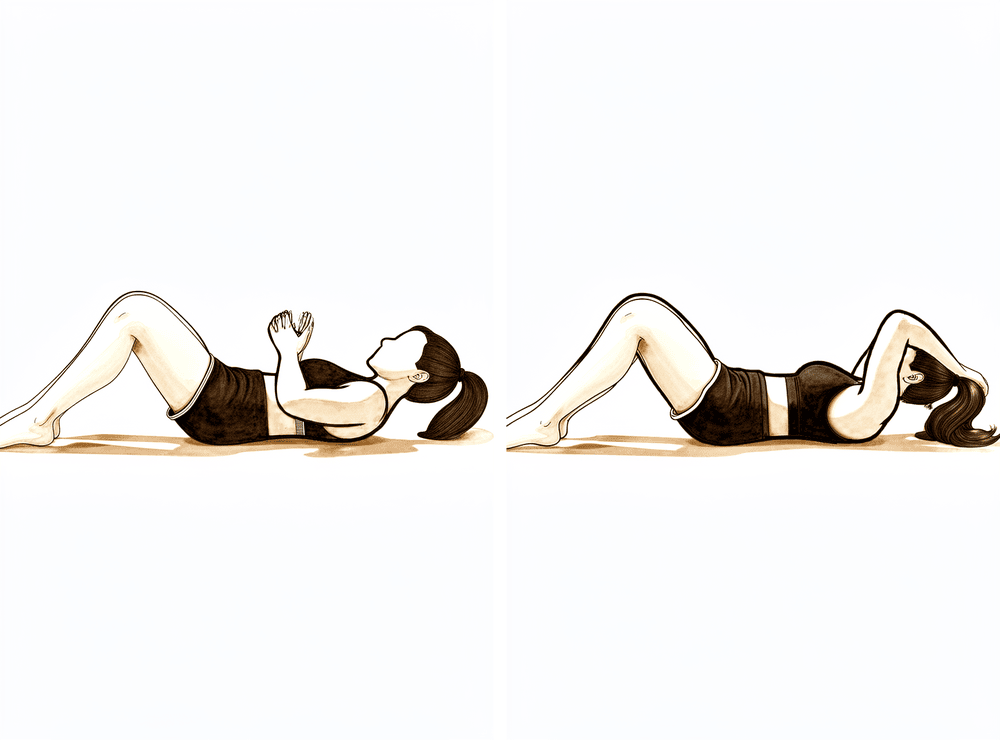
Kieran Hirpara 4.0
双手置于脑后
双手交叉置于脑后,轻柔地将肘部向外、向后展开,直至肩部前方感到牵拉。保持该姿势,然后放松。此动作可在手臂上举时恢复外旋活动度的最后部分。
在您的物理治疗师指导下

Kieran Hirpara 4.0
外旋90度
将手臂抬起至肩部高度,肘部弯曲成直角,手握橡皮筋。对抗橡皮筋的阻力将前臂向上旋转,使手背向上移动,然后缓慢复位。在运动和控制良好后,这是一个较高难度的肩袖练习。
在您的物理治疗师指导下
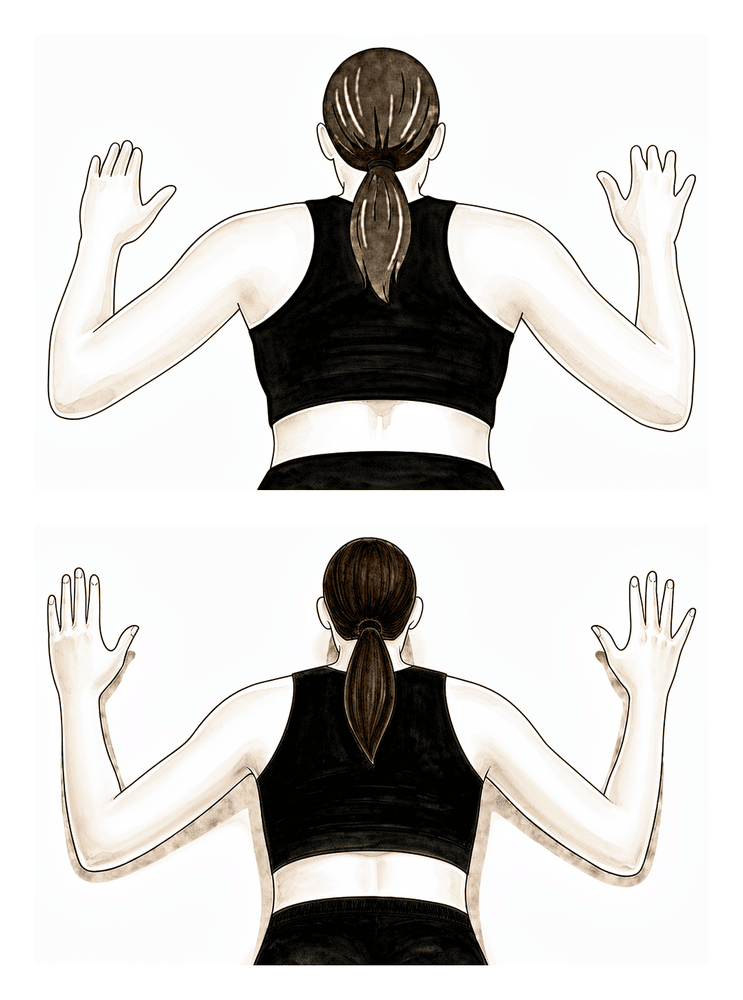
Kieran Hirpara 4.0
俯卧位 W
俯卧,双臂自然下垂。将肩胛骨相互靠拢,肘部向后下方牵引,使双臂呈“W”形,然后缓慢放下。此动作可锻炼下肩胛肌群,以稳定关节。
在您的物理治疗师指导下
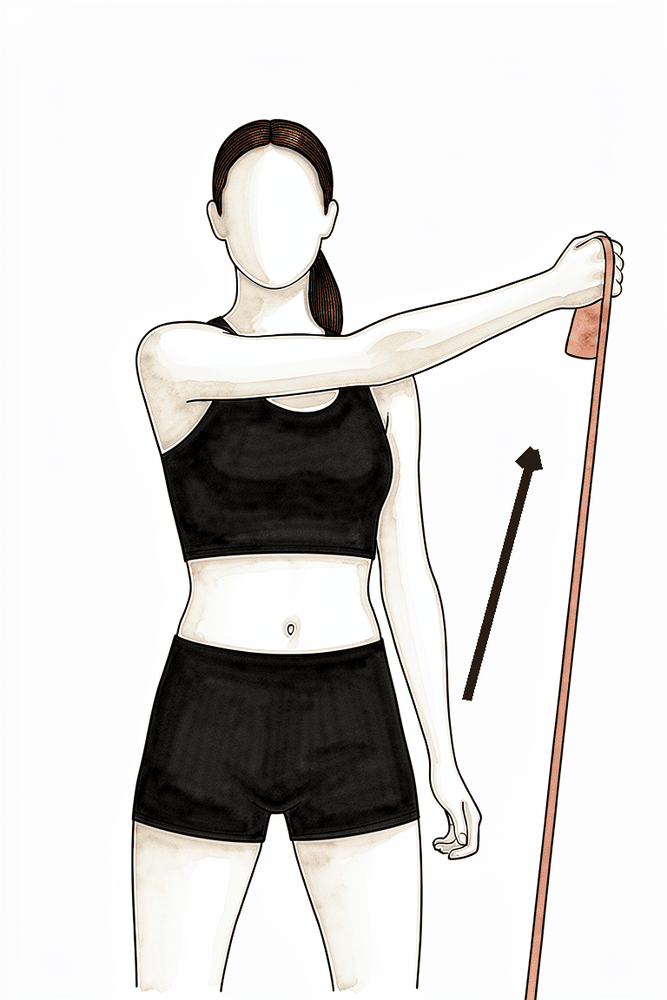
Kieran Hirpara 4.0
弹力带对角线模式(D1)
握住弹力带,沿对角线方向拉动,从身体前侧斜向上向外拉至对侧,然后缓慢还原。这种对角线动作模式按照肩部在日常伸展活动中的实际工作方式对其进行训练。
在您的物理治疗师指导下
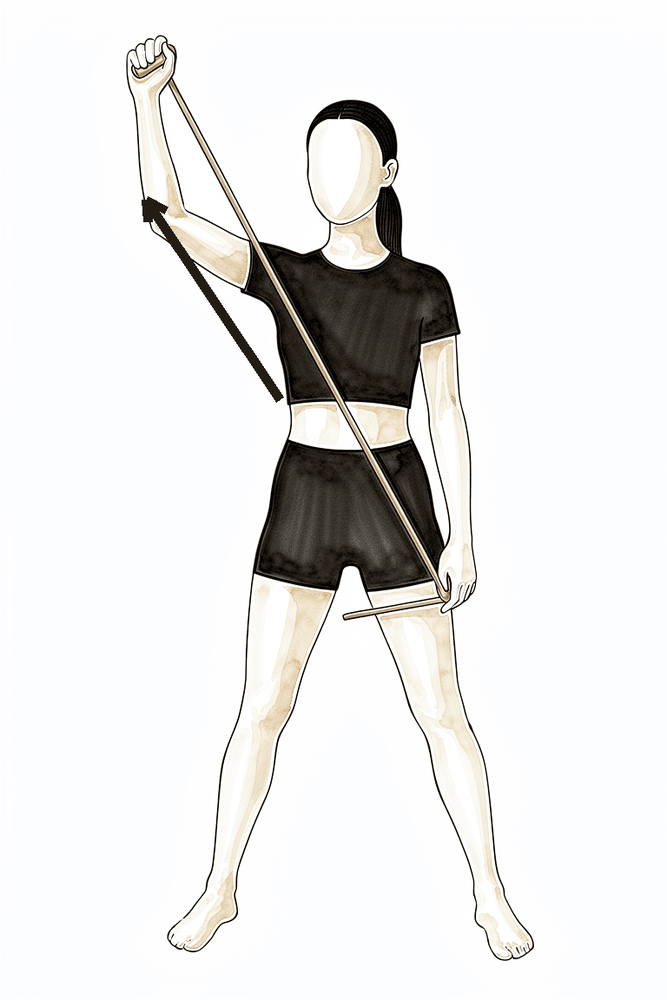
Kieran Hirpara 4.0
弹力带对角线模式(D2)
将橡皮筋持于身体低处并横向拉直,然后沿对角线方向向上向外拉至头顶侧方,结束时拇指朝上,随后缓慢还原。第二种对角线模式,通过更宽的活动范围来增强控制力。
在您的物理治疗师指导下
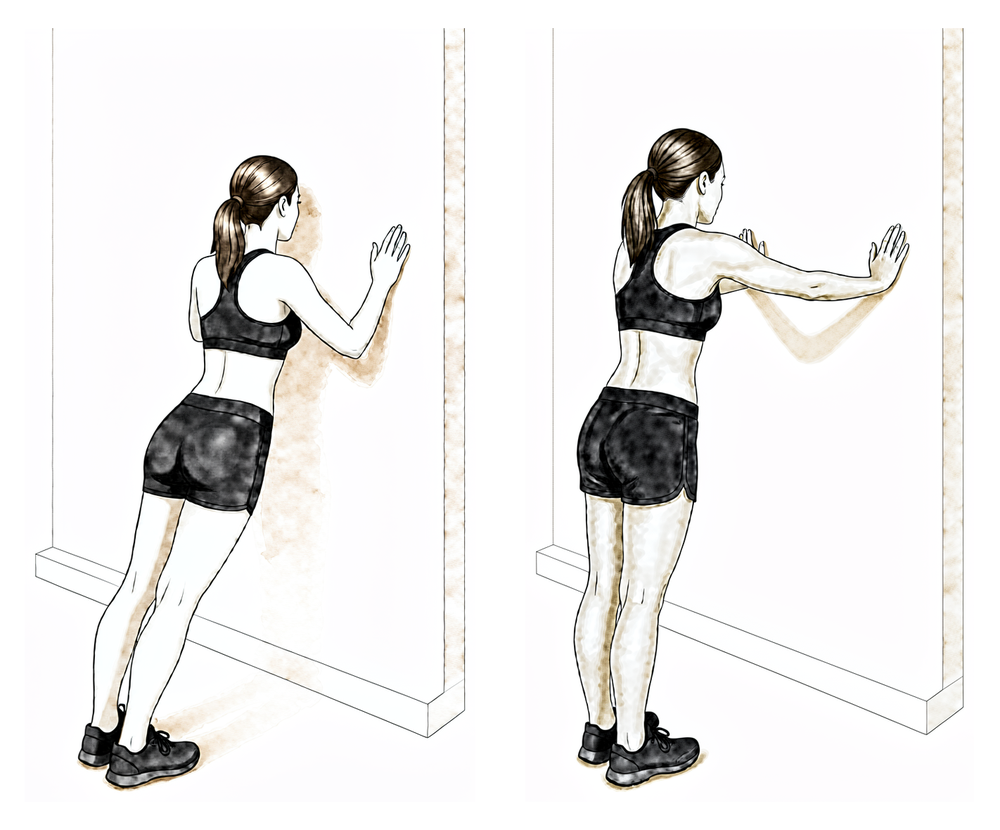
Kieran Hirpara 4.0
靠墙俯卧撑
面对墙壁站立,双手置于墙面,高度与肩部齐平。弯曲肘部使胸部靠近墙面,然后向后推;在动作顶端,再向前推一点,使上背部远离墙面呈拱形。先在墙边练习,再逐步进阶——保持肩胛骨受控。
在您的物理治疗师指导下
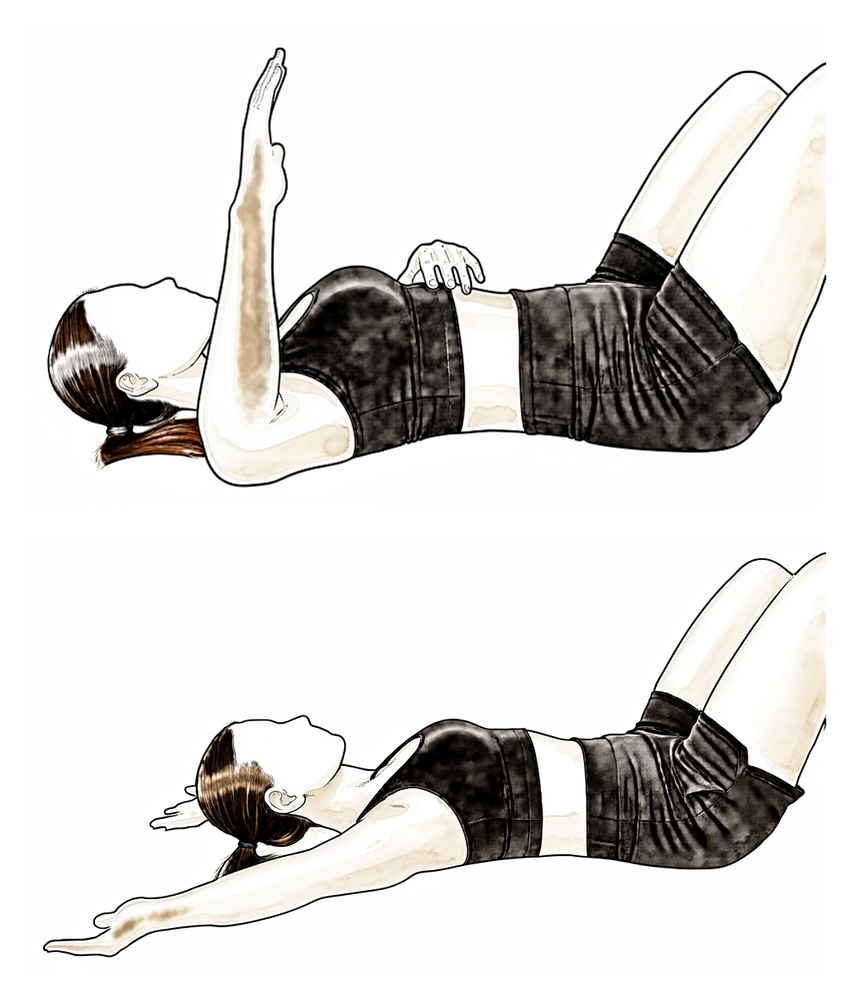
Kieran Hirpara 4.0
90/90位外旋(弹力带)
手臂侧平举至肩高,肘关节屈曲呈直角,前臂向后上方对抗轻阻力带或负重旋转,随后缓慢下放。此动作可在上举(投掷)位增强肩袖肌群力量。
每组10至15次,共2至3组,低阻力
Kieran Hirpara 4.0
90/90位(弹力带)内旋
在手臂侧平举至肩高的同一姿势下,前臂向前下方朝脚部方向旋转,对抗轻阻力带或负重,然后有控制地返回。
2至3组,每组10至15次,低阻力
Kieran Hirpara 4.0
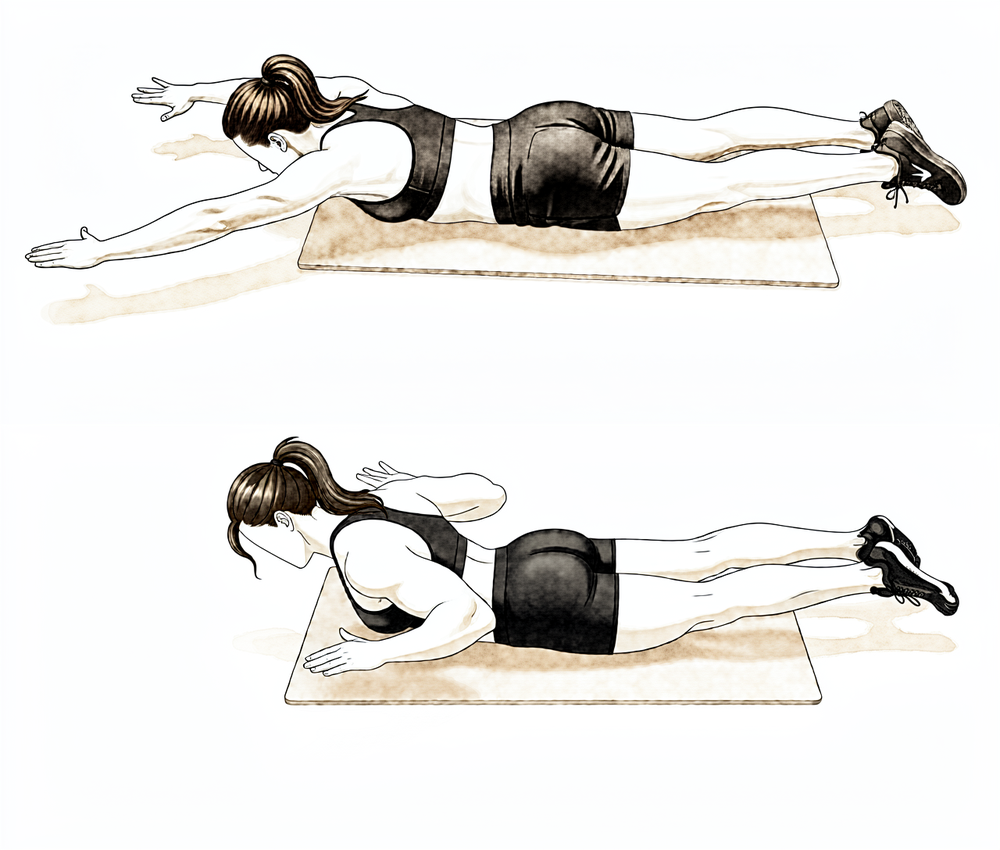
俯卧位Y形(下肩胛骨)
俯卧,将手术侧手臂向前上方伸展,与身体呈约45°角形成Y形,拇指朝上。通过向下并向后拉动肩胛骨,将手臂略微抬离支撑面,然后缓慢放下。动作要轻柔——此动作主要针对下肩胛肌群。
在物理治疗师的指导下——轻负荷、高次数
Kieran Hirpara 4.0
俯卧划船
俯卧,手术侧手臂自然下垂指向地面。将肘部向上(朝向天花板)抬起,同时将肩胛骨向脊柱方向内收挤压,然后缓慢放下。起始时不施加重量,并保持动作受控。
在您的物理治疗师指导下
随着修复组织成熟且活动度基本恢复,重点转向重建力量。此前受限的拉伸动作(跨身体拉伸和背后上举)现在用于争取最后的关节活动度。抗阻训练从弹力带逐步过渡到轻重量,俯卧撑从靠墙开始,随后逐步进阶。通常从第 16 周左右重新引入健身房力量训练,初期采用有限活动范围和轻负荷。在此阶段,仍需避免大重量的过头举重以及剧烈的推和拉动作。
致您的物理治疗师:
目标
- 所有平面的主动和被动关节活动度均达到全范围
- 肩袖和肩胛骨稳定肌群的渐进性力量、耐力及神经肌肉控制
- 为逐步回归运动特异性负荷做准备
管理
- 多方向末端关节活动度拉伸:跨身体拉伸、背后内旋、双手抱头后伸、睡眠者拉伸、外展 90 度时的外旋
- 在动态训练方案中增加渐进性抗阻(约 0.5–2.5 公斤):侧卧外旋、俯卧划船、俯卧伸展、俯卧“T”字和“Y”字、站立肩外展
- 弹力带进阶训练:“T”字、“W”字、对角线动作、外展 90 度时的内旋和外旋
- 闭链训练:从第 12 周左右开始靠墙俯卧撑,根据耐受情况逐步进阶
- 从第 16 周左右开始器械力量训练:有限活动范围、轻负荷(划船、高位下拉、肱二头肌和肱三头肌;谨慎重新引入推举动作)
- 节律性稳定、本体感觉及肩肱节律训练
注意事项
- 避免大重量举重,尤其是过头动作,以及剧烈的推和拉动作
- 强化训练应保持无痛,并避免诱发性的末端关节活动度负荷
- 在整个活动范围内保持肩胛骨控制:若出现耸肩或代偿,应降低负荷
进阶标准
- 肩关节在所有方向的主动和被动活动度均在功能范围内
- 能够耐受渐进性强化训练方案而无症状加重
第四阶段 — 重返运动与重体力劳动(第18周起)
最后阶段是逐步恢复剧烈工作、过头负重及运动。增强型训练计划中叠加了增强式训练和专项运动训练,间歇训练方案指导患者重返投掷、游泳、高尔夫和球拍类运动。重返对抗性和碰撞性运动通常需要术后四到六个月,具体取决于手臂是否恢复完全的活动度、力量和信心;针对碰撞类运动员的已发表方案有时持续时间更长,可达约九个月。力量型运动员通常在相似的时间框架内逐步恢复至其常规训练水平。您的物理治疗师和外科医生将指导最终的康复许可,部分碰撞类运动员选择在重返赛场后的首个赛季佩戴肩部护具。
致您的物理治疗师:
目标
- 维持全范围关节活动度
- 将力量、爆发力和耐力逐步提升至满足患者工作和运动需求
- 基于标准、循序渐进地重返对抗性和过头运动
管理
- 继续并推进第三阶段增强型训练计划
- 闭链运动进阶:俯卧撑进阶至不稳定表面,墙球训练
- 针对投掷和过头运动员的增强式训练:反弹球投掷、加权球训练、墙前运球、减速训练
- 针对投掷、高尔夫、网球和游泳的间歇运动方案
- 针对功能和职业特异的运动链力量与耐力训练
注意事项
- 仅在恢复全范围活动度、力量恢复并获得外科医生许可后,方可重返对抗性和碰撞性运动
- 进阶过程仍以症状为导向:若出现疼痛或不稳定感,应退回上一阶段
您的康复方案之后
上述各阶段源自已发表的肩锁关节稳定与重建康复方案:马萨诸塞州总医院布里格姆运动医学中心、马萨诸塞州总医院运动医学肩锁关节重建项目、英国肩部专科单位的肩锁关节稳定指南,以及一项针对公开可用的肩锁关节重建方案的系统综述。周数范围通常为典型值而非固定值,且已发表的项目存在差异;您的持续康复由您的物理治疗师根据修复和运动功能的恢复情况,与诊所协作进行个体化指导。本页面与诊所的一般恢复建议相辅相成;请参阅术后疼痛管理和伤口护理。关于手术本身及其治疗的损伤,请参阅肩锁关节稳定术。本方案背后的证据(包括重建手术、复位丢失文献及康复研究)在证据部分进行了总结,可从本页面顶部获取 PDF 版本。
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Topic scope: Post-operative rehabilitation after acromioclavicular (AC) joint stabilisation / reconstruction for a high-grade AC joint dislocation (Rockwood type III–V) — restoring the alignment between the clavicle and scapula with a coracoclavicular (CC) suspensory device (suture-button / endobutton construct), with or without a biological tendon graft (semitendinosus / pectoralis minor) and with or without a direct AC ligament reconstruction. This page also summarises the operative/non-operative evidence that frames the rehabilitation choices. It is the clinician-facing companion to the patient protocol.
Defining principle of the surgical rehab here — PROTECT the construct. Unlike a capsular release (where the enemy is re-stiffening and rehab is immediate aggressive ROM), AC joint stabilisation is a protect-the-repair pathway, closer in spirit to a rotator-cuff or instability repair. The reconstruction has to resist the constant downward pull of gravity on the weight of the arm — the exact deforming force that displaced the joint in the first place. A suspensory suture-button or tendon graft has no early intrinsic strength; biological healing of the CC/AC ligaments and tunnel incorporation takes weeks to months, and the dominant early complication is loss of reduction before that healing matures. So the rehab is deliberately conservative: the sling carries the weight of the arm (typically ~6 weeks), active elevation and any downward traction on the arm are avoided early, ROM is restricted (no elevation > 90°, no cross-body, no reaching behind the back) for the first 6 weeks, strengthening waits until the construct has matured (~12 weeks), and return to contact/collision sport is deferred to ~4–6 months. Motion progression and protection are the two levers; the single most important point distinguishing this protocol from the capsular-release inversion is that here, time and protection are the friends, not the enemy.
A. THE OPERATION & WHY REHAB IS PROTECTIVE
A high-grade AC dislocation tears the AC and coracoclavicular (conoid + trapezoid) ligaments, allowing the clavicle to rise relative to the acromion under the weight of the arm. Surgical stabilisation aims to restore the CC distance and let the ligaments heal in a reduced position. Contemporary constructs are predominantly:
- CC suspensory fixation — a suture-button / endobutton loop passed through clavicular and coracoid tunnels (e.g. flip-button, single- or double-tunnel). Restores vertical stability.
- + Biological augmentation — a free tendon graft (semitendinosus allograft/autograft, or the pectoralis minor / coracoacromial ligament in Weaver–Dunn-type procedures) to reconstruct the CC ± AC ligaments. The anatomy of the pectoralis minor tendon has been characterised specifically for this use [pec minor anatomy, JSES 2007].
- + Direct AC reconstruction — adding an AC-level construct to the CC reconstruction improves horizontal stability; combined CC + AC reconstruction gives better radiographic reduction and lower reoperation rates than isolated CC reconstruction in pooled data.
The structural properties of the reconstructed CC complex have been measured biomechanically: reconstructions restore much, but not all, of the intact ligament's stiffness and load to failure [Structural Properties, Am J Sports Med 2000]. This is the mechanical basis for protecting the construct early — the graft/button is weaker than the native ligament until it heals and incorporates.
B. EVIDENCE BY THEME
1. Operative vs non-operative — only high grades benefit from surgery
- Type I–II AC injuries are managed non-operatively. Type III is genuinely controversial and most are treated non-operatively first; type IV–V are the usual operative indications [ACJ Injuries: Evidence-based Treatment, JAAOS 2018]. A network meta-analysis of RCTs for acute Rockwood III–V found no single surgical technique clearly superior, and that surgery's advantage over non-operative care is modest and grade-dependent [network MA, JSES 2023].
- Hook-plate fixation of acute dislocations improved radiographic but NOT clinical outcomes versus non-operative treatment [Hook-plate RCT, JBJS 2017] — a caution that radiographic reduction does not automatically translate into a better patient outcome, and a reason the hook plate (which requires removal) is not the preferred construct here.
- The Rockwood classification itself has only moderate reliability between observers [Rockwood reliability, JSES 2021], which is part of why type III decision-making is debated.
2. Loss of reduction is the dominant complication — and it shapes the rehab
- Loss of reduction (the clavicle drifting back up) is the most frequent radiographic failure after suspensory-device stabilisation. Clavicular tunnel widening correlates with post-operative loss of reduction in an implant-dependent way [tunnel widening, Arthroscopy 2023] — i.e. the construct and tunnel position matter.
- Radiographic failure and reoperation rates after ACJ reconstruction are non-trivial [radiographic failure / reoperation, Bone Joint J 2016]; one suspensory-device series reported ~10–11% revision for loss of reduction / implant failure (suture fatigue, button escape, coracoid stress fracture, deep infection) [web: suspensory-device cohort].
- Adding the AC-level reconstruction and a biological graft improves radiographic reduction and lowers reoperation versus isolated CC suture-button [web: combined CC+AC reviews].
- Complications after operative treatment of high-grade injuries are well catalogued [complications, JSES 2023] — they include loss of reduction, coracoid/clavicle fracture, hardware problems and infection.
Rehab implication: because the early failure mode is mechanical loss of reduction under arm-weight loading, the early phase forbids active elevation, lifting, downward traction on the arm and weight-bearing through the arm — the patient protects the construct while the ligaments and tunnels heal.
3. Outcomes and return to sport are generally good — but timeline is conservative
- Anatomic CC reconstruction with semitendinosus graft for chronic dislocation gives good clinical and radiological results [semitendinosus reconstruction, KSSTA 2020].
- Sports activity after anatomic flip-button stabilisation is generally restored, with most athletes returning to their pre-injury sport, though return is gradual [flip-button sport, KSSTA 2016].
- Delayed (chronic) reconstruction with a modern suspensory device does not increase fixation failure or major complications versus acute fixation [web: delayed reconstruction].
4. The rehab protocol itself is consensus/expert, not RCT-derived — and it is highly variable
A systematic review of publicly available ACJ-reconstruction rehabilitation protocols found they are widely variable: sling duration ranged 3–8 weeks (the modal recommendation was 6 weeks, in 8/18 protocols), active ROM commonly began at ~6 weeks (6/20 protocols), and heavy/strenuous shoulder use was typically prohibited for a further ~6 weeks beyond the initial 6-week protection period [Cheema et al., Arthrosc Sports Med Rehabil 2021]. There is no high-level RCT defining the optimal post-op regimen — phase timings are expert/consensus.
The patient protocol's phase boundaries (0–6 / 6–12 / 12–18 weeks, sling 6 weeks, return to contact sport ~4–6 months) sit squarely within this published range and match the Massachusetts General Brigham / MGH Sports Medicine ACJ-reconstruction guideline (Phase I 0–6 wk, Phase II 7–12 wk, Phase III 13–18 wk) and similar surgeon protocols (e.g. Dickens: 6-week sling, return to all activity months 4–6).
C. PHASED POST-OP TIMELINE (consistent with the patient protocol)
| Phase | Window | Sling | ROM | Strengthening | Notes |
|---|---|---|---|---|---|
| I — Protecting the repair | Weeks 0–6 | Yes, ~6 wk whenever up; worn for sleep weeks 0–3 (arm-weight loads the repair even lying down) | Pendulum + passive/assisted elevation to 90° max in scapular plane; assisted ER to ~30°; NO active elevation, no cross-body, no behind-the-back | Hand/wrist/elbow AROM; scapular setting; sub-maximal pain-free isometric IR/ER only | No driving while in the sling (~6 wk). No lifting > ~0.5 kg, no carrying, no leaning/pushing up on the arm, no letting the arm hang unsupported — each loads the construct |
| II — Restoring movement | Weeks 6–12 | Wean off | Progress assisted → active ROM; build toward full by ~12 wk (~15°/week as a guide); behind-the-back introduced gradually (to beltline) | Light elastic-band cuff + scapular work begins (rows, IR/ER, serratus punch); side-lying ER, prone row/T/Y | Lift to ~1 kg; avoid forceful push/pull, push-ups, overhead and cross-body lifting |
| III — Strengthening | Weeks 12–18 | Off | Full ROM goal; end-range stretches (cross-body, behind-back, sleeper) now used to win final range | Progressive resistance ~0.5–2.5 kg; wall push-ups from ~wk 12; machine weights from ~wk 16 (limited range, light load) | Construct matured; still avoid heavy overhead and forceful push/pull |
| IV — Return to sport / heavy work | Week 18 onward | Off | Maintain full ROM | Plyometrics, sport-specific & interval programs; occupation-specific kinetic-chain loading | Return to contact/collision sport ~4–6 months (collision athletes / some occupations longer, up to ~9 mo); criteria-based clearance; some wear a brace first season back |
(Phase boundaries from the MGH/Mass General Brigham ACJ-reconstruction guideline; return-to-sport windows from the flip-button sport series and surgeon protocols; all within the variability documented by Cheema et al. 2021.)
D. KEY CONTROVERSIES / EVIDENCE QUALITY
- Type III — operate or not? The most-debated grade; most are trialled non-operatively first. No clear winner in RCT-level data, compounded by only-moderate reliability of the Rockwood grade itself. Moderate / conflicting.
- Which construct? Network MA shows no single technique clearly superior for acute III–V. Combined CC + AC reconstruction (± graft) gives better radiographic reduction and lower reoperation than isolated CC suture-button, but at the cost of complexity. Hook plates improve radiographs but not clinical scores and need removal. Moderate.
- Loss of reduction vs clinical outcome. Radiographic loss of reduction is common yet often clinically well-tolerated — radiographic and patient-reported outcomes diverge. This tempers how aggressively reduction should be chased. Moderate.
- The rehab protocol is consensus, not trial-derived, and published protocols vary widely (sling 3–8 wk; Cheema 2021). The patient page's timings are typical, not RCT-validated. Weak / consensus.
E. EVIDENCE-STRENGTH FLAGS (summary)
- STRONG (RCT / SR-MA): hook-plate improves radiographic but not clinical outcomes vs non-operative (RCT, JBJS 2017); network meta-analysis of RCTs for acute III–V shows no clearly superior technique (JSES 2023).
- MODERATE (cohorts / biomechanical / SR): anatomic semitendinosus CC reconstruction outcomes (KSSTA 2020); sports return after flip-button stabilisation (KSSTA 2016); loss-of-reduction / tunnel-widening drivers (Arthroscopy 2023; Bone Joint J 2016); complications of high-grade operative treatment (JSES 2023); reconstructed-CC biomechanics (AJSM 2000); combined CC+AC > isolated CC for reduction/reoperation; delayed reconstruction safety.
- WEAK / CONSENSUS ONLY: the post-operative rehabilitation protocol itself — no defining RCT; protocols are expert/consensus and highly variable (Cheema 2021; sling 3–8 wk). Rockwood classification reliability only moderate (JSES 2021).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Anatomy of the pectoralis minor tendon and its use in acromioclavicular joint reconstruction. J Shoulder Elbow Surg. 2007. DOI: 10.1016/j.jse.2006.09.007
- Clavicular tunnel widening after acromioclavicular stabilization shows implant-dependent correlation with postoperative loss of reduction. Arthroscopy. 2023. DOI: 10.1016/j.arthro.2023.05.014
- Acromioclavicular joint injuries: evidence-based treatment. J Am Acad Orthop Surg. 2018. DOI: 10.5435/jaaos-d-17-00105
- Review of Weaver and Dunn on treatment of acromioclavicular injuries, especially complete acromioclavicular separation. J ISAKOS. 2019. DOI: 10.1136/jisakos-2019-000299
- Structural properties of the intact and the reconstructed coracoclavicular ligament complex. Am J Sports Med. 2000. DOI: 10.1177/03635465000280010201
- Complications after operative treatment of high-grade acromioclavicular injuries. J Shoulder Elbow Surg. 2023. DOI: 10.1016/j.jse.2023.03.019
- Sports activity after anatomic acromioclavicular joint stabilisation with flip-button technique. Knee Surg Sports Traumatol Arthrosc. 2016. DOI: 10.1007/s00167-016-4287-7
- Anatomic reconstruction of the coracoclavicular and acromioclavicular ligaments with semitendinosus tendon graft for the treatment of chronic acromioclavicular joint dislocation provides good clinical and radiological results. Knee Surg Sports Traumatol Arthrosc. 2020. DOI: 10.1007/s00167-020-06285-x
- Hook-plate fixation in patients with acute acromioclavicular joint dislocation improved radiographic but not clinical outcomes compared with nonoperative treatment. J Bone Joint Surg Am. 2017. DOI: 10.2106/jbjs.16.00582
- Radiographic failure and rates of re-operation after acromioclavicular joint reconstruction. Bone Joint J. 2016. DOI: 10.1302/0301-620x.98b4.35935
- Treatment options for acute Rockwood type III–V acromioclavicular dislocations: a network meta-analysis of randomized controlled trials. J Shoulder Elbow Surg. 2023. DOI: 10.1016/j.jse.2023.01.039
- A relook at the reliability of Rockwood classification for acromioclavicular joint injuries. J Shoulder Elbow Surg. 2021. DOI: 10.1016/j.jse.2021.01.016
Literature (URLs)
- Cheema SG, Hermanns C, Coda RG, et al. Publicly accessible rehabilitation protocols for acromioclavicular joint reconstruction are widely variable. Arthrosc Sports Med Rehabil. 2021;3(2):e427–e433. https://doi.org/10.1016/j.asmr.2020.10.007 (sling 3–8 wk, modal 6 wk; active ROM ~6 wk; further ~6 wk before heavy use)
- Acromioclavicular joint injuries: effective rehabilitation (review). PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC8169819/
- Delayed acromioclavicular joint reconstruction using a modern tunnelled suspensory device does not increase the risk of fixation failure or major complications. PubMed. https://pubmed.ncbi.nlm.nih.gov/35781084/
- Low rate of substantial loss of reduction immediately after hardware removal following ACJ stabilization using a suspensory fixation system. KSSTA. https://link.springer.com/article/10.1007/s00167-022-06978-5
- Minimum 10-year outcomes after arthroscopically assisted anatomic coracoclavicular ligament reconstruction for type III and V AC joint injuries. ScienceDirect. https://www.sciencedirect.com/science/article/pii/S2666638325001835
Published rehab protocols (URLs — basis for the phase structure)
- Massachusetts General Brigham Sports Medicine. Rehabilitation guideline for acromioclavicular joint reconstruction (including coracoclavicular ligament reconstruction). https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-acromioclavicular-joint-reconstruction.pdf (Phase I 0–6 wk sling, Phase II 7–12 wk, Phase III 13–18 wk)
- Dickens JD. AC joint reconstruction protocol (Duke Sports Medicine). https://www.jondickensmd.com/pdf/ac-joint-reconstruction-protocol.pdf (6-week sling worn for sleep; return to all activity months 4–6)
- Chambler A. ACJ stabilisation rehabilitation guidelines. https://www.andrewchambler.com/post/acj-stabilisation-rehabilitation-guidelines
- North Tees and Hartlepool NHS Foundation Trust. Acromioclavicular joint stabilisation — LockDown/Weaver Dunn procedure. https://www.nth.nhs.uk/resources/acromioclavicular-joint-stabilisation-lockdown-weaver-dunn-procedure/
- Stone Clinic. Acromioclavicular (AC) joint reconstruction rehab protocol. https://www.stoneclinic.com/Acromioclavicular-AC-joint-reconstruction-rehab-protocol





